Related Experiment Video
Updated: Aug 5, 2026

Implantation Protocol of the Foldable Capsular Vitreous Body for Complex Vitreoretinal Surgery
Published on: April 14, 2026
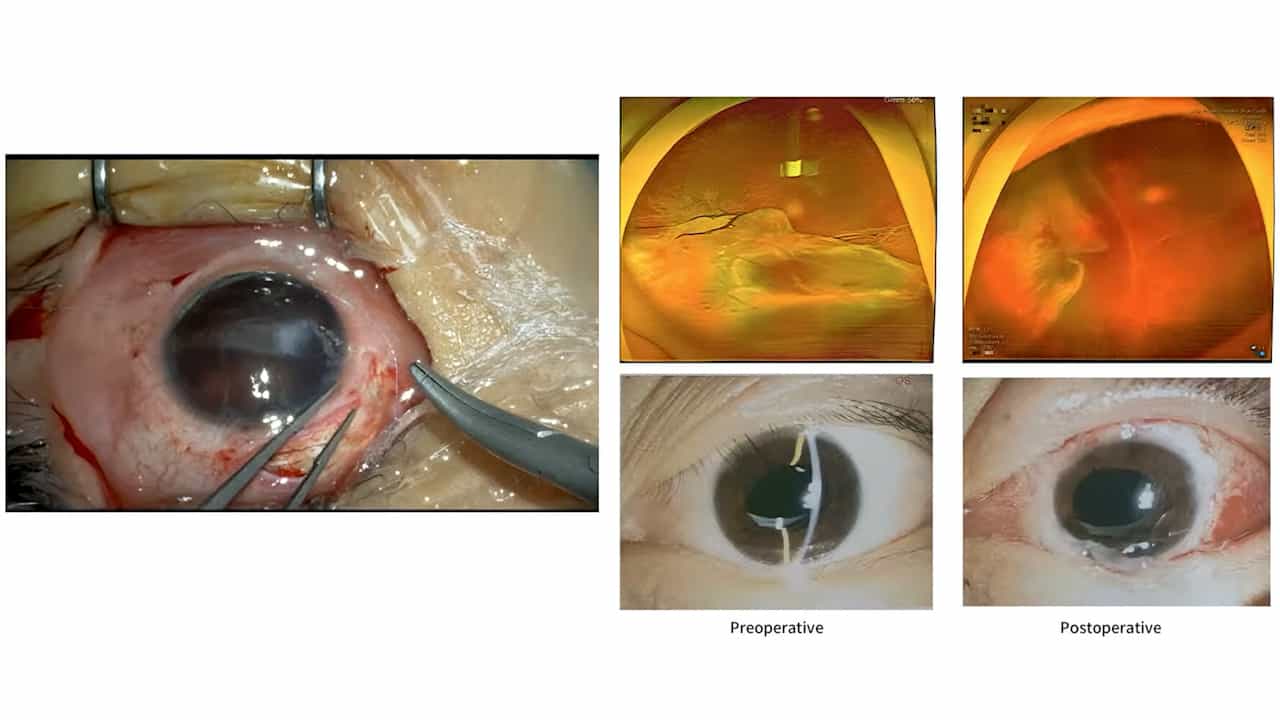
Minimally Invasive Segmental Scleral Buckle as Primary Surgery for the Repair of Rhegmatogenous Retinal Detachment: A
Supanji Supanji1,2,3, Dewi Fathin Romdhoniyyah1,2, Hifdza Faza Felisha1
1Department of Ophthalmology, Faculty of Medicine Public Health and Nursing, Universitas Gadjah Mada, Yogyakarta, Indonesia, ugm.ac.id.

Introduction:
The scleral buckling (SB) or encircling buckle technique has been employed in the management of rhegmatogenous retinal detachment (RRD). While encircling buckle technique offers substantial assistance in managing RRD, particularly for cases involving numerous breaks or extensive detachments, this procedure is time-consuming and associated with complications such as anterior segment ischemia. In contrast, segmental scleral buckling (SSB) provides a more targeted approach for correcting retinal detachments. Thus, SSB is technically straightforward in the hands of an experienced vitreoretinal surgeon. Herein, we delineate anatomical and functional results of SSB in RRD patients.
Result:
Seven consecutive patients (seven eyes) with primary RRD were treated with the SSB technique and followed up for 6 months. Postoperatively, all seven individuals exhibited satisfactory buckle positioning and height, with retinal detachments resolving within 24 h. Subretinal fluid drainage was required in five of seven eyes, reflecting the relatively bullous nature of most detachments, whereas two eyes were successfully reattached without drainage. At both 1- and 6-month follow-ups, anatomical and functional improvements were maintained, demonstrating a 100% reattachment rate with no reported surgical complications or instances of redetachment.
Conclusion:
In this small, consecutive case series from a tertiary referral centre in Indonesia, SSB achieved favourable anatomical and functional outcomes at 6 months, with no redetachment or serious complications. The procedure was well tolerated, and in our resource-limited setting, the material costs were lower than those of encircling buckling or vitrectomy based on local procurement prices, although we did not conduct a formal economic analysis. We therefore suggest that SSB remains a reasonable primary option for selected RRD cases, particularly in young, myopic patients with a single break. Larger, ideally multicentre studies are needed to confirm these observations and to explore generalisability to less experienced surgeons.
