Outcomes of splenic artery embolization in patients with portal hypertension: a single center experience
Related Experiment Video
Updated: Aug 6, 2026
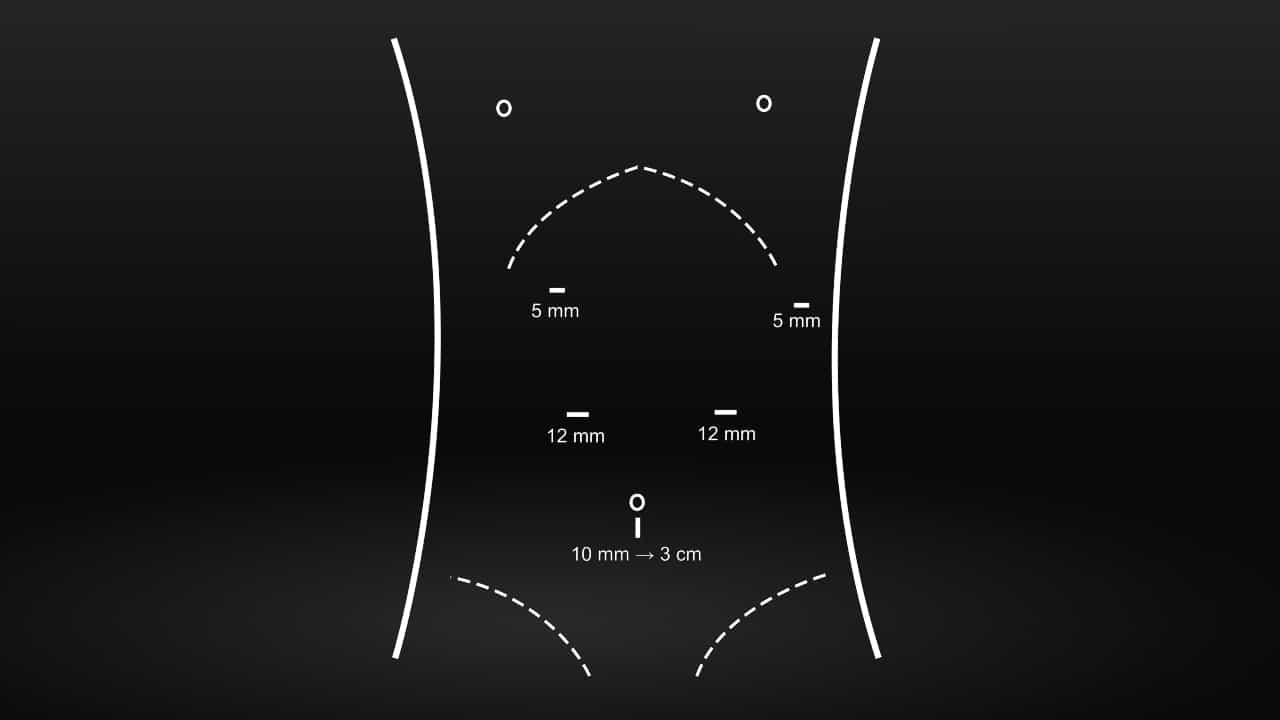
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Johan Waern1, Johann P Hreinsson1, Adrian Mahdavian1
1Department of Medicine, Sahlgrenska University Hospital, Gothenburg, Sweden.

Insights
Splenic artery embolization (SAE) is a feasible treatment for portal hypertension complications, reducing spleen size. Outcomes were more favorable in non-cirrhotic portal hypertension (NCPH) than cirrhotic portal hypertension (CPH).
Area of Science:
- Interventional Radiology
- Hepatology
- Vascular Surgery
Background:
- Portal hypertension, encompassing cirrhotic (CPH) and non-cirrhotic (NCPH) forms, presents severe complications like variceal bleeding and ascites.
- Long-term clinical impact data for splenic artery embolization (SAE) in managing portal hypertension complications remain limited.
Purpose of the Study:
- To evaluate the long-term clinical impact and outcomes of splenic artery embolization (SAE) in patients with portal hypertension.
- To compare the effectiveness of SAE in patients with CPH versus NCPH.
Main Methods:
- A retrospective, single-center study was conducted involving patients who underwent SAE for portal hypertension complications between January 2016 and December 2024.
- Clinical, radiological, and laboratory data were collected at baseline and during follow-up to assess overall survival, gastrointestinal bleeding, complications, and changes in clinical features.
Main Results:
- Twenty patients (50% CPH, 50% NCPH) were included. SAE significantly reduced spleen volume and splenic vein diameter, with stable liver function.
- Complications occurred in 65% of patients, most commonly post-embolization syndrome (45%).
- Patients with CPH showed trends toward poorer survival and higher gastrointestinal bleeding risk post-SAE compared to NCPH patients.
Conclusions:
- Splenic artery embolization (SAE) is a feasible treatment for portal hypertension complications in patients unsuitable for standard therapies.
- Outcomes appear more favorable in non-cirrhotic portal hypertension (NCPH) compared to cirrhotic portal hypertension (CPH).
- Larger prospective studies are needed to clarify the role of SAE in clinical practice.
Background:
Cirrhotic (CPH) and non-cirrhotic portal hypertension (NCPH) can result in severe complications, including variceal bleeding, ascites, and hypersplenism. However, evidence regarding the long-term clinical impact of splenic artery embolization (SAE) in portal hypertension remains limited.
Patients And Methods:
We conducted a retrospective single-center study including consecutive patients who underwent SAE for complications of portal hypertension at Sahlgrenska University Hospital, Gothenburg, Sweden, between January 2016 and December 2024. Clinical, radiological, and laboratory data were collected at baseline and during follow-up. Overall survival, gastrointestinal bleeding, complications, and changes in clinical features of portal hypertension were evaluated.
Results:
Twenty patients were included (median age 47 years; 60% male), with an equal distribution of CPH and NCPH. The most common indication for SAE was failure of endoscopic treatment for gastroesophageal varices (50%). SAE resulted in a significant reduction in spleen volume (1,325 vs. 1,146 mL, p = 0.024) and splenic vein diameter (14 vs. 12 mm, p = 0.008), while liver function remained stable. Complications occurred in 65% of patients, with post-embolization syndrome being the most frequent (45%). Patients with CPH showed a trend toward poorer overall survival (HR 4.94, 95% CI 0.57-42.7; p = 0.15) and a trend toward a higher risk of gastrointestinal bleeding after SAE (HR 8.02, 95% CI 0.96-66.8; p = 0.054) than those with NCPH.
Conclusions:
SAE appears to be a feasible treatment option for portal hypertension-related complications in patients unsuitable for standard therapies, with more favorable outcomes in NCPH than CPH. Larger prospective studies are warranted to better define its role in clinical practice.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:22
Portal Hypertension