Related Experiment Video
Updated: Aug 5, 2026


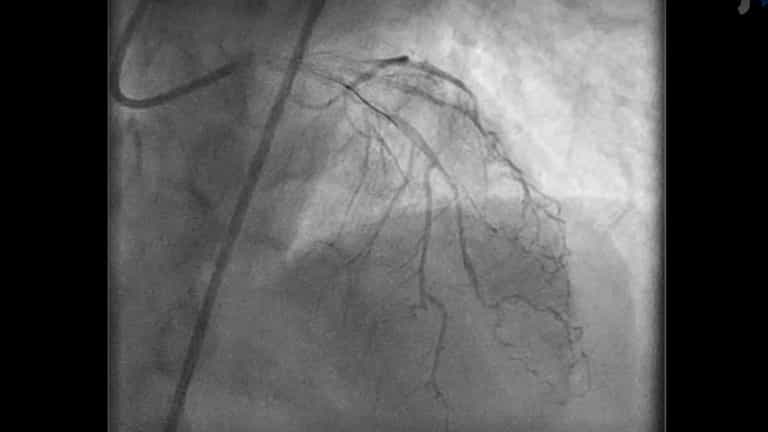
Testing Acetylcholine Followed by Adenosine for Invasive Diagnosis of Coronary Vasomotor Disorders
Published on: February 3, 2021
Acute cardiovascular complications of sympathomimetic recreational drug use
1Emergency department, OLVG Hospital, locatie Oost, Amsterdam, The Netherlands.

Introduction:
Recreational drug use is rising globally, with significant cardiovascular implications. Sympathomimetic substances such as cocaine, amfetamine(amphetamine)-type stimulants and synthetic cathinones are increasingly associated with emergency department presentations and acute cardiac events. Despite this growing burden, standardized guidance for diagnosing and managing acute sympathomimetic recreational drug-related cardiovascular complications remains limited.
Methods:
A narrative review of the literature was conducted to identify acute cardiovascular complications associated with commonly used recreational drugs. A PubMed search was performed from database inception to 1 March 2024 using combinations of cardiovascular symptoms and cardiovascular complications with terms related to sympathomimetic recreational drug use.
Results:
These substances exert potent sympathomimetic effects through catecholamine excess, and cause receptor activation, ion channel interference, and direct myocardial toxicity. Cocaine additionally induces vasospasm and thrombosis via endothelin-1 and causes sodium channel and potassium channel blockade. Amfetamine-type stimulants and synthetic cathinones amplify catecholamine release, contributing to arrhythmia, ischemia, and myocardial injury. Acute cardiovascular manifestations include chest pain, acute coronary syndrome, arrhythmias, cardiomyopathy, and sudden cardiac death. Presentations often mimic classical cardiac syndromes but may be more severe, especially in younger patients without traditional risk factors. Diagnosis begins with detailed history-taking, although self-reported drug use is frequently unreliable. Depending on symptoms, electrocardiography, cardiac biomarkers and echocardiography may be essential for risk stratification and identifying the underlying pathology. Toxicological testing may be considered when clinically indicated and should be interpreted in conjunction with clinical findings. For cocaine associated chest pain patients, risk stratification with the HEART pathway may guide safe discharge in low-risk cases. Management should be individualized based on the specific recreational drug involved and the presenting symptoms. Sedation, antihypertensives, and dual antiplatelet therapy are foundational, with vasodilators when indicated. Beta-blockers with alpha-blocking properties may be beneficial in selected patients. Early drug counselling and referral are critical to reduce recurrence.
Discussion:
In most cases, evaluation and management of acute cardiovascular symptoms in patients with suspected sympathomimetic drug use should follow standard guideline-based cardiovascular care. However, specific modifications may be required, including selective use of toxicological testing when it is expected to influence clinical decision-making, early sedation to reduce sympathetic overactivity, and cautious selection of beta-blockers depending on the substance involved. Awareness of these distinctions is essential to avoid both under- and overtreatment.
Conclusion:
Clinicians must recognize the acute cardiovascular risks of sympathomimetic recreational drugs and integrate routine drug screening, tailored management, and addiction intervention into acute care pathways to improve outcomes and reduce morbidity.

Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:23
Drugs Acting on Autonomic Ganglia: Stimulants
Ganglionic stimulants activate NM nicotinic receptors in autonomic ganglia, falling into two categories: nicotine mimetics [e.g., lobeline, dimethylpiperazine, tetramethylammonium] and muscarinic receptor agonists [e.g., muscarine, methacholine]. The first category's action is rapid and blocked by nicotinic receptor antagonists, while the second category's action is delayed and blocked by atropine-like agents. Nicotine, an alkaloid, affects the heart rate by stimulating sympathetic or...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:25
Adrenergic Agonists: Indirect-Acting Agents
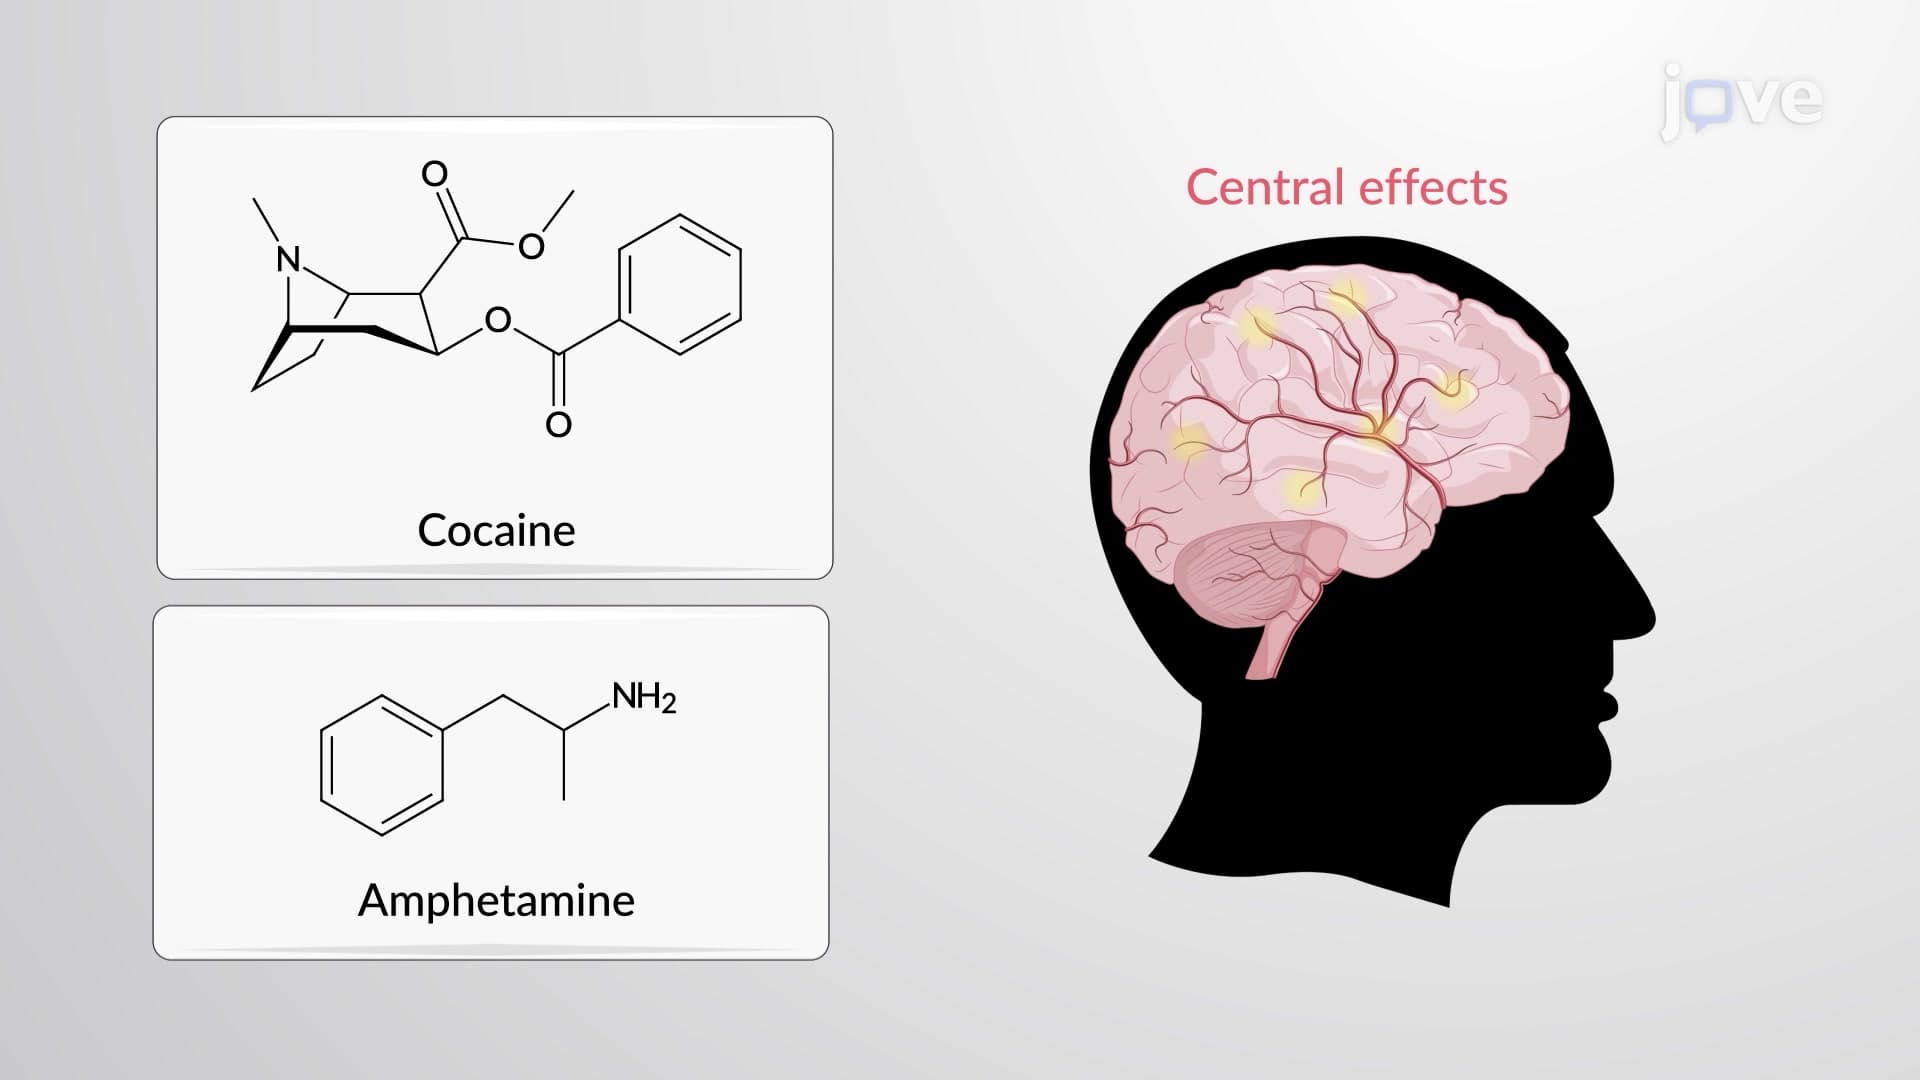
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...