Related Experiment Video
Updated: Aug 5, 2026


Estimating Bilateral Atrial Function by Cardiovascular Magnetic Resonance Feature Tracking in Patients with Paroxysmal Atrial Fibrillation
Published on: July 20, 2022
Three-Dimensional Left Atrial Geometry in Atrial Fibrillation: Imaging Biomarkers, Substrate Phenotyping, and
Paschalis Karakasis1, Panagiotis Theofilis2, Panagiotis Stachteas1
1Second Department of Cardiology, Hippokration General Hospital, Aristotle University of Thessaloniki, Konstantinoupoleos 49, 54642 Thessaloniki, Greece.

Abstract:
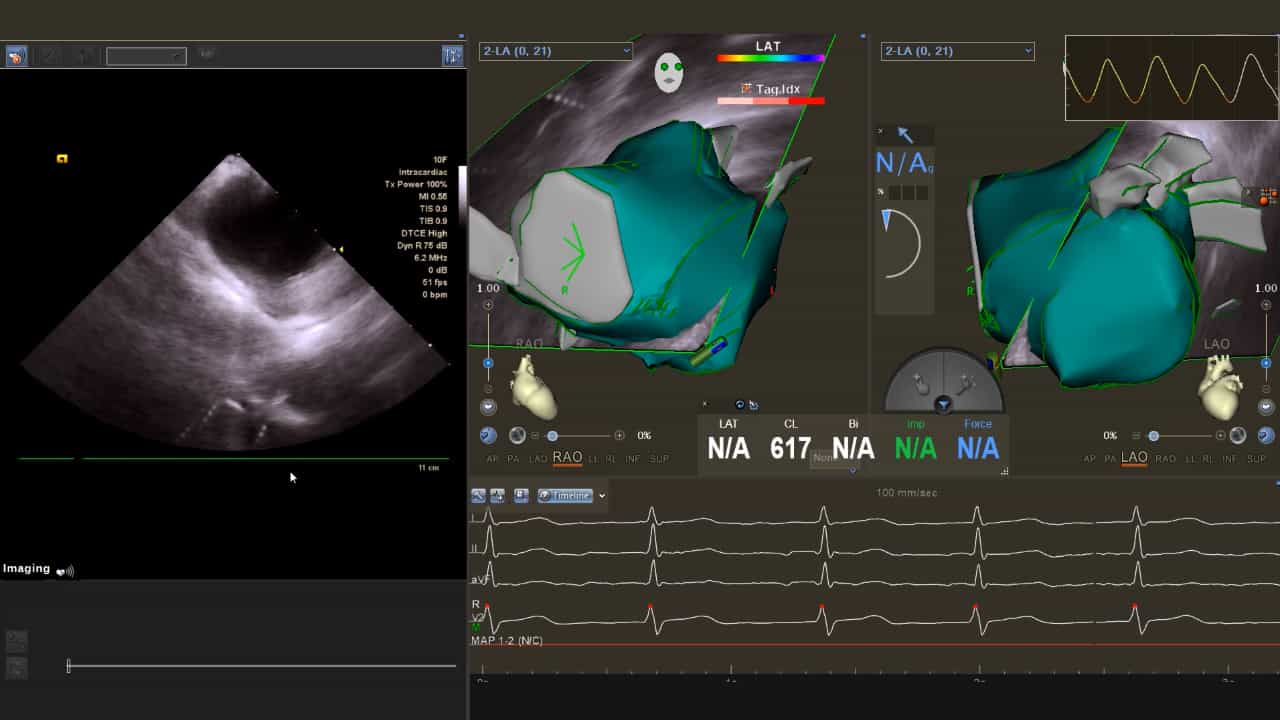
Assessment of left atrial remodeling in atrial fibrillation (AF) has traditionally relied on anteroposterior diameter, left atrial volume (LAV), and indexed left atrial volume (LAVI). Although these measures remain clinically useful, they reduce a complex, asymmetric, and anatomically constrained chamber to scalar descriptors and therefore cannot fully capture the spatial substrate that underlies AF persistence, thromboembolic risk, or arrhythmia recurrence after catheter ablation. Three-dimensional left atrial reconstruction provides a more refined framework by preserving chamber shape, regional deformation, pulmonary vein (PV) orientation, left atrial appendage (LAA) geometry, posterior wall and roof configuration, left lateral ridge anatomy, wall-thickness heterogeneity, and computational surface features. In this review, we examine how three-dimensional left atrial geometry can extend conventional remodeling assessment from measurement of atrial size toward imaging-based substrate characterization. We discuss the relative strengths and limitations of computed tomography (CT), cardiovascular magnetic resonance (CMR), three-dimensional echocardiography, and electroanatomic mapping (EAM), and summarize key geometry-derived metrics, including LAV, LAVI, left atrial sphericity, asymmetry index, atrial eccentricity index, PV anatomy, LAA morphology, posterior wall geometry, wall thickness, radiomics, and artificial intelligence (AI)-derived shape descriptors. We further synthesize evidence linking geometric remodeling with atrial cardiomyopathy, mechanical dysfunction, fibrosis, low-voltage substrate, and catheter ablation outcomes. The clinical relevance of three-dimensional left atrial geometry may be further redefined by pulsed field ablation (PFA), whose non-thermal lesion biology and tissue selectivity may modify predictors of recurrence established in radiofrequency and cryoballoon cohorts. Finally, we outline the need for standardized segmentation, harmonized metric definitions, prospective multicenter validation, and integration with AI, digital twin modeling, biomarkers, EAM data, and wearable-derived AF burden. Three-dimensional left atrial geometry is not yet a standalone determinant of ablation strategy, but it may become a central component of individualized atrial phenotyping and rhythm-control decision-making.