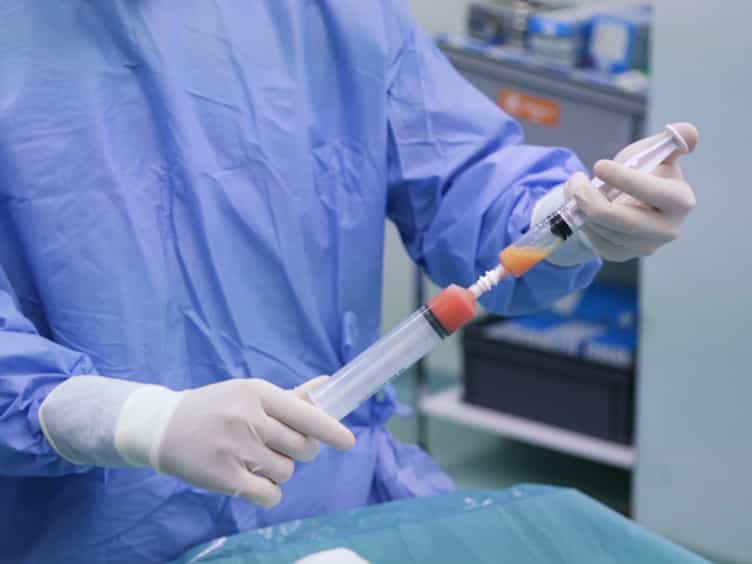
Micro-Fragmented Adipose Tissue (MFAT) in Orthopedic Regenerative Medicine: A Narrative Review of the Biological Basis and Clinical Evidence
Related Experiment Video
Updated: Aug 5, 2026

Human Adipose Tissue Micro-fragmentation for Cell Phenotyping and Secretome Characterization
Published on: October 20, 2019
Claire Yuan1, Ashu K Goyle2, Maged Guirguis3
1Department of History and Philosophy of Science, Christ's College, University of Cambridge, Cambridge CB2 3RH, UK.

Abstract:
Micro-fragmented adipose tissue (mFAT) is a promising autologous biologic in regenerative medicine because it provides a mechanically processed adipose-derived product that preserves native extracellular matrix architecture and a cellular milieu rich in mesenchymal stem cells, pericytes, growth factors, cytokines, and extracellular vesicles. Mechanistically, mFAT is hypothesized to act largely through paracrine signaling that dampens inflammation, supports vascular stabilization, and promotes cartilage and soft-tissue repair; in vitro data suggest modulation of osteoarthritic synovial macrophage signaling, including reductions in chemokines such as CCL2 and CCL3. Preparation involves liposuction harvest followed by closed, sterile mechanical processing without enzymatic digestion or cell expansion, aligning with "minimal manipulation" concepts relevant to regulatory frameworks. Preclinical animal studies generally demonstrate favorable effects on synovial inflammation and cartilage matrix markers (e.g., glycosaminoglycan content) with limited adverse events. Clinically, the strongest body of evidence is in knee osteoarthritis, where multiple prospective and retrospective studies report improvements in pain and function from months to several years after single injections, though response rates vary and study designs are heterogeneous. Evolving data support potential benefit in hip osteoarthritis and select tendon conditions, but cohorts remain small. Overall, mFAT appears safe and potentially effective, yet larger, standardized, long-term randomized controlled trials and comparative studies versus platelet-rich plasma and bone marrow aspirate concentrates are needed to clarify indications, dosing, durability, and mechanisms in vivo.