Prevalence, Timing and Mutual Relationships of Acute and Chronic Respiratory Failure in People with Chronic
Michele Vitacca1, Gaia Riboni2, Mara Paneroni1
1Respiratory Rehabilitation Unit of the Institute of Lumezzane, Istituti Clinici Scientifici Maugeri IRCCS, 25065 Lumezzane, Italy.

Abstract:
Background and aim: Prevalence, time to first diagnosis of acute (ARF) and chronic (CRF) respiratory failure in people with chronic obstructive pulmonary disease (COPD) are still unclear and were assessed in this 15-year, retrospective, observational, real-world data study. Methods: Our study examined one cohort (Cohort C1) of people older than 40 years diagnosed with COPD without any previous diagnosis of ARF. To assess the temporal relationship between ARF and CRF, two more cohorts of individuals were created: Cohort C2 included people with COPD subsequently diagnosed with CRF, without any previous diagnosis of ARF. Cohort C3 consisted of COPD people subsequently diagnosed with ARF, without any previous diagnosis of CRF. Adjusted hazard risk of and timing to first diagnosis were estimated for: i-ARF and CRF in Cohort C1; ii-ARF in Cohort C2; iii-CRF in Cohort C3. Results: Participants in Cohort C1 were equally distributed by gender, with a mean age of 66.9 ± 12.2 years and BMI 28.1 ± 7.72 kg/m2. After 15 years since COPD diagnosis, participants in Cohort C1 showed 45.25% (75th percentile reached after 7.2 years) and 21.86% (80th percentile after 13.7 years) probabilities for ARF and CRF, respectively. Participants in Cohort C2 showed an 86.78% ARF (acute-on-chronic) probability (1.7 years median time to ARF since CRF diagnosis). Individuals in Cohort C3 showed a 41.52% CRF probability (75th percentile after 3.3 years since first ARF diagnosis). Conclusions: COPD individuals reported different prevalence of and times to ARF or CRF diagnoses. Time since CRF diagnosis to first acute-on-chronic respiratory failure is shorter than time to post-ARF chronic respiratory failure. Our findings provide useful insights into periods of increased vulnerability following COPD diagnosis and respiratory failure events, which may have implications for patient monitoring and preventive strategies.
More Related Videos
 05:34
Auricular Acupuncture as a Traditional Chinese Medicine Therapy for Chronic Obstructive Pulmonary Disease Combined with Sleep Disorders
Published on: August 18, 2023
 04:03
Alternative Therapy for Acute Exacerbation of Chronic Obstructive Pulmonary Disease: Moving Cupping Along Meridians
Published on: September 27, 2024
Related Concept Videos
 01:23
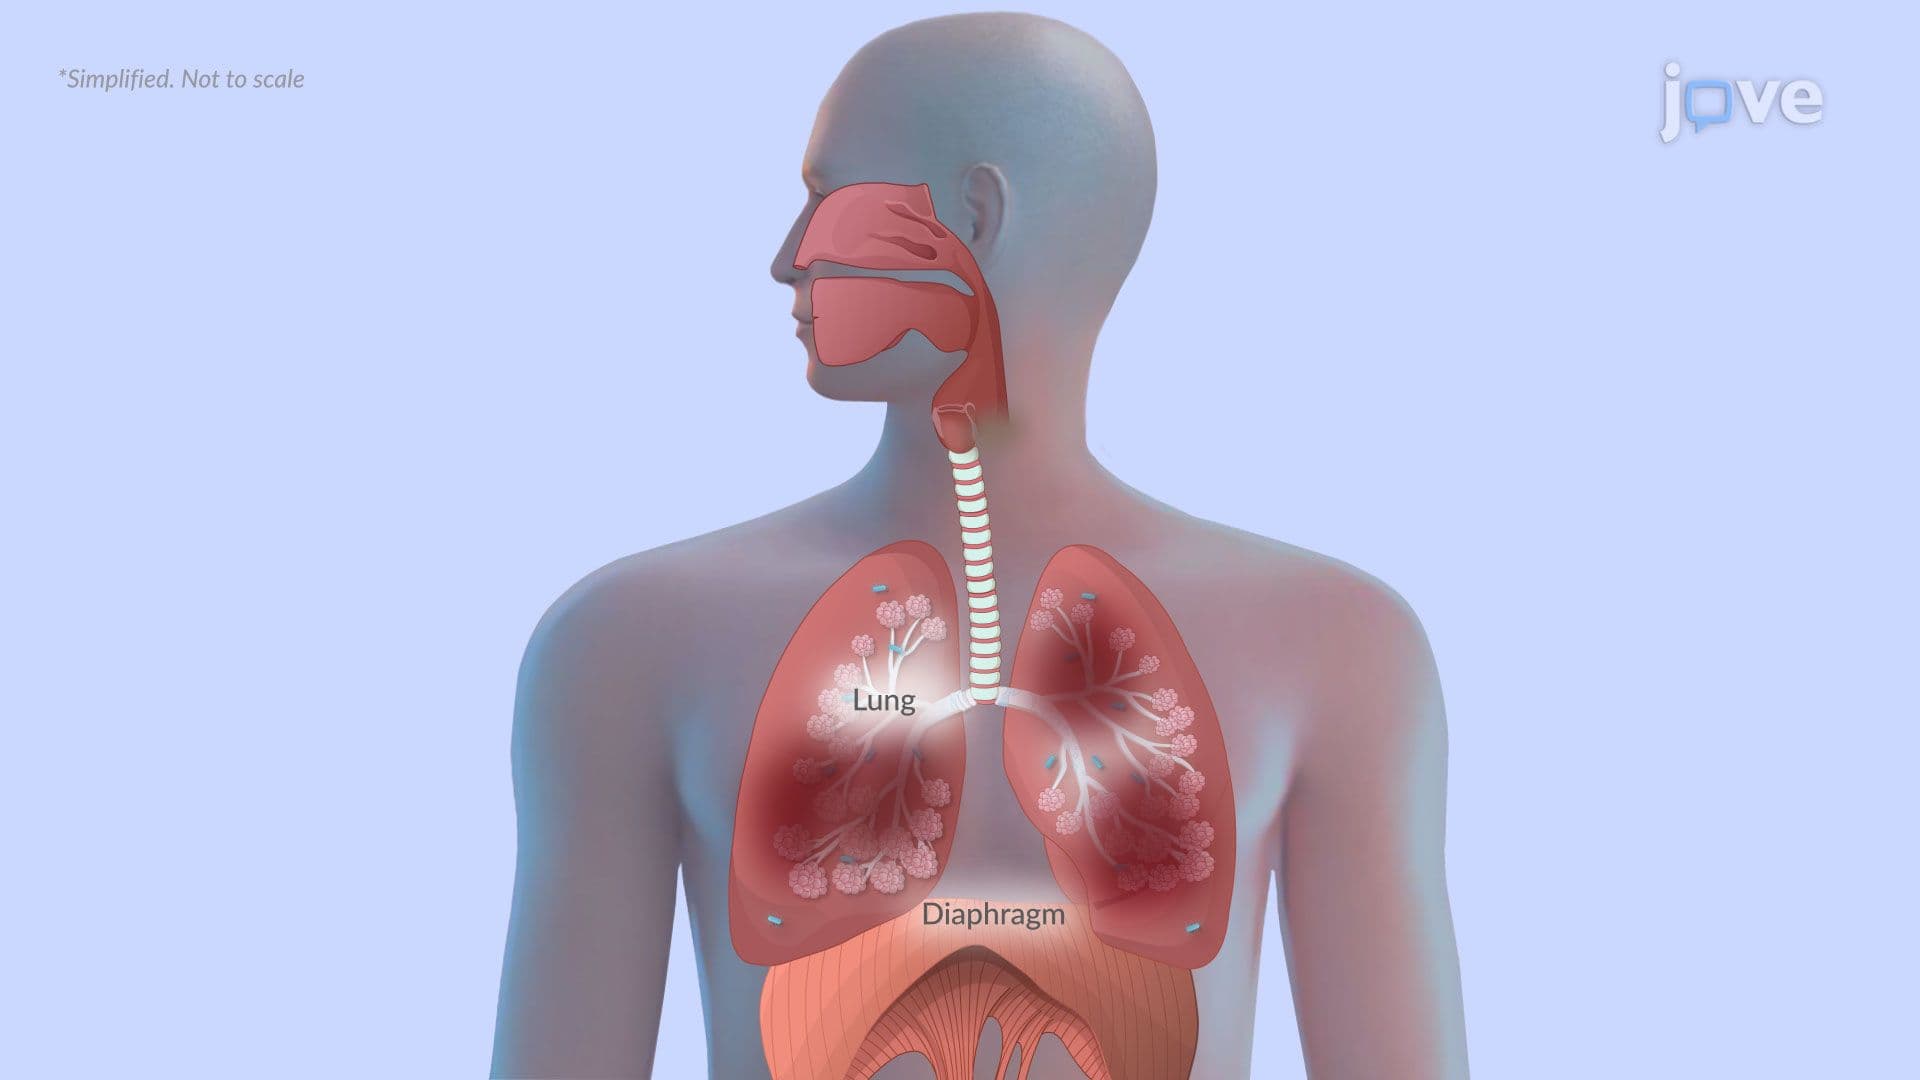
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: