Related Experiment Video
Updated: Aug 5, 2026
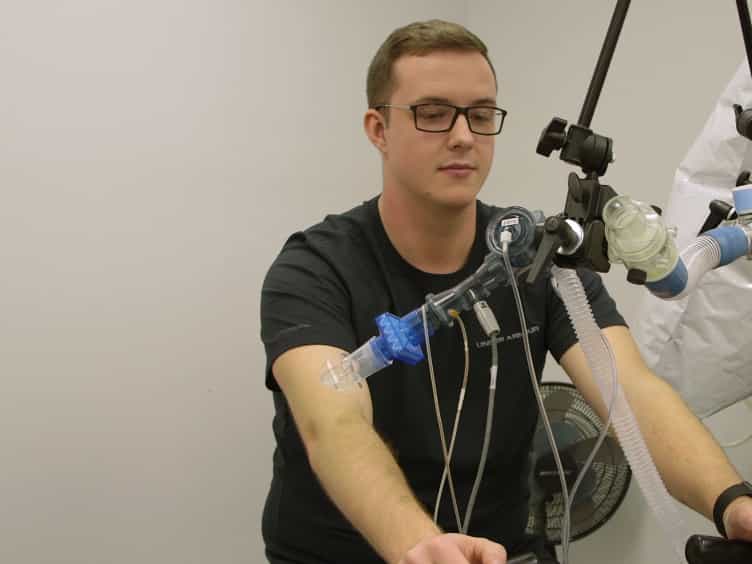
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Noninvasive Gas Exchange Determinants of Exercise Hemodynamics in Non-Severe Pulmonary Hypertension Associated With
Chebly Dagher1, Niala Moallem2, Garrett Fiscus3
1Department of Internal Medicine University of Connecticut Farmington Connecticut USA.

Abstract:
Level 3 cardiopulmonary exercise testing (CPET) can unmask the dynamic burden of pulmonary vascular disease (PVD), while submaximal exercise testing offers a simpler, noninvasive alternative. Emerging markers such as a gas-exchange derived estimate of pulmonary vascular capacitance (GXCAP) and ventilatory efficiency (VE/VCO2) may reflect PVD and correlate with invasive hemodynamics. Level 3 CPET has been used to stratify PH-ILD patients into those with exercise-induced increases in pulmonary vascular resistance (PVRD) and those with static PVR (PVRS). This study evaluated whether GXCAP and VE/VCO2 measured during submaximal testing could identify non-severe PH-ILD patients with exercise-induced increases in PVR. GXCAP and VE/VCO2 were retrospectively analyzed in 16 non-severe PH-ILD patients who underwent both submaximal exercise testing and invasive Level 3 CPET. Patients were previously categorized as having dynamic (PVRD) or stable (PVRS) PVR responses. Between-group differences were assessed using unpaired t-tests, and receiver operating characteristic (ROC) analysis evaluated the ability of each variable to identify the PVRD phenotype. Among the 16 patients included in the analysis, 6 were classified as PVRS and 10 as PVRD. Baseline characteristics, including peak VO2, were similar between groups. Mean GXCAP was significantly higher in PVRS (471 ± 85 mL·mmHg) than in PVRD (311 ± 38 mL·mmHg, p < 0.01), while VE/VCO2 was lower in PVRS (33 ± 2 vs 37 ± 2.5, p < 0.01). ROC analysis demonstrated excellent discriminatory performance for GXCAP (AUC 0.98) and good discrimination for VE/VCO2 (AUC 0.90). The GXCAP/VE/VCO2 ratio performed similarly (AUC 0.98). These findings suggest that GXCAP and VE/VCO2 obtained during submaximal testing may serve as practical, noninvasive tools for identifying exercise-induced pulmonary vascular impairment and aiding risk stratification in patients with non-severe PH-ILD. However, validation in larger prospective cohorts is needed.
More Related Videos

Related Concept Videos
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:18
Pulmonary Edema II: Pathophysiology
 01:24
External and Internal Respiration
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...