The Prognostic Value of Baseline PSA Density on Long-term Oncological Outcomes in Men with an Initial Negative Prostate Biopsy: Results from ERSPC Rotterdam
Related Experiment Video
Updated: Aug 5, 2026
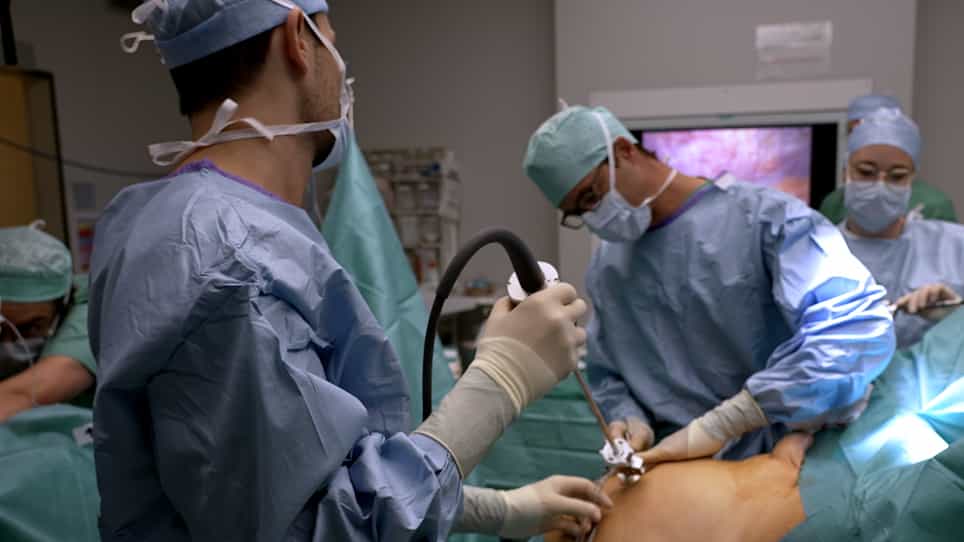
Retzius-Sparing Robot-Assisted Radical Prostatectomy
Published on: May 19, 2022
Meike J van Harten1, Sebastiaan Remmers1, Ivo I de Vos1
1Department of Urology, Erasmus MC Cancer Institute, University Medical Center Rotterdam, The Netherlands.

Introduction:
Baseline prostate-specific antigen (PSA) is associated with the risk of metastatic disease (M+) and prostate cancer (PCa)-specific mortality (PCSM). However, the prognostic value of baseline PSA density (PSA-D) for long-term oncological outcomes is less well established. This study aims to evaluate the prognostic value of baseline PSA-D for oncological outcomes in men who participated in a population-based screening study and had an elevated PSA but a negative prostate biopsy at their first screening visit.
Material And Methods:
Data from the Rotterdam cohort of the European Randomized Study of Screening for Prostate Cancer (ERSPC) were used. All men aged 55-69 yr with PSA ≥ 3 ng/ml following a negative (sextant) biopsy at initial screening were included. Screening was repeated every 4 yr, with (repeat) biopsy if PSA ≥ 3 ng/ml. Screen-detected PCa was defined as PCa diagnosed during scheduled screening rounds. Men were stratified into three age groups according to the maximum number of potential screening rounds: 55-59, 60-64, and 65-69, and three baseline PSA-D groups reflecting clinical practice: <0.10, 0.10-0.15, and ≥0.15 ng/ml2. Cumulative incidences (CIs) of indolent PCa, clinically significant PCa (csPCa) defined as Grade Group ≥2, M+ disease, and PCSM were assessed for each stratum at 21 yr after initial negative biopsy.
Results:
In total, 1565 men met the inclusion criteria: 55-59 (n = 368), 60-64 (n = 535), 65-69 (n = 662), with a median follow-up of 21 yr. A total of 268 men were diagnosed with PCa, of whom 66 had csPCa; 138 PCa cases were screen-detected, including 19 cases of csPCa. At 21 yr, the CI of M+ disease ranged from 0.3% to 5.2%, with the highest incidence in men aged 60-64 with PSA-D ≥ 0.15 ng/ml2 (5.2%, 95% CI: 1.9-11). PCSM was lowest in men with PSA-D < 0.10 ng/ml2, regardless of age group: <0.001% for men aged 55-59 and 65-69, 0.8% for men aged 60-64.
Conclusions:
Baseline PSA-D is a useful tool for identifying a group of men at low risk of future oncological events after an initial negative biopsy. Although continued screening may have contributed to low CI of oncological outcomes, the limited number of screen-detected csPCa during follow-up screening rounds supports the use of baseline PSA-D for risk stratification and de-escalation of repeat testing. Men aged 55-59 with a baseline PSA-D < 0.10 ng/ml2 after a negative prostate biopsy could be subject to extended screening intervals in a screening setting. Further validation in modern diagnostic settings is needed before firm clinical recommendations can be made.
