Antimicrobial Management of Severe Chlamydia psittaci Pneumonia in Adults: A Narrative Review
Lujun Shao1,2, Gaochao Lv3, Yi Yuan3
1Department of Intensive Care Unit, The Affiliated Taizhou People's Hospital of Nanjing Medical University, Taizhou, 225300, People's Republic of China.

Abstract:
Chlamydia psittaci is an obligate intracellular bacterium and an increasingly recognized cause of severe community-acquired pneumonia (CAP) in adults, with contemporary multicenter Chinese cohorts reporting severe-stratum in-hospital mortality clustering around 8-9% and higher figures in acute respiratory distress syndrome (ARDS)-enriched series. β-Lactam therapy lacks reliable activity against this pathogen, yet considerable practice variation persists in the selection, sequencing, and de-escalation of intracellularly active agents in the era of routine metagenomic and targeted next-generation sequencing (mNGS, tNGS). The aim of this review is to provide a phase- and severity-stratified, bedside antimicrobial framework for severe psittacosis in adults-clarifying when to select, continue, switch, or combine intracellularly active agents at the 48- to 72-hour ICU decision points. This narrative review, reported in accordance with the SANRA framework, synthesizes the post-2015 antimicrobial evidence for severe C. psittaci pneumonia in adults and integrates treatment phase (empirical versus targeted), severity context, organ support, and antimicrobial stewardship at the 48- to 72-hour ICU decision points. Drawing on six multicenter cohorts and the largest dedicated multicenter dataset to date (Fang 2026, n = 186; severe-stratum mortality 7/81 = 8.6%), phase-by-severity stratification reconciles apparently discordant tetracycline- and fluoroquinolone-favoring cohort signals. Doxycycline is the preferred targeted backbone in confirmed non-pregnant disease; reflex class-switching is not required when severely ill patients are already improving on an empirical fluoroquinolone at NGS confirmation. Omadacycline is a renal-sparing alternative when acute kidney injury, anticipated continuous renal replacement therapy, or unreliable doxycycline access alters the standard pathway; high-dose tigecycline is reserved for salvage; azithromycin retains its clearest targeted role in pregnancy. Apparent nonresponse at 72 hours should trigger structured reassessment for coinfection, secondary organizing pneumonia, pulmonary embolism, and inadequate antimicrobial exposure before any salvage escalation. Adjunctive corticosteroid use should follow contemporary severe-CAP guidance pending pathogen-specific data from the NCT07352865 adaptive trial. Recommendations are calibrated using GRADE-adapted certainty and strength, with explicit acknowledgment that the comparative evidence base remains overwhelmingly retrospective and geographically concentrated in Chinese tertiary hospitals.
Related Concept Videos
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:29
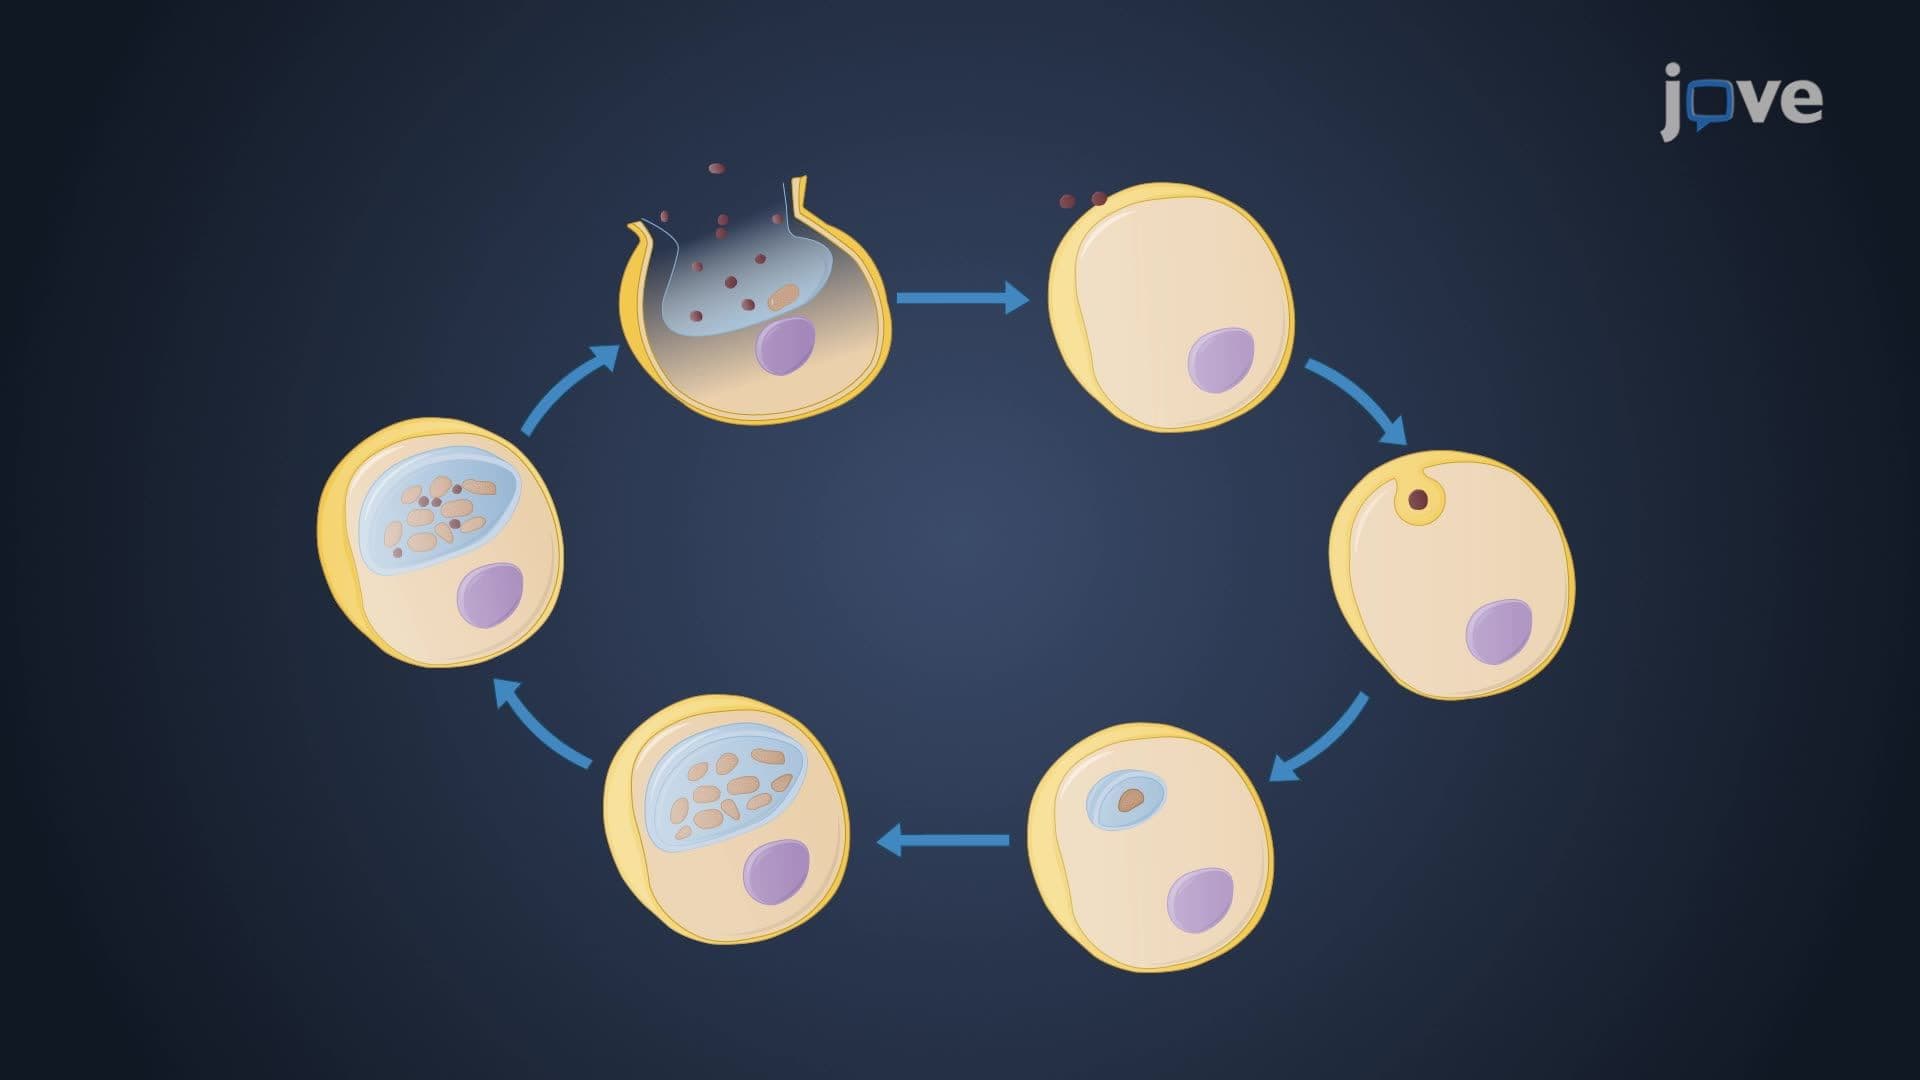
Bacterial Phylum Chlamydiae
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:14
Atypical Pneumonia
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:30
Pneumonia III: Complications and Assessment