Related Experiment Video
Updated: Aug 5, 2026
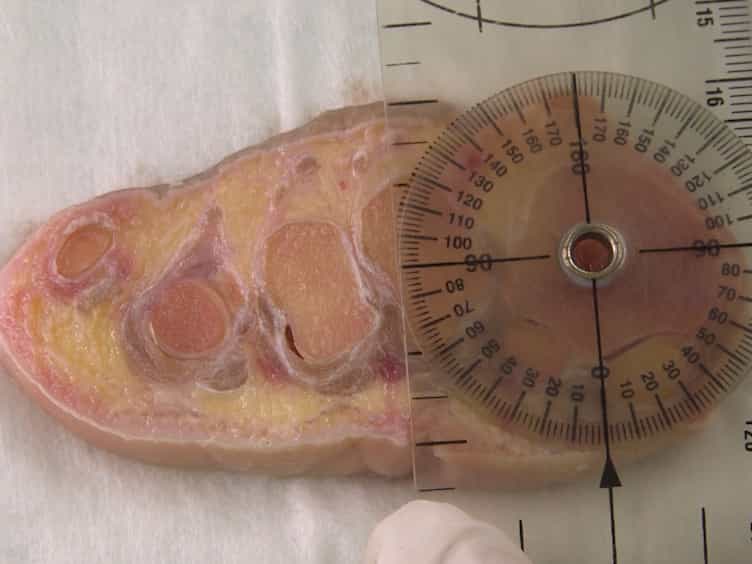

An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Long-acting narcotic multimodal anesthesia versus standard of care anesthesia for hallux valgus patients undergoing a
Shayan Karimi1, Dena Bakhsh2, Lucy Luo3
1Faculty of Medicine and Health Sciences, McGill University, Montréal, QC, Canada.

Background:
Hallux valgus surgery often results in significant post-operative pain, requiring narcotics. Optimizing pain management while minimizing opioid consumption remains an important clinical challenge.
Purpose:
This study investigates whether multimodal analgesia (acetaminophen, naproxen, and pregabalin) with the use of long-acting tramadol reduces the need for short-acting narcotics following minimally invasive hallux valgus surgery under regional ankle block anesthesia.
Study Design/Methods:
A total of 114 patients aged 18-70 with BMI ≤ 40 undergoing hallux valgus surgery were randomized into Experimental (Exp) and Standard (S) groups. The Exp group (n = 56) received acetaminophen, naproxen, pregabalin, and Ralivia (tramadol extended release) pre-operatively, along with a post-operative regimen including rescue hydromorphone. The S group (n = 58) followed standard protocols with hydromorphone as the primary analgesic. Pain (VAS scores) and short-acting narcotic use were recorded post-operatively, alongside steps and sleep using smartwatches. Two-sided t-tests compared VAS scores and narcotic consumption.
Results:
Exp patients used significantly fewer short-acting narcotics in the first week, averaging 5.24 hydromorphone pills (20.96 MME) vs. 13.53 hydromorphone pills (54.12 MME) in the S group (p < 0.0005), however the Exp group consumed a higher overall MME. Notably, of all patients in the study, 27.2% did not consume any short-acting narcotics post-operatively (43.1% in Exp group and 10.7% in S group). Pain scores at 24 and 48 hours were significantly less in the Exp group (p = 0.001, p = 0.012), but the difference was minimal and not clinically significant. Steps and sleep were comparable between groups.
Conclusion:
Multimodal analgesia with long-acting narcotics in minimally invasive surgery was associated with reduced short-acting narcotic use, but higher overall MME compared to the standard protocol.