Related Experiment Video
Updated: Aug 5, 2026

Murine Distal Colostomy, A Novel Model of Diversion Colitis in C57BL/6 Mice
Published on: July 12, 2018
Diversion ostomy improves treatment tolerance, conversion surgery, and survival compared with self-expanding metal
Fengbin Cai1, Weiming Jiang2, Huali Cai1
1Department of Gastrointestinal Surgery, Xiamen Humanity Hospital, Fuiian Medical University, Xiamen, China.

Background:
The optimal decompression strategy for patients with initially non-resectable obstructive colorectal cancer undergoing conversion intent treatment remains unclear. This study compared diversion ostomy (DO) and self-expanding metal stent (SEMS) placement.
Methods:
Data from 115 patients with initially non-resectable obstructive colorectal cancer, who were treated between June 2021 and June 2025, were retrospectively reviewed. Sixty-two patients underwent DO, and 53 underwent SEMS as the initial decompression strategy. After decompression, patients received oxaliplatin and oral capecitabine (i.e., "CAPEOX")- or folinic acid, fluorouracil, and oxaliplatin (i.e., "FOLFOX")-based systemic therapy with targeted therapy, with or without immunotherapy, according to molecular and immunohistochemical findings. Clinical outcomes, nutritional and inflammatory indices, tumor response, subsequent resection, and overall survival (OS) were compared between the two groups.
Results:
DO was associated with a significantly higher rate of achievement of Colorectal Obstruction Scoring System (CROSS) score 3 than SEMS (85.5% versus [vs.] 47.2%; P<0.001), and a higher number of chemotherapy cycles (median, 6 vs. 2; P<0.001). Post-treatment nutritional and inflammatory profiles were more favorable in the DO group, with higher Prognostic Nutritional Index (≥45) rates and lower platelet-to-lymphocyte and neutrophil-to lymphocyte ratios (all P ≤ 0.005). The objective response and subsequent resection rates were significantly higher in the DO group than that in the SEMS group (69.4% vs. 30.2%; P<0.001), as was the subsequent resection rate (69.4% vs. 30.2%; P<0.001), respectively. Kaplan-Meier analysis revealed significantly longer OS in the DO group, with a median survival of 27.8 vs. 10.3 months (P<0.0001). In multivariate analysis, SEMS remained independently associated with worse OS than DO (hazard ratio 2.231 [95% confidence interval 1.345-3.842; P = 0.001).
Conclusions:
In patients with initially non-resectable obstructive colorectal cancer treated with conversion intent, DO was associated with better decompression, improved treatment tolerance, higher resection rates, and longer survival than SEMS placement.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:24
Ostomy Care
An ostomy is a surgical procedure that creates an artificial opening from the intestines to the outside of the body, allowing for the rerouting of effluent. This opening is known as a stoma. A stoma usually protrudes above the skin surface, appearing pink or red, moist, and round, and it lacks nerve sensations.
There are different types of ostomies, including colostomies, ileostomies, and urostomies:
 01:27
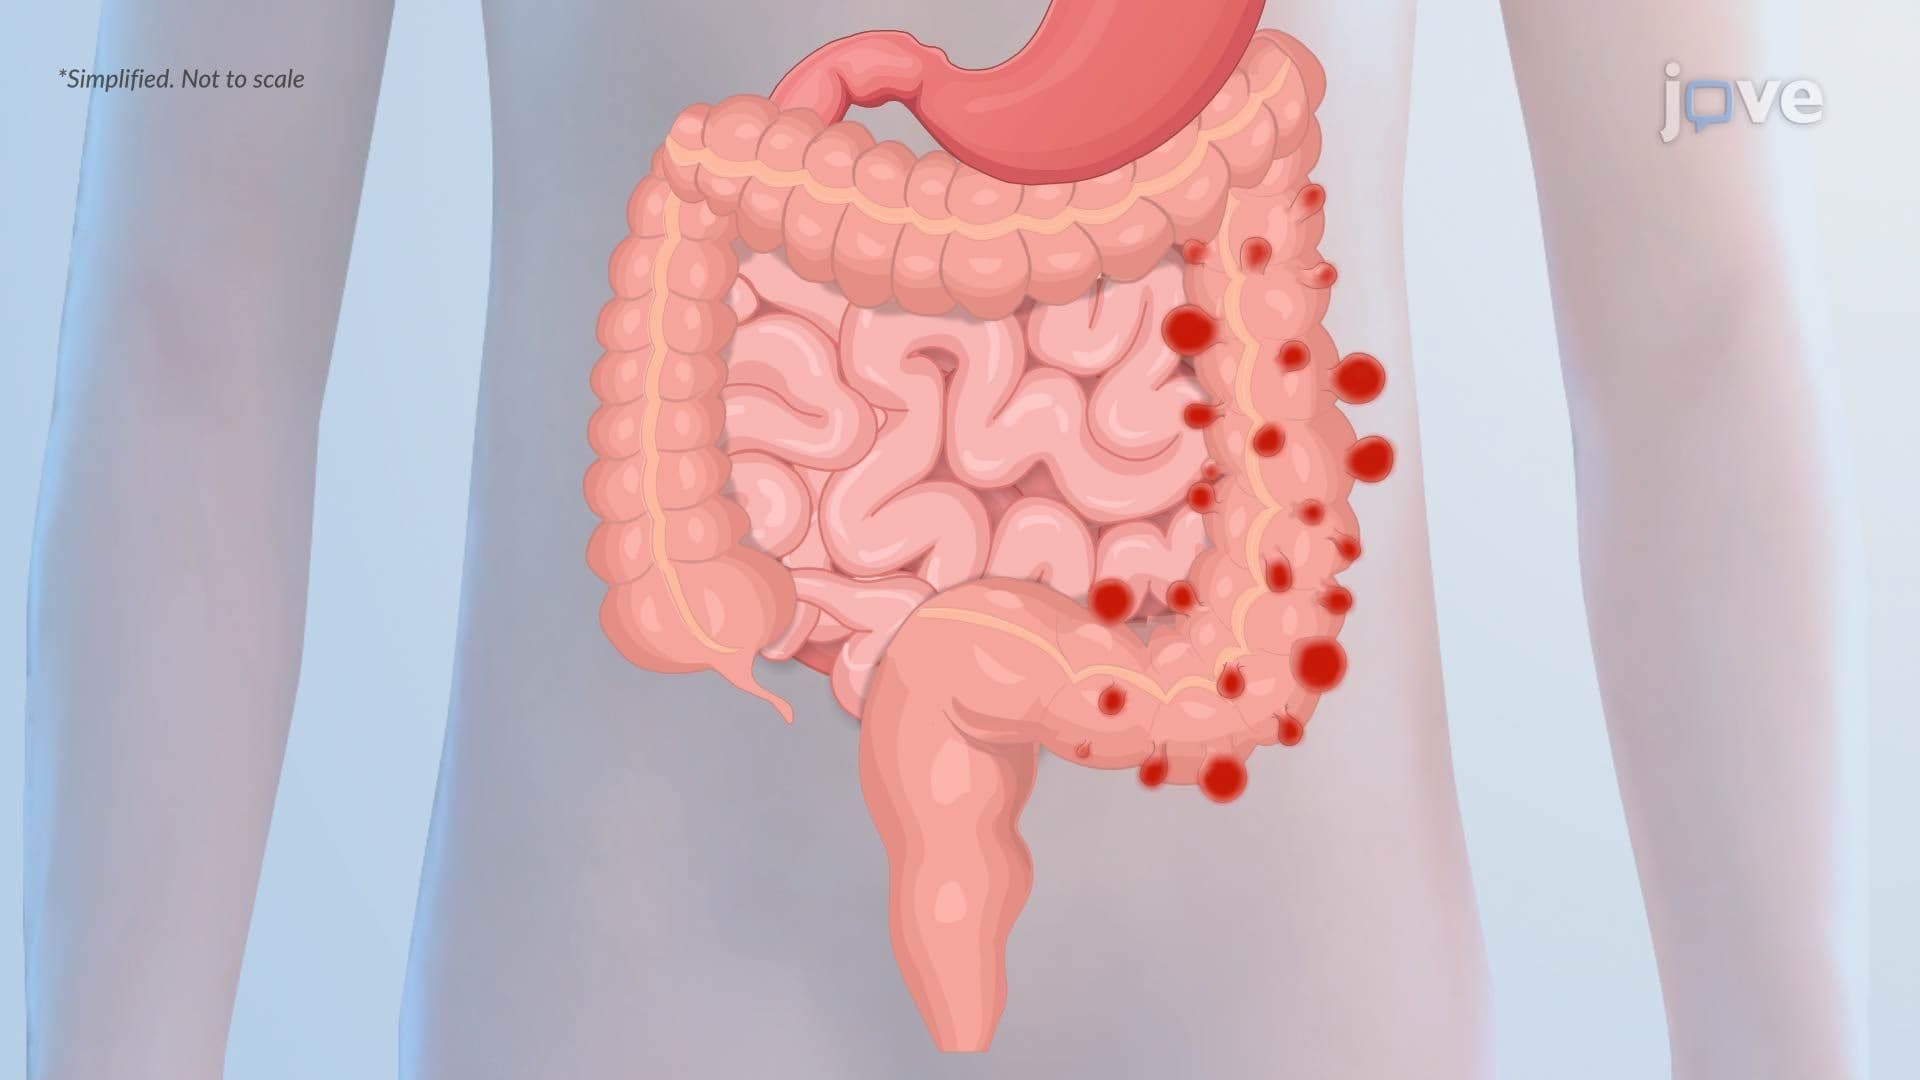
Diverticular Disease of the Colon
 01:29
Drugs for Treatment of Ulcerative Colitis in IBD
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease