Related Experiment Video
Updated: Aug 5, 2026
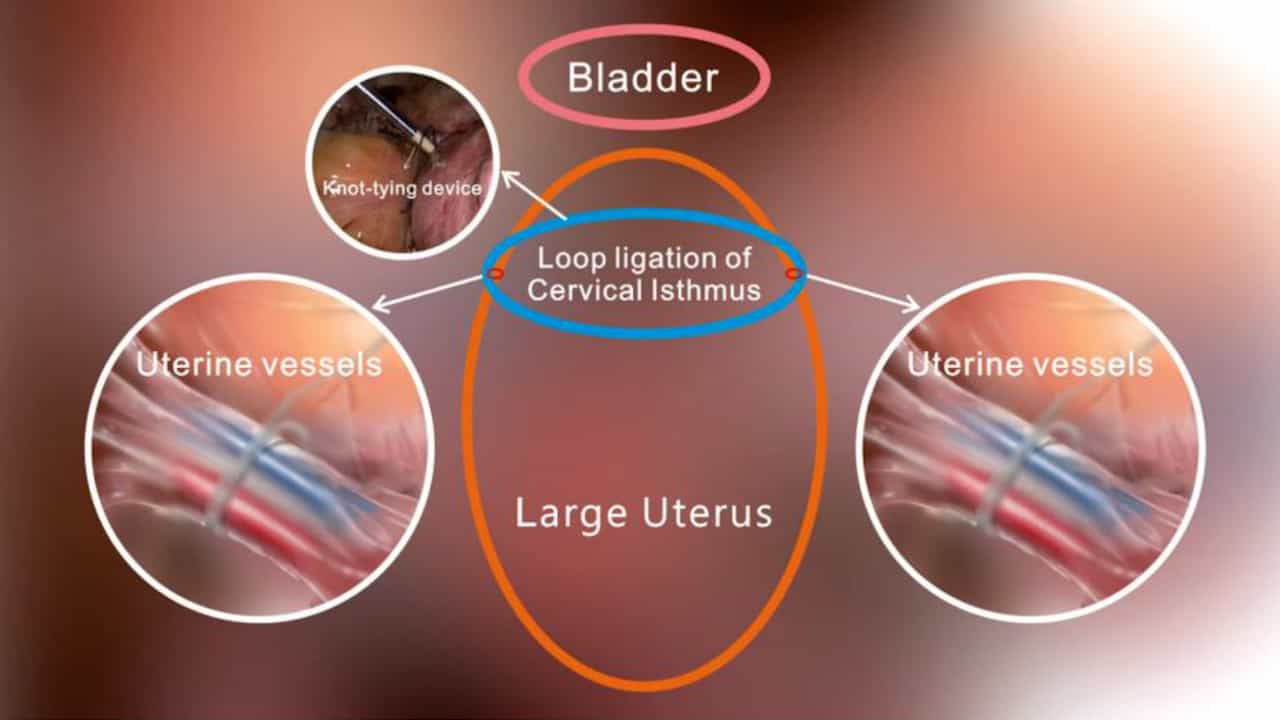

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Perioperative outcomes and learning curves of minimally invasive hysterectomy: a comparative analysis of MPLH, RASPH,
Ying Zhang1, Xiaofeng Xu1, Wenyou Zhu1
1Department of Gynecology and Obstetrics, Jiading District Central Hospital Affiliated Shanghai University of Medicine & Health Sciences, Shanghai, China.

Objective:
To compare perioperative safety, efficiency and learning curves of MPLH, RASPH and SPLH, and analyze surgical disparities stratified by uterine volume. We adopted multivariable regression (primary adjusted analysis) and multinomial IPTW weighting (sensitivity analysis) to correct indication confounding; though IPTW failed to balance baseline covariates and could not achieve adequate covariate balance, both adjusted methods yielded consistent outcomes.
Methods:
This single-center retrospective cohort enrolled 280 patients (118 MPLH, 35 RASPH, 127 SPLH). We compared intraoperative metrics, early recovery indicators, 30-days complications and CUSUM learning curves, stratifying patients into simple (<200 cm3) and complex (≥200 cm3) uterine subgroups. Raw comparisons were supplemented by two covariate-adjusted models controlling for uterine volume, BMI, pelvic adhesions and benign/malignant pathology.
Results:
Unadjusted operative time differed markedly (Kruskal-Wallis P < 0.001): MPLH 83.9 [80.7, 125.0] min, RASPH 166.0 [137.0, 170.0] min, SPLH 102.0 [88.5, 107.0] min. Robotic console time excluded docking steps. After adjustment, RASPH independently required longer operating time, with comparable efficiency between MPLH and SPLH. Unadjusted blood loss varied significantly (P < 0.001): MPLH 126 [115, 140] mL, RASPH 134 [93.5, 143] mL, SPLH 156 [146, 170] mL. Raw blood loss was similar between MPLH and RASPH, yet SPLH lost more blood; adjustment confirmed equivalent hemorrhage for MPLH and RASPH. Hospital stay and POD1 pain scores were comparable (all P > 0.05), and 30-days complication rates were balanced (3.4% vs. 5.7% vs. 3.1%, P = 0.79). RASPH took longer in both uterine subgroups, but its complex subgroup only contained seven patients with limited statistical power. CUSUM inflection points were 15 (MPLH), 19 (SPLH) and 23 (RASPH); only 12 robotic cases fell after the threshold, weakening plateau reliability.
Conclusion:
The three techniques shared similar short-term safety. Adjusted data identified prolonged operative time for RASPH, while MPLH and SPLH had equivalent efficiency. SPLH was associated with greater intraoperative bleeding, whereas blood loss was comparable between MPLH and RASPH. Severe baseline imbalance restricts causal subgroup interpretation. MPLH and SPLH reached proficiency faster, offering evidence for personalized surgery and tiered training; prospective balanced cohorts are needed for further validation.