Related Experiment Video
Updated: Aug 5, 2026
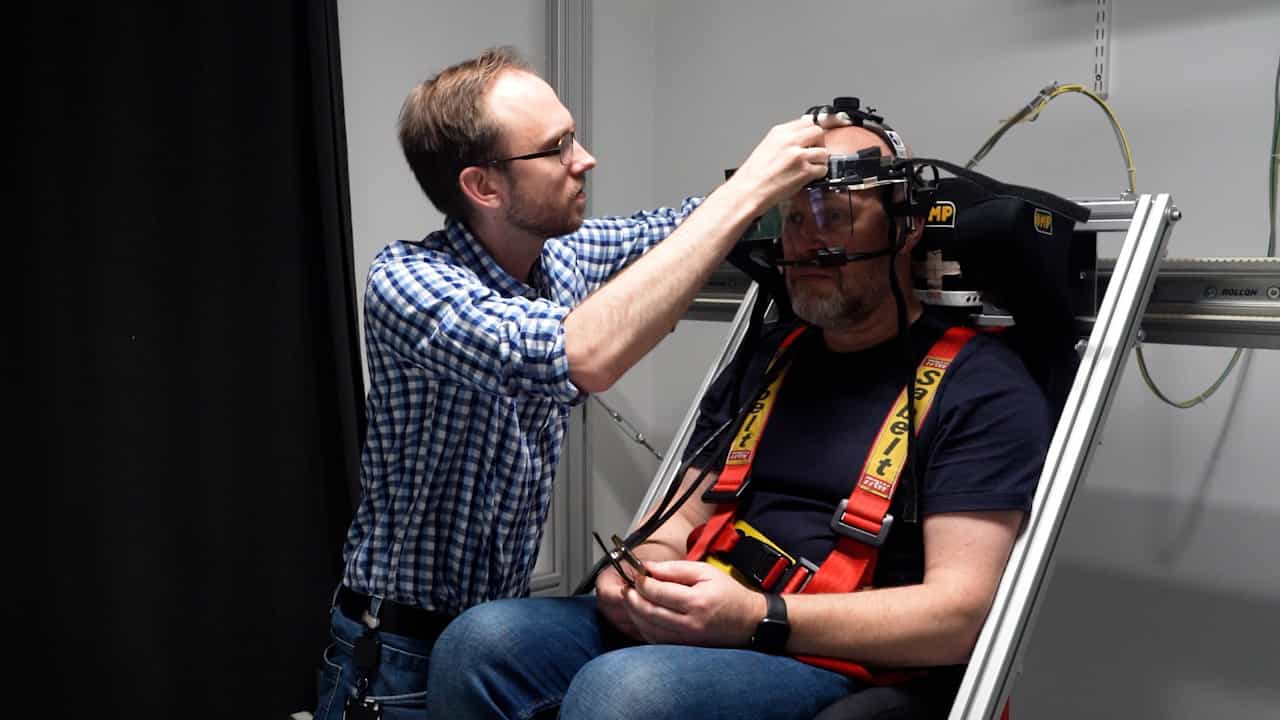

Using Eye-tracking to Assess the Relative Importance of Visual and Vestibular Input to Subcortical Motion Processing in the Roll Plane
Published on: August 22, 2025
Altered spontaneous brain activity and functional connectivity in persistent postural-perceptual dizziness
Jinghan Qin1,2, Weitao Wang1,2,3, Liya Shen2
1Encephalopathy Department, The First Affiliated Hospital of Henan University of Chinese Medicine, Zhengzhou, China.

Background And Purpose:
Persistent postural-perceptual dizziness (PPPD) is a chronic functional vestibular disorder characterized by persistent dizziness or postural instability that is exacerbated by upright posture, motion, and complex visual stimuli. Although neuroimaging studies suggest altered visual, vestibular, and emotional processing in PPPD, comprehensive resting-state functional magnetic resonance imaging evidence remains limited. This study investigated spontaneous brain activity and functional connectivity alterations in patients with PPPD.
Methods:
Twenty-one patients with PPPD and 23 healthy controls underwent 3.0 Tesla resting-state functional magnetic resonance imaging. Regional spontaneous brain activity and local synchronization were assessed using low-frequency fluctuation and regional homogeneity measures. Seed-based functional connectivity analyses were performed using the left insula, right anterior cingulate cortex, and left precuneus as seed regions. Between-group differences were tested with age and sex as covariates, and exploratory clinical-imaging correlation analyses were conducted in the patient group.
Results:
Patients with PPPD showed altered spontaneous activity and local synchronization in the cerebellum, occipital and temporal cortices, frontal and parietal regions, anterior cingulate cortex, insula, precuneus, and motor-related areas. Functional connectivity analyses revealed abnormal connections among the insula, caudate nucleus, prefrontal cortex, supplementary motor area, anterior and posterior cingulate cortices, precuneus, fusiform gyrus, and superior temporal gyrus. Clinical-imaging correlation analyses further showed that disease duration, dizziness handicap, anxiety severity, and cognitive performance were associated with functional changes in visual, cerebellar, supplementary motor, superior parietal, cuneus, and precuneus regions.
Conclusion:
These findings indicate that PPPD involves distributed functional abnormalities in brain regions responsible for vestibular and postural integration, visual-spatial processing, emotional and salience monitoring, motor regulation, and self-referential cognitive processing. Abnormalities in these regions may contribute to persistent dizziness, postural instability, visual dependence, heightened symptom vigilance, anxiety-related symptom amplification, and insufficient postural-motor compensation. Thus, PPPD may be better understood as a distributed network disorder involving disrupted visual-vestibular-postural integration and maladaptive functional reorganization.


