Related Experiment Video
Updated: Aug 5, 2026
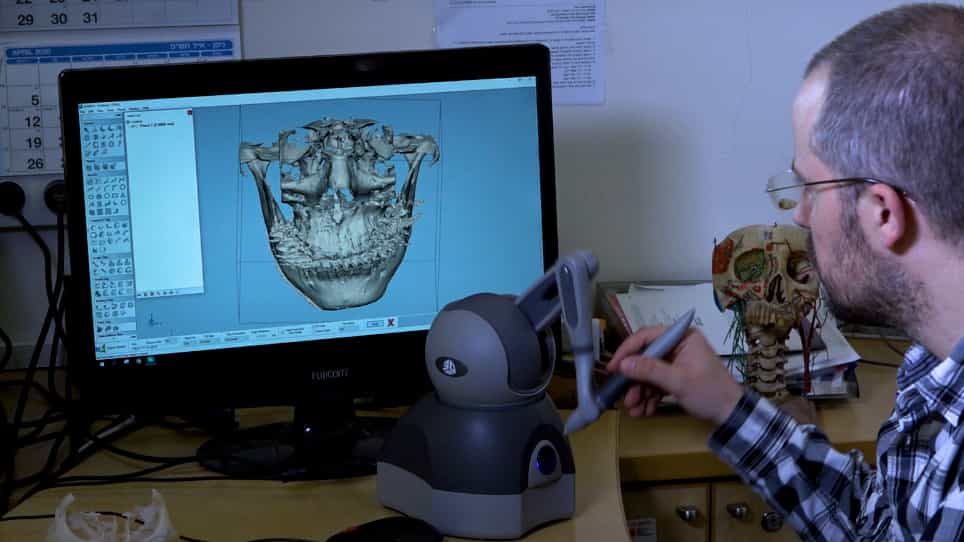

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Comparative Meta-Analysis of Complications of Maxillomandibular Advancement for OSA versus Orthognathic Surgeries for
Mohamed Faisal Kassir1, Angelica Walker1, Lauren A Howser1
1Department of Otolaryngology-Head and Neck Surgery, Medical University of South Carolina, 135 Rutledge Avenue, MSC 500, Charleston, 29425, South Carolina, USA.

Objective:
Maxillomandibular advancement (MMA) surgeries for obstructive sleep apnea (OSA) and orthognathic surgeries for dentofacial deformities (DFDs) are both complex procedures with distinct indications. This meta-analysis and systematic review aimed to compare complications and recovery metrics between these surgeries.
Data Sources:
CINAHL, Cochrane Library, PubMed, and SCOPUS.
Review Methods:
Included studies focused on MMA for OSA or orthognathic surgeries for DFDs. Included were 18 bimaxillary studies (n = 1734), 10 single-jaw (n = 3847), and 17 MMA studies (n = 601). Outcomes analyzed included operative time, hospital stay, and complications such as neurosensory disturbance, infection, and hardware removal.
Results:
MMA demonstrated a surgical success rate of 79.6% and a cure rate of 39%. Compared to bimaxillary surgery, MMA was associated with longer operative time (343.87 vs 326.95 min; P = .021) and postoperative hospital stay (4.22 vs 3.25 days; P < .0001). Neurosensory disturbance was comparable between MMA (40.44%) and bimaxillary surgeries (44.91%; P = .2189), but highest in single-jaw procedures (55.18%; P < .001). MMA had higher postoperative infection (16.34%) and hardware removal rates (21.99%) than bimaxillary surgery (3.55% and 4.21%, respectively; P < .0001). Postoperative OSA developed in 12.25% of bimaxillary cases for DFDs.
Conclusion:
Our findings underscore the need for tailored preoperative counseling and risk stratification when selecting orthognathic surgical interventions. MMA offers a high surgical success rate but is associated with longer operative time, increased hospital stay, and higher rates of infection and hardware removal compared to bimaxillary and single-jaw surgeries. These findings highlight the need to balance efficacy with complication risk when selecting surgical approaches for OSA or DFDs.