Related Experiment Video
Updated: Aug 5, 2026
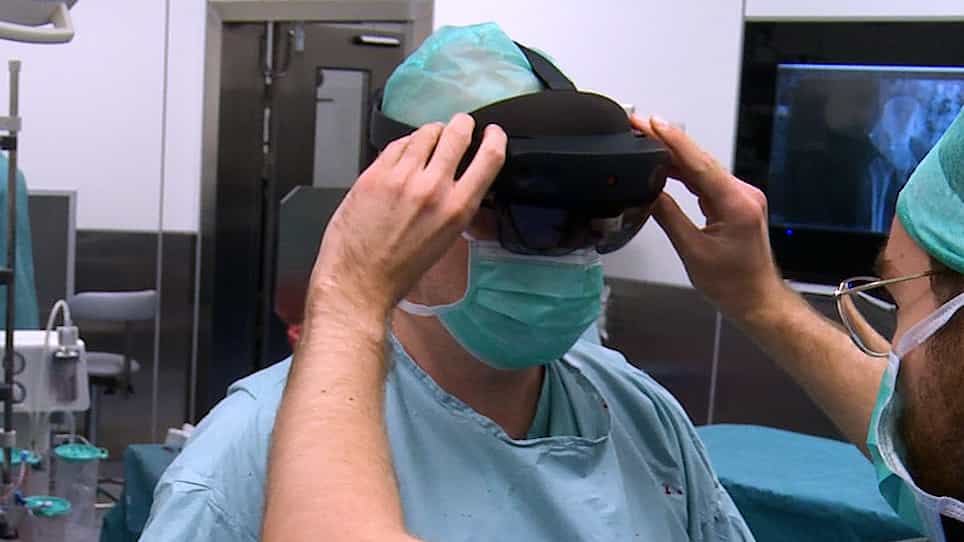

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Autologous impaction bone grafting of a cemented acetabular component in primary total hip arthroplasty in young
Diederik R de Boer1, Patricia Pasman1, Roelina Munnik-Hagewoud1
1Department of Orthopaedics, Isala Hospital, Zwolle, The Netherlands.

Insights
Autologous impaction bone grafting (IBG) in primary total hip arthroplasty (THA) for young patients is noninferior to standard fixation. IBG improves radiological fixation and component positioning, potentially enhancing long-term survival.
Area of Science:
- Orthopedic Surgery
- Biomaterials Science
- Radiology
Background:
- Primary total hip arthroplasty (THA) is a common procedure for hip osteoarthritis.
- Acetabular component fixation is crucial for long-term implant survival.
- Autologous impaction bone grafting (IBG) is a technique used to augment bone stock in THA.
Purpose of the Study:
- To compare clinical and radiological outcomes of cemented acetabular components in primary THA for patients under 60.
- To evaluate the efficacy of autologous impaction bone grafting (IBG) versus standard fixation.
- To assess the noninferiority of IBG for functional outcomes at one-year follow-up.
Main Methods:
- A single-centre, triple-blinded randomized controlled trial (RCT) involving 131 patients aged 18-59.
- Patients undergoing primary THA without acetabular defects were randomized to IBG or no IBG.
- Primary endpoint: Hip disability and Osteoarthritis Outcome Score (HOOS) for activities of daily living (ADL) at one year. Secondary outcomes included PROMs, perioperative data, complications, and radiological assessments.
Main Results:
- No significant difference in HOOS-ADL scores between groups, meeting noninferiority criteria for IBG.
- IBG group showed significantly longer surgery duration and increased blood loss.
- Radiologically, IBG reduced radiolucent lines and improved centre of rotation positioning compared to controls.
Conclusions:
- Autologous IBG with a cemented acetabular component in primary THA for young patients is clinically noninferior to standard cemented fixation in the short term.
- IBG demonstrates potential long-term benefits by improving radiological fixation and component positioning.
- Further research may explore the long-term survival advantages of IBG in this patient population.
Aims:
This randomized controlled trial (RCT) aimed to compare clinical and radiological outcomes of cemented acetabular component in primary total hip arthroplasty (THA) in patients aged under 60 years with and without autologous impaction bone grafting (IBG).
Methods:
A single-centre, triple-blinded RCT was conducted in patients aged 18 to 59 years undergoing primary THA without acetabular defects. Patients were randomized to receive either IBG or no IBG. Noninferiority of IBG was assessed for the primary endpoint, the Hip disability and Osteoarthritis Outcome Score (HOOS) sub-scale for activities of daily living (ADL) at one-year follow-up. Secondary outcomes included other patient-reported outcome measures (PROMs), perioperative outcomes, complications, and radiological outcomes. Radiographs assessed acetabular component and centre of rotation positioning, offset changes, and the presence of radiolucent lines in the bone-cement interface.
Results:
A total of 131 patients were randomized. No significant group differences were found for the HOOS-ADL sub-scale at one year (mean difference 1.9 points (95% CI -4.85 to 8.7); p = 0.578), meeting the criteria for noninferiority. Furthermore, there was no effect of group on the scores for other PROMs. Surgery duration (+ 7.5 minutes; p < 0.001) and blood loss (+ 100 ml; p = 0.001) were significantly higher in the IBG group. Complication and revision rates were comparable. Radiologically, the IBG group had significantly fewer radiolucent lines in the bone-cement interface than the control group at one-year follow-up (p < 0.001). Compared with preoperatively, the postoperative position of the centre of rotation was less superior and medial in the IBG group (p = 0.024).
Conclusion:
The use of autologous IBG with a cemented acetabular component in primary THA in young patients is noninferior to standard cemented fixation regarding short-term clinical outcomes. IBG improves vertical position of the centre of rotation and early radiological fixation by reducing radiolucent lines around the cup, suggesting potential benefits for long-term acetabular component survival.
