Related Experiment Video
Updated: Aug 5, 2026
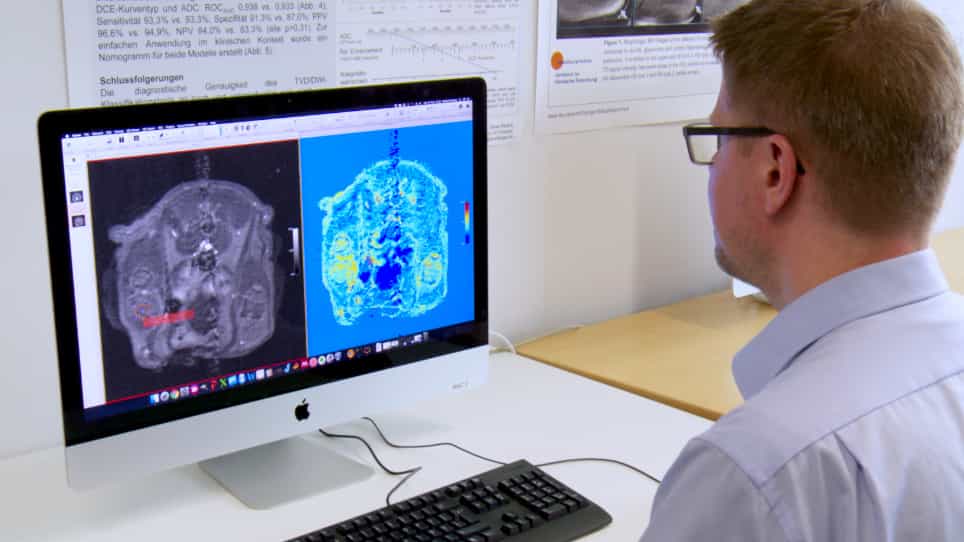

Machine Learning Algorithms for Early Detection of Bone Metastases in an Experimental Rat Model
Published on: August 16, 2020
A machine learning-based prognostic model for de novo metastatic HR-positive breast cancer: SEER cohort with external
Sihang Lin1, Wanwan Wang1, Lixia Liu1
1Department of Breast Surgery, Key Laboratory of Breast Cancer Diagnosis and Treatment Research of Guangxi Department of Education, Guangxi Medical University Cancer Hospital, Nanning, China.

Objective:
To investigate the prognostic value of postoperative radiotherapy (RT) for overall survival (OS) in patients with de novo metastatic hormone receptor (HR)-positive breast cancer, and to develop and externally validate a machine learning-based prognostic prediction model to support prognostic risk stratification in patients with or without postoperative radiotherapy.
Methods:
2,266 patients with de novo metastatic HR-positive breast cancer from the Surveillance, Epidemiology, and End Results (SEER) database (2010-2015) were retrospectively enrolled as the training cohort, and 79 patients from Guangxi Medical University Cancer Hospital (2015-2020) served as the independent external validation cohort. OS was compared between the RT and non-RT groups using Kaplan-Meier analysis and the log-rank test. Multivariate Cox regression was performed to identify independent prognostic factors. Four machine learning models-K-nearest neighbors (KNN), logistic regression (LR), random forest (RF), and extreme gradient boosting (XGBoost)-were constructed to predict 3-year OS and evaluated using the area under the receiver operating characteristic curve (AUC), average precision (AP), calibration curves, and decision curve analysis (DCA). Postoperative RT status was included as one of the input features in all models. The predicted outcome reflects 3-year prognostic risk (i.e., probability of death within 3 years) rather than the causal RT benefit.
Results:
In the training cohort, the RT group demonstrated significantly superior OS compared with the non-RT group (HR = 0.52, P < 0.001). Multivariate analysis confirmed RT as an independent protective factor for OS (HR = 0.657, P < 0.001), a finding further validated in the external validation cohort (HR = 0.171, P = 0.015). Among the four models, the LR model achieved the best performance, with an AUC of 0.721, an AP of 0.429, and a calibration slope of 0.97. DCA demonstrated favorable net clinical benefit for the LR model.
Conclusion:
Postoperative RT is an independent protective factor for OS in patients with de novo metastatic HR-positive breast cancer. The LR-based prognostic model provides reliable prognostic risk estimates and may serve as a supportive reference for clinical discussions. This model predicts observed survival risk, not the causal benefit of RT, and should not be used as a standalone tool for treatment decisions.
