Related Experiment Video
Updated: Aug 6, 2026
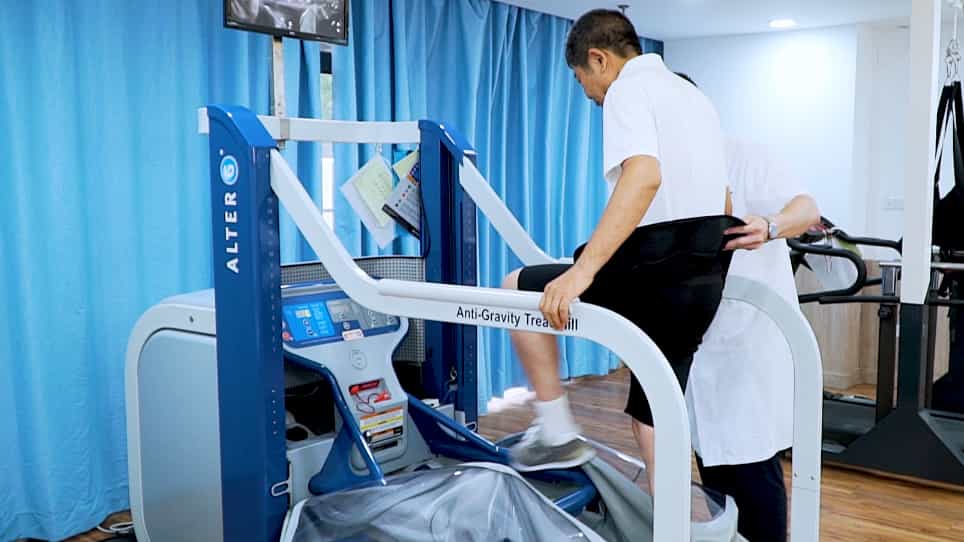

The Lower Body Positive Pressure Treadmill for Knee Osteoarthritis Rehabilitation
Published on: July 22, 2019
Comparative efficacy of early exercise interventions for recovery outcomes after total knee arthroplasty: a
Xinyue Yan1,2, PinMei Li1, Jia Li1,2
1Department of Rehabilitation, China-Japan Union Hospital of Jilin University, Changchun, China.

Background:
Early rehabilitation after total knee arthroplasty (TKA) is essential for pain relief and functional recovery. Although exercise is a core component of rehabilitation, the comparative effectiveness and optimal protocols of specific exercise modalities within the 3-day postoperative "golden period" remain uncertain. This network meta-analysis (NMA) compared the effects of different early exercise interventions (initiated ≤3 days post-TKA) on pain, joint function (WOMAC), and range of motion (ROM) and ranked their efficacy.
Methods:
Randomized controlled trials (RCTs) were systematically searched for using the PubMed, Embase, Cochrane Library, Web of Science, and Scopus databases for studies published in the past 10 years. Two reviewers independently screened the studies, extracted the data, and assessed the risk of bias using Cochrane Risk of Bias Tool (RoB2). A frequentist random-effects NMA was performed using Stata 18.0. Interventions were ranked using the surface under the cumulative ranking curve (SUCRA) values, and evidence certainty was evaluated using CINeMA.
Results:
A total of 32 RCTs (1,871 patients) evaluating nine interventions were included. In terms of pain relief, functional training and resistance training showed favorable comparative effects versus the control, with relatively high ranking probabilities (SMD: -4.23 and -1.57; SUCRA: 100 and 85.8%, respectively). For WOMAC-based functional status, functional training and intelligence-assisted training appeared to provide greater improvement than the other interventions in the current network (SMD: -1.51 and -1.35; SUCRA: 85.5 and 78.7%, respectively). Regarding ROM improvement, intelligence-assisted training and resistance training had the highest ranking probabilities and showed favorable effect estimates (SMD: 2.21 and 1.91; SUCRA: 94.7 and 88.9%, respectively). According to CINeMA, the certainty of evidence was moderate for pain and low for WOMAC and ROM.
Conclusion:
Functional training, intelligence-assisted training, and resistance training appeared to be promising early exercise strategies after TKA. Functional training showed favorable comparative effects on pain relief and functional improvement, while intelligence-assisted training demonstrated potential benefits across all three outcomes. To optimize patient recovery, clinicians should tailor the selection and combination of these interventions on the basis of the rehabilitation stage and goals.
Systematic Review Registration:
PROSPERO (CRD420251041523).