Related Experiment Video
Updated: Aug 5, 2026


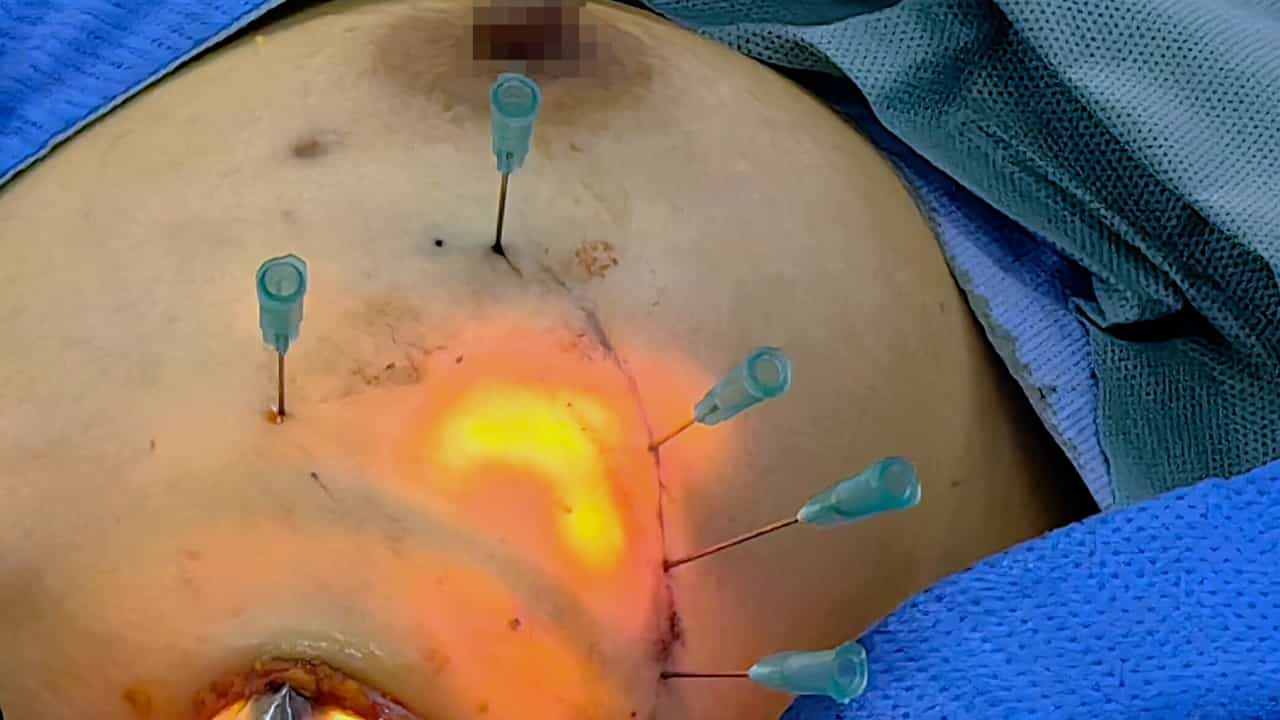
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Robotic-assisted pulmonary resection with a periareolar assistant port: learning curve and propensity-matched
Xu Hao1, Chen Simiao1, Zhang Han1
1Department of Thoracic Surgery, The Second Hospital Affiliated to Harbin Medical University, #148 Baojian Road, Harbin, 150001, China.

Objective:
Periareolar incisions improve cosmesis in video-assisted thoracoscopic surgery, but their use as an assistant port in robotic-assisted thoracoscopic surgery (RATS) has not been formally described. We characterized the learning curve of this approach and compared perioperative outcomes with conventional-portal RATS.
Methods:
We retrospectively analyzed 117 consecutive malignant RATS resections performed with a periareolar assistant port (December 2025-June 2026) and 285 conventional-portal cases (January 2024-September 2025) at a single center. Learning curve analysis used cumulative sum analysis, moving-average smoothing, and case-sequence quartile comparison. Outcomes were compared using 1:1 propensity-score matching (100 pairs) and multivariable regression.
Results:
No monotonic improvement in unadjusted operative time was detected (r = 0.099, P = 0.287), and operative time did not differ between matched groups (80.0 vs. 75.0 min, P = 0.503). The periareolar approach had less blood loss (20.0 vs. 30.0 mL, P < 0.001) but fewer lymph node stations (6.0 vs. 7.0, P < 0.001) and nodes dissected (10.0 vs. 12.5, P = 0.025), and a higher complication rate (15.0% vs. 0.0%, P < 0.001), driven mainly by prolonged air leak. Multivariable regression confirmed these findings (lymph node stations: β = -0.824, P < 0.001; complications: OR = 6.65, P < 0.001). No conversions or positive margins occurred.
Conclusions:
RATS with a periareolar assistant port was technically feasible; no monotonic improvement in unadjusted operative time was detected across the case series, and operative time was comparable to the conventional approach. However, comparative safety and oncologic adequacy remain uncertain given the higher complication rate and lower lymph-node yield observed, warranting prospective, randomized, multicenter validation.