Related Experiment Video
Updated: Aug 5, 2026


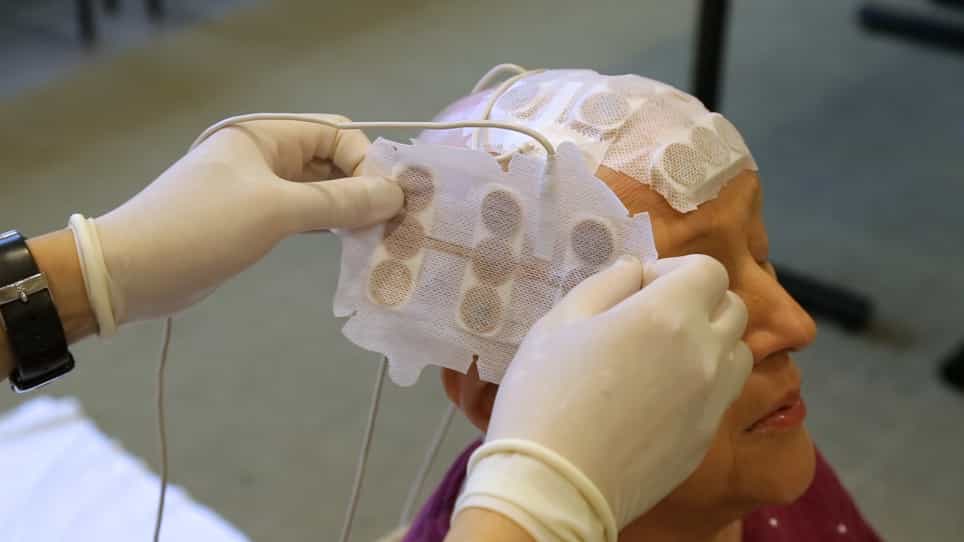
Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Therapeutic Plasma Exchange for Removal of Bevacizumab: A Case Series
Sooraj Srirangadhamu Gopu1, Rushad Patell2,3, Erik J Uhlmann3,4
1New York Medical College and Landmark Medical Center, Woonsocket, Rhode Island, USA.

Bevacizumab is a humanized monoclonal antibody against vascular endothelial growth factor A. Its long half-life and low volume of distribution allow circulating drug to persist in the body for weeks, which becomes clinically relevant when urgent or emergent surgery is needed. Because bevacizumab is largely intravascular, therapeutic plasma exchange (TPE) is attractive, though published experience is limited. We describe four adults who underwent TPE to facilitate surgery or postoperative wound healing after bevacizumab exposure: two with glioblastoma multiforme (GBM) before craniotomy, one with GBM after bowel resection with primary anastomosis, and one with metastatic rectal adenocarcinoma before craniotomy for a hemorrhagic brain mass. Patients received one to three sessions with albumin replacement, with fresh frozen plasma added in one case. No postoperative hemorrhage or delayed wound healing occurred. These cases support a practical role for TPE when residual bevacizumab exposure remains relevant and awaiting spontaneous clearance is not feasible.
Bevacizumab is a humanized monoclonal antibody against vascular endothelial growth factor A. Its long half-life and low volume of distribution allow circulating drug to persist in the body for weeks, which becomes clinically relevant when urgent or emergent surgery is needed. Because bevacizumab is largely intravascular, therapeutic plasma exchange (TPE) is attractive, though published experience is limited. We describe four adults who underwent TPE to facilitate surgery or postoperative wound healing after bevacizumab exposure: two with glioblastoma multiforme (GBM) before craniotomy, one with GBM after bowel resection with primary anastomosis, and one with metastatic rectal adenocarcinoma before craniotomy for a hemorrhagic brain mass. Patients received one to three sessions with albumin replacement, with fresh frozen plasma added in one case. No postoperative hemorrhage or delayed wound healing occurred. These cases support a practical role for TPE when residual bevacizumab exposure remains relevant and awaiting spontaneous clearance is not feasible.