Related Experiment Video
Updated: Aug 5, 2026


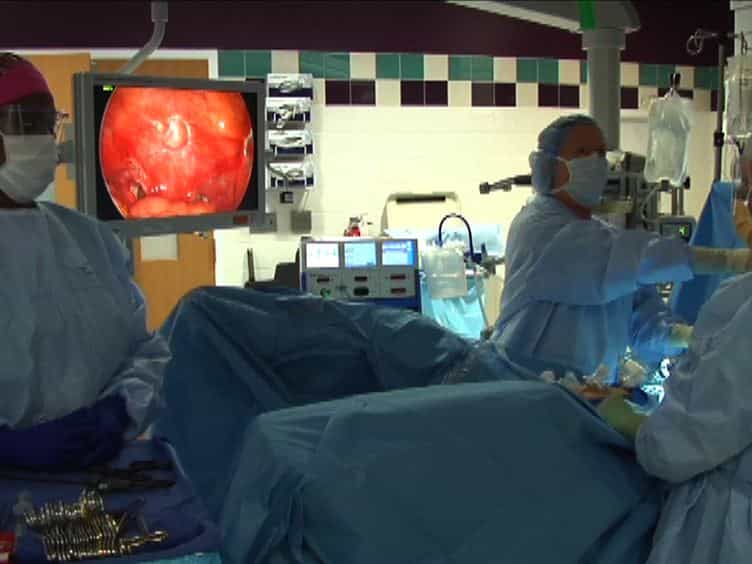
Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
When It's Not Just "That Time of the Month": Identifying Thoracic Endometriosis in the Context of Recurrent Pleural
Anjali Kamath1, Jairaj P Nair2, Tanay Sinha3
1Senior Resident, Department of Respiratory Medicine, Lokmanya Tilak Municipal Medical College and Hospital, Mumbai, Maharashtra, India, Corresponding Author.

Abstract:
Recurrent hemorrhagic pleural effusion presents as a challenge for both the clinician and the patient, with common causes being tuberculosis, malignancy, and collagen vascular diseases. Among uncommon causes of recurrent hemorrhagic effusion is catamenial hemothorax, which is a part of thoracic endometriosis syndrome (TES). Endometriosis is the extrauterine growth of endometrial glands and stroma. It is relatively common among women of reproductive age-group, with reported incidence of around 11%. Although rare, the thorax is the most common extraabdominal site for endometriosis. Here we present a rare case of recurrent hemorrhagic pleural effusion due to thoracic endometriosis in a young female with infertility. A 33-year-old female housewife presented with dyspnea on exertion modified Medical Research Council (mMRC) grade 2 and dry cough occasionally for 6 months. She had a history of tubercular cervical lymphadenopathy for which she was on treatment. Therapeutic thoracocentesis was performed thrice in 4 months. Routine microscopy showed predominantly lymphocytes, mesothelial cells, and numerous foamy histiocytes, some pigment laden. There were no malignant cells or acid-fast bacilli (AFB) detected in the fluid. Pleural fluid amylase and lipase were normal. Contrast-enhanced computed tomography (CT) thorax showed moderate right-sided pleural effusion without any evident parenchymal lesions, pleural lesions, or mediastinal lymphadenopathy. Ultrasonography (USG) abdomen and pelvis showed mild ascites which was nontappable. As we had not reached a definitive diagnosis, medical thoracoscopy was performed. It showed moderate hemorrhagic pleural fluid in the pleural cavity and a small raised erythematous glandular tissue on the parietal pleural surface from which biopsy was taken. Histopathology showed an island of endometrial stroma with a single gland. Immunohistochemistry was performed on this section, which was PAX8 and CD10 positive, confirming the diagnosis of thoracic endometriosis. Pleurodesis with talc slurry was done to prevent further refilling of the effusion. Gynecology opinion was sought, and patient was started on monthly subcutaneous injections of gonadotropin-releasing hormone (GnRH) analogue for 3 months. Chest X-ray after 3 months showed no refilling of pleural effusion. Catamenial hemothorax is the second commonest manifestation of TES, occurring in approximately 14% of cases. It affects the right side in about 80% of the cases. Diagnosis is based on high degree of suspicion and is often delayed. Video-assisted thoracic surgery (VATS) remains the gold standard for diagnosis and management of TES. Medical thoracoscopy is a viable alternative in resource-poor settings or when diagnosis is not confirmed. On histology, diagnosis is confirmed by the presence of endometriotic glands or stroma, which may also show stromal arterioles, erythrocytes, and pigmented histiocytes. In difficult-to-diagnose cases, CD10 immunohistochemical staining can help in diagnosis of endometrial tissue. There are various treatment modalities considered in the management of catamenial hemothorax, like surgical resection, medical management along with pleurodesis, combination therapy, or in some cases, simple observation. Currently, VATS with GnRH analogue therapy is considered the gold standard of management.
Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Pleural Disorders: Types and Brief Description
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...