Related Experiment Video
Updated: Aug 9, 2026

Simulator Training for Endovascular Neurosurgery
Published on: May 6, 2020
A Prospective Randomized Controlled Simulation Study to Test a Proof-of-Concept Real-Time Periprocedural Decision
Anthony Dinkel1, Justin Talluto, Vikranth Chinthareddy
1Department of Anesthesiology, Massachusetts Eye and Ear Infirmary, Harvard Medical School, Boston, MA.

Objectives:
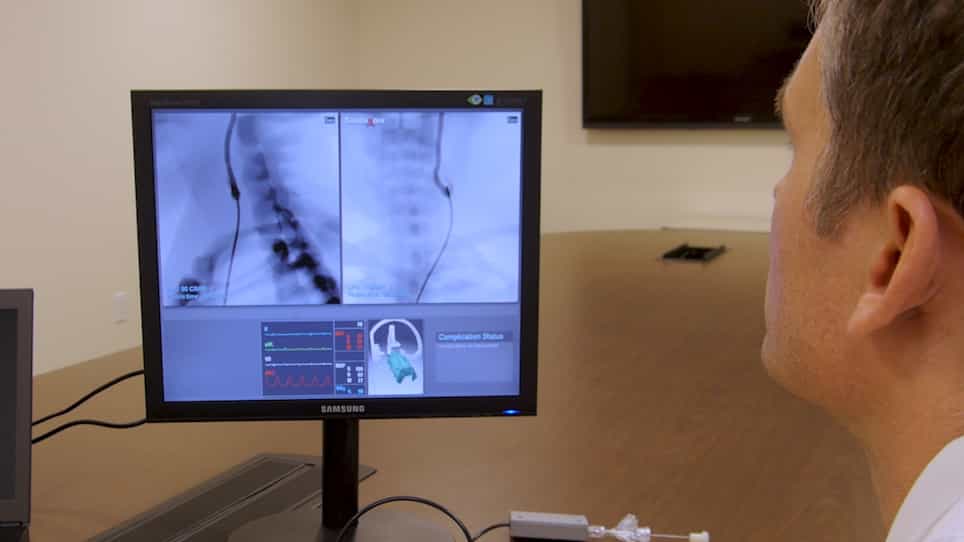
The recent pilot simulation study by Greenberg and colleagues introduced a proof-of-concept audio-visual support system for anesthesiology professional management of perioperative patient deterioration. The results demonstrated that real-time decision support for providers may enhance diagnostic accuracy/efficiency. In collaboration with Greenberg and colleagues, the authors from Massachusetts General Brigham (MGB) similarly developed a realistic operating room simulation environment at Massachusetts General Hospital (MGH) Learning Center. Here, the ability of anesthesiology trainees to accurately diagnose and treat using audio-visual cues was measured.
Methods:
This study is a prospective, randomized controlled pilot trial adapted from a recent study further investigating the impact of audio-visual decision support on anesthesiology resident and student nurse anesthetist diagnostic accuracy and efficiency. This study took place entirely at Massachusetts General Hospital Center for Simulation and Innovation. Twenty-one anesthesiology trainees were randomized into 2 groups: (1) standard of care (control) versus (2) audio-visual cue group (experimental). The experimental group received audio-visual cues such as a choice of possible diagnoses from an experienced anesthesiologist and subsequent recommended interventions from the Stanford emergency manual and based on changes in the simulated patient's vitals. Each participant underwent 3 experimental simulations where patient deterioration occurs. These included: anaphylaxis, amniotic fluid embolism (AFE), and pulseless electrical activity (PEA) arrest during a pediatric dental case. Key time points and accuracy of diagnoses and treatment steps were recorded.
Results:
The simulation scenario recordings for 10 anesthesiology residents and 11 student nurse anesthetists of various training years were investigated. For the anaphylaxis scenario, there was a statistically significant increase in the number of participants who correctly executed intervention 1 in the intervention group compared with the control group (P=0.0015). For the AFE scenario, there was a statistically significant increase in the median time to intervention 1 for SRNAs in the intervention group compared with the control group (P=0.01). However, there was a statistically significant decrease in the median time to intervention 1 for residents in the intervention group compared with the control group (P=0.01). For the pediatric dental scenario, there was a statistically significant increase in the number of participants in the intervention group versus the control group who made the correct diagnosis 2 (P=0.005). In addition, there was a statistically significant increase in the number of participants in the intervention group versus the control group who made the correct diagnosis 3 (P=0.023).
Conclusions:
The results indicate that real-time audio and visual cues in a simulated operative environment may improve time to diagnosis and treatment. This effect has now been investigated across the training spectrum from resident trainees to attendings. On the basis of observations from these simulations, this mode of simulation can be an effective educational tool for simulation-based learning exercises. In education or real-time practice, additional dedicated research and development of decision support technology could be beneficial in improving safety during periprocedural care by guiding best training practices.