Related Experiment Video
Updated: Aug 5, 2026

Surgical Retrieval, Isolation and In vitro Expansion of Human Anterior Cruciate Ligament-derived Cells for Tissue Engineering Applications
Published on: April 30, 2014
Length Changes of the Lateral Knee: Fibular Collateral Ligament, Anterolateral Ligament, and Iliotibial Band Fibers
Edouard J Augustin1,2, Zachary R Oppenheim1, Jose Vega1
1Rush University Medical Center, Chicago, Illinois, USA.

Background:
The lateral knee is stabilized by the fibular collateral ligament (FCL), anterolateral ligament (ALL), and iliotibial band (ITB) fibers. Understanding their flexion-dependent behavior is critical for guiding graft fixation during reconstruction.
Hypothesis/Purpose:
The hypothesis was that the FCL and ALL would shorten with flexion, while ITB fibers would show more minor, transient changes. The purpose was to characterize native length changes of these structures in cadaveric knees.
Study Design:
Descriptive laboratory study.
Methods:
Ten fresh-frozen knees were dissected with preservation of lateral soft tissue attachments. Bony landmarks were marked for the attachment sites: FCL (n = 10), ALL (n = 7), and ITB (n = 10 distal Kaplan fibers, n = 9 proximal). A 3-dimensional digitizer recorded coordinates at 0°, 15°, 30°, 45°, 60°, and 90° of flexion. Attachment distances were calculated, and paired t tests or Wilcoxon tests (based on Shapiro-Wilk normality) compared 0° with each flexion angle.
Results:
Distances between the FCL and ALL attachment sites progressively decreased with flexion, with mean reductions of -7.59 and -6.44 mm, respectively, from 0° to 90° (both P≤ .05). Distances from the Gerdy tubercle to the distal and proximal Kaplan attachments of the ITB increased significantly by 2 to 6 mm between 15° and 60° before returning toward baseline at 90°: distal Kaplan, -0.78 mm (P = .853); proximal Kaplan, -3.99 mm (P = .506).
Conclusion:
FCL and ALL attachment distances decreased throughout flexion. In contrast, the distances from the Gerdy tubercle to the proximal and distal Kaplan attachments demonstrated midflexion lengthening with a return toward baseline at deeper flexion angles, reflecting relative isometry of these ITB segments. This study is the first to describe the simultaneous length change behavior of all 3 structures, providing integrated anatomic data that may inform graft tensioning and fixation strategies for ALL, FCL, and lateral extra-articular tenodesis reconstruction of the lateral knee.
Clinical Relevance:
The relative isometry observed in ITB attachment distances suggests that lateral extra-articular tenodesis graft fixation may be less sensitive to knee flexion angle. In contrast, the flexion-dependent decreases in FCL and ALL attachment distances suggest that fixation at knee flexion angles closer to extension may be favorable for avoiding overconstraint in reconstruction of these ligaments. These findings are anatomic and descriptive rather than prescriptive. Further loaded biomechanical studies are needed to determine optimal graft tensioning protocols.

Related Concept Videos
 01:23
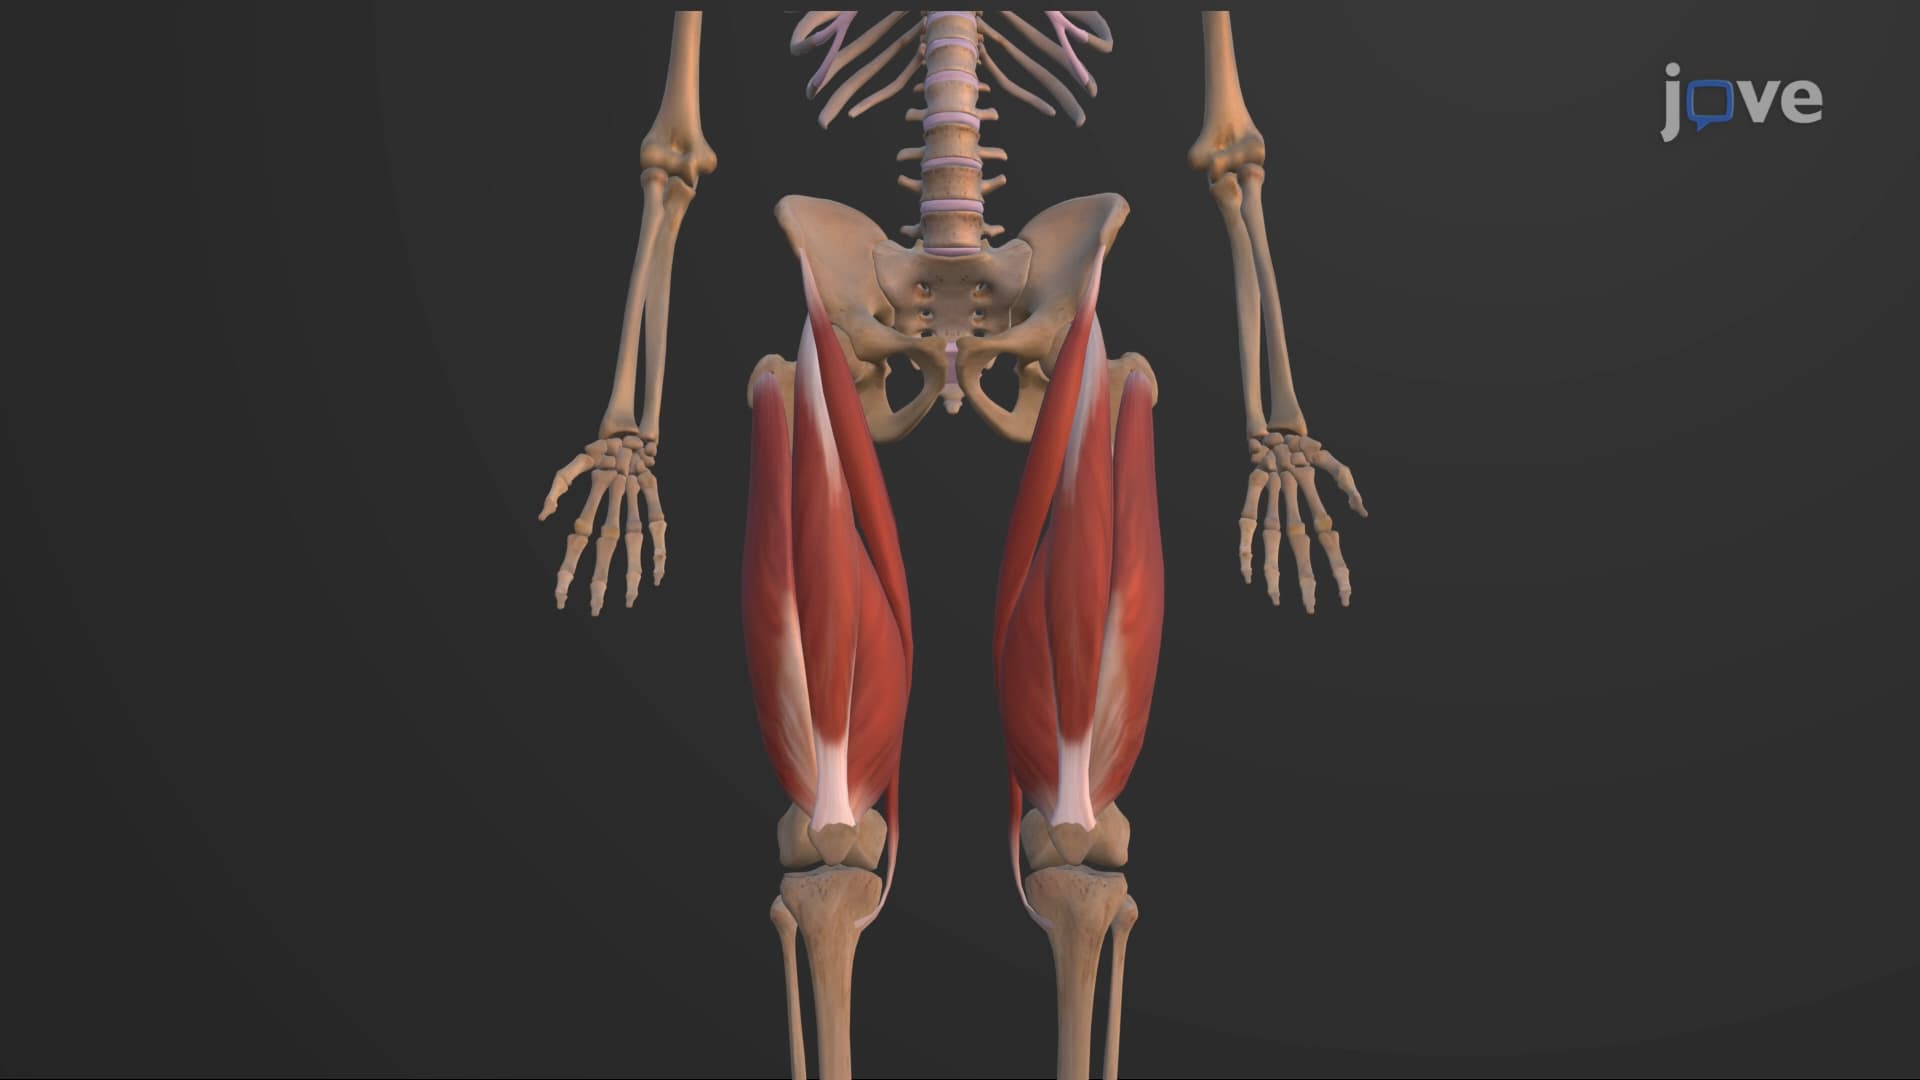
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris group...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:10
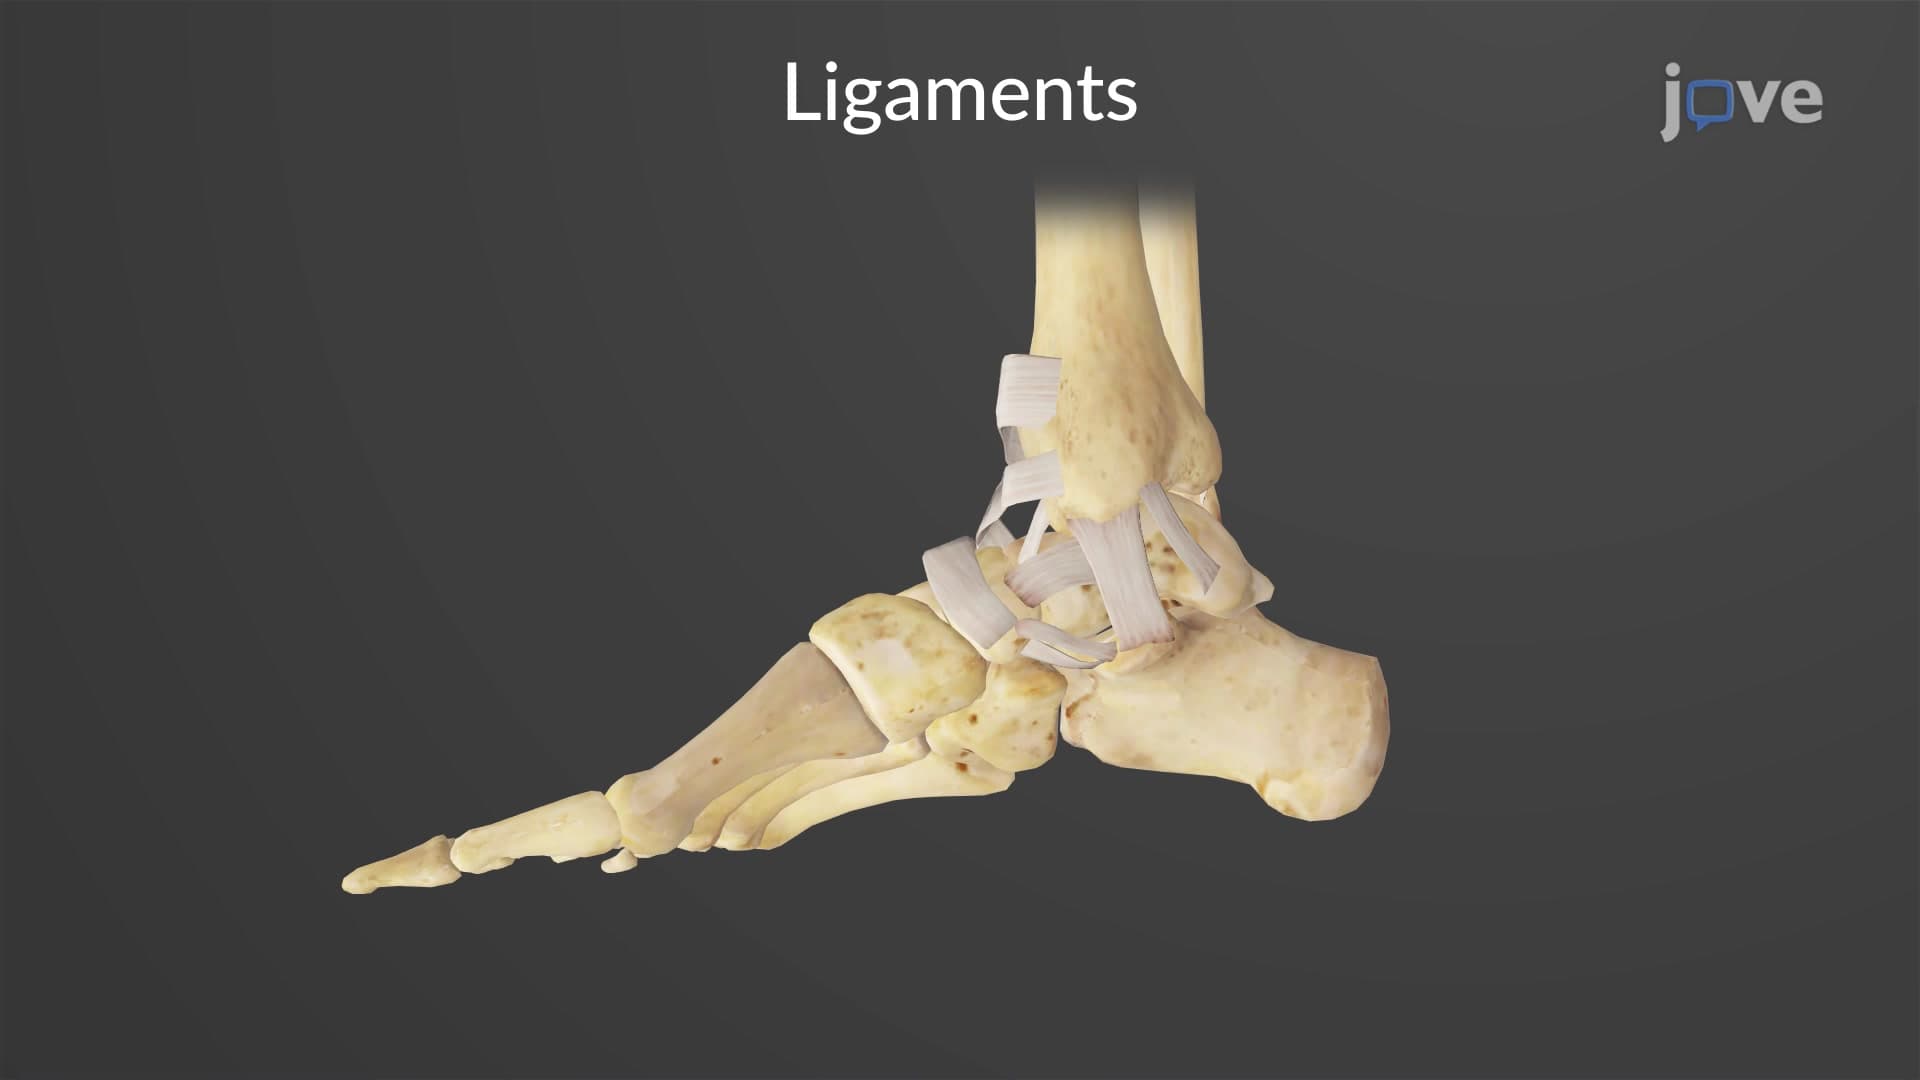
Ankle Joint
 01:28
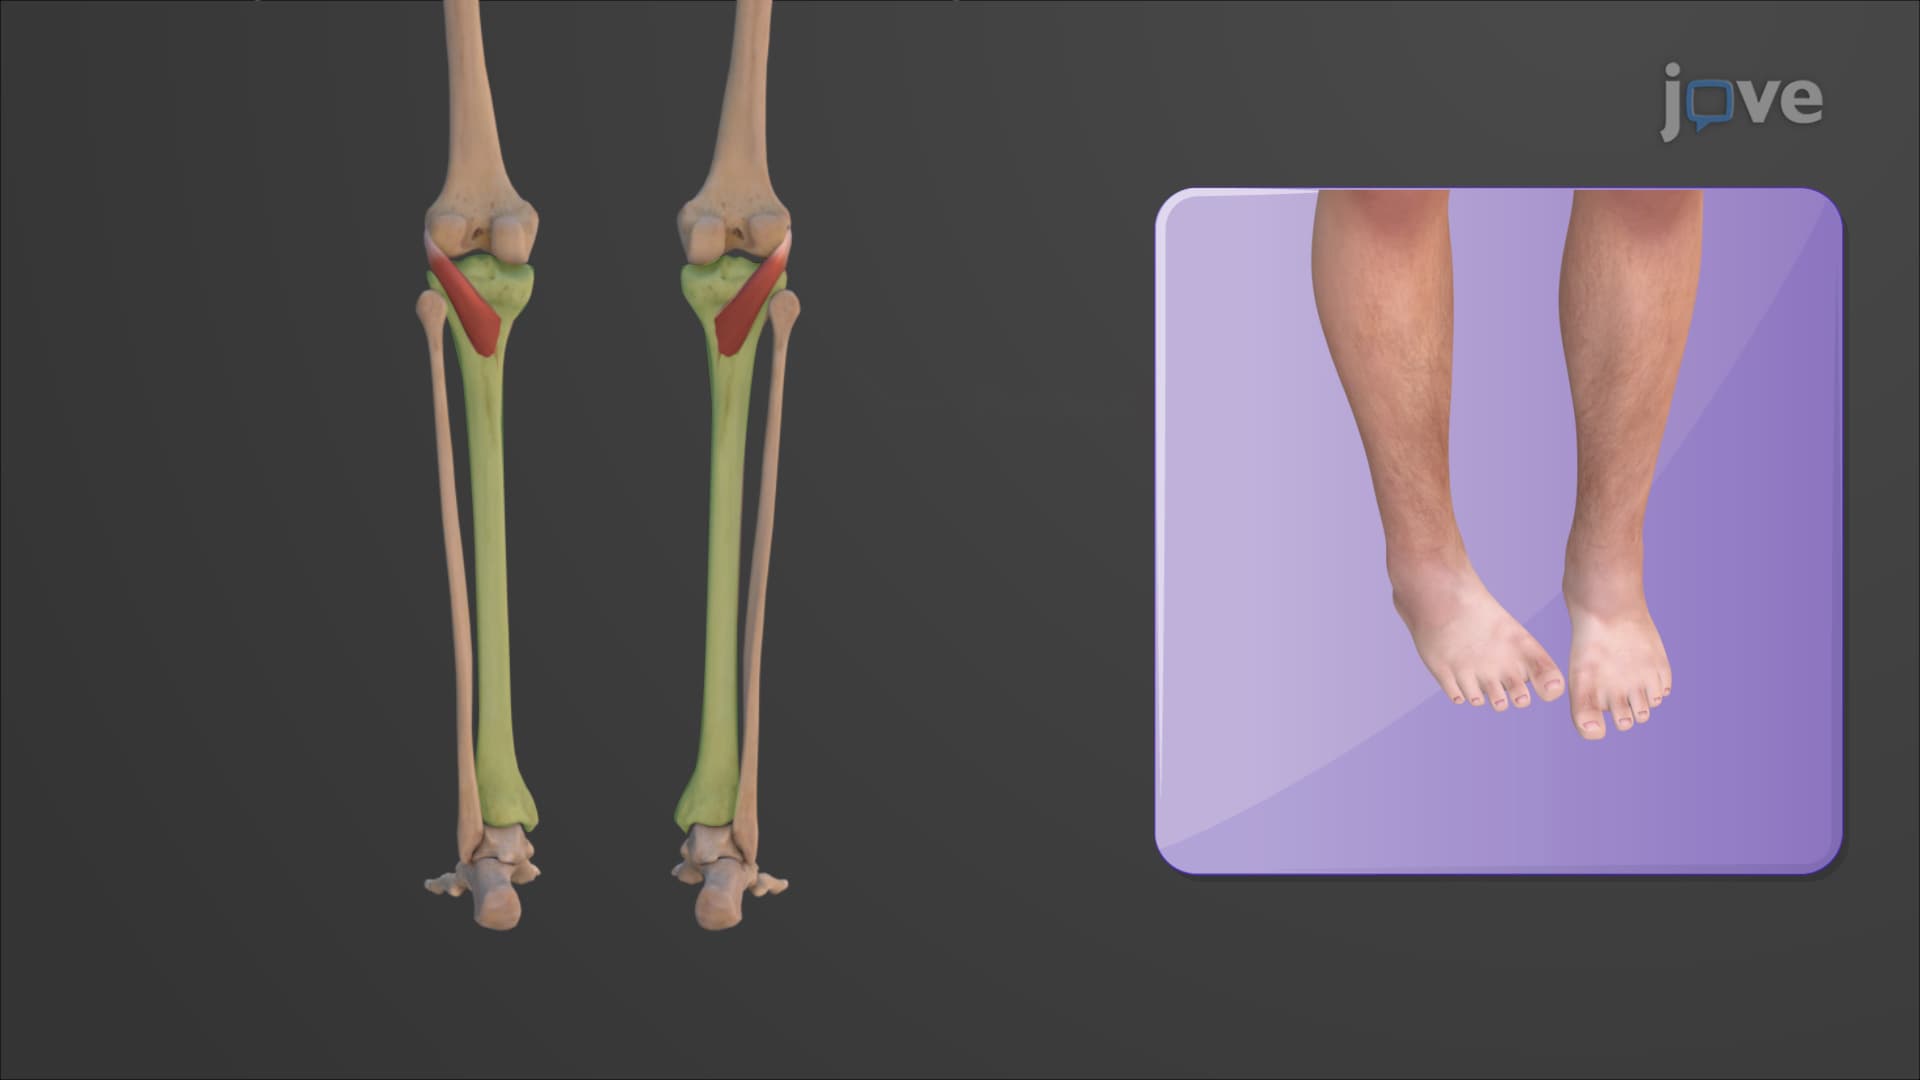
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
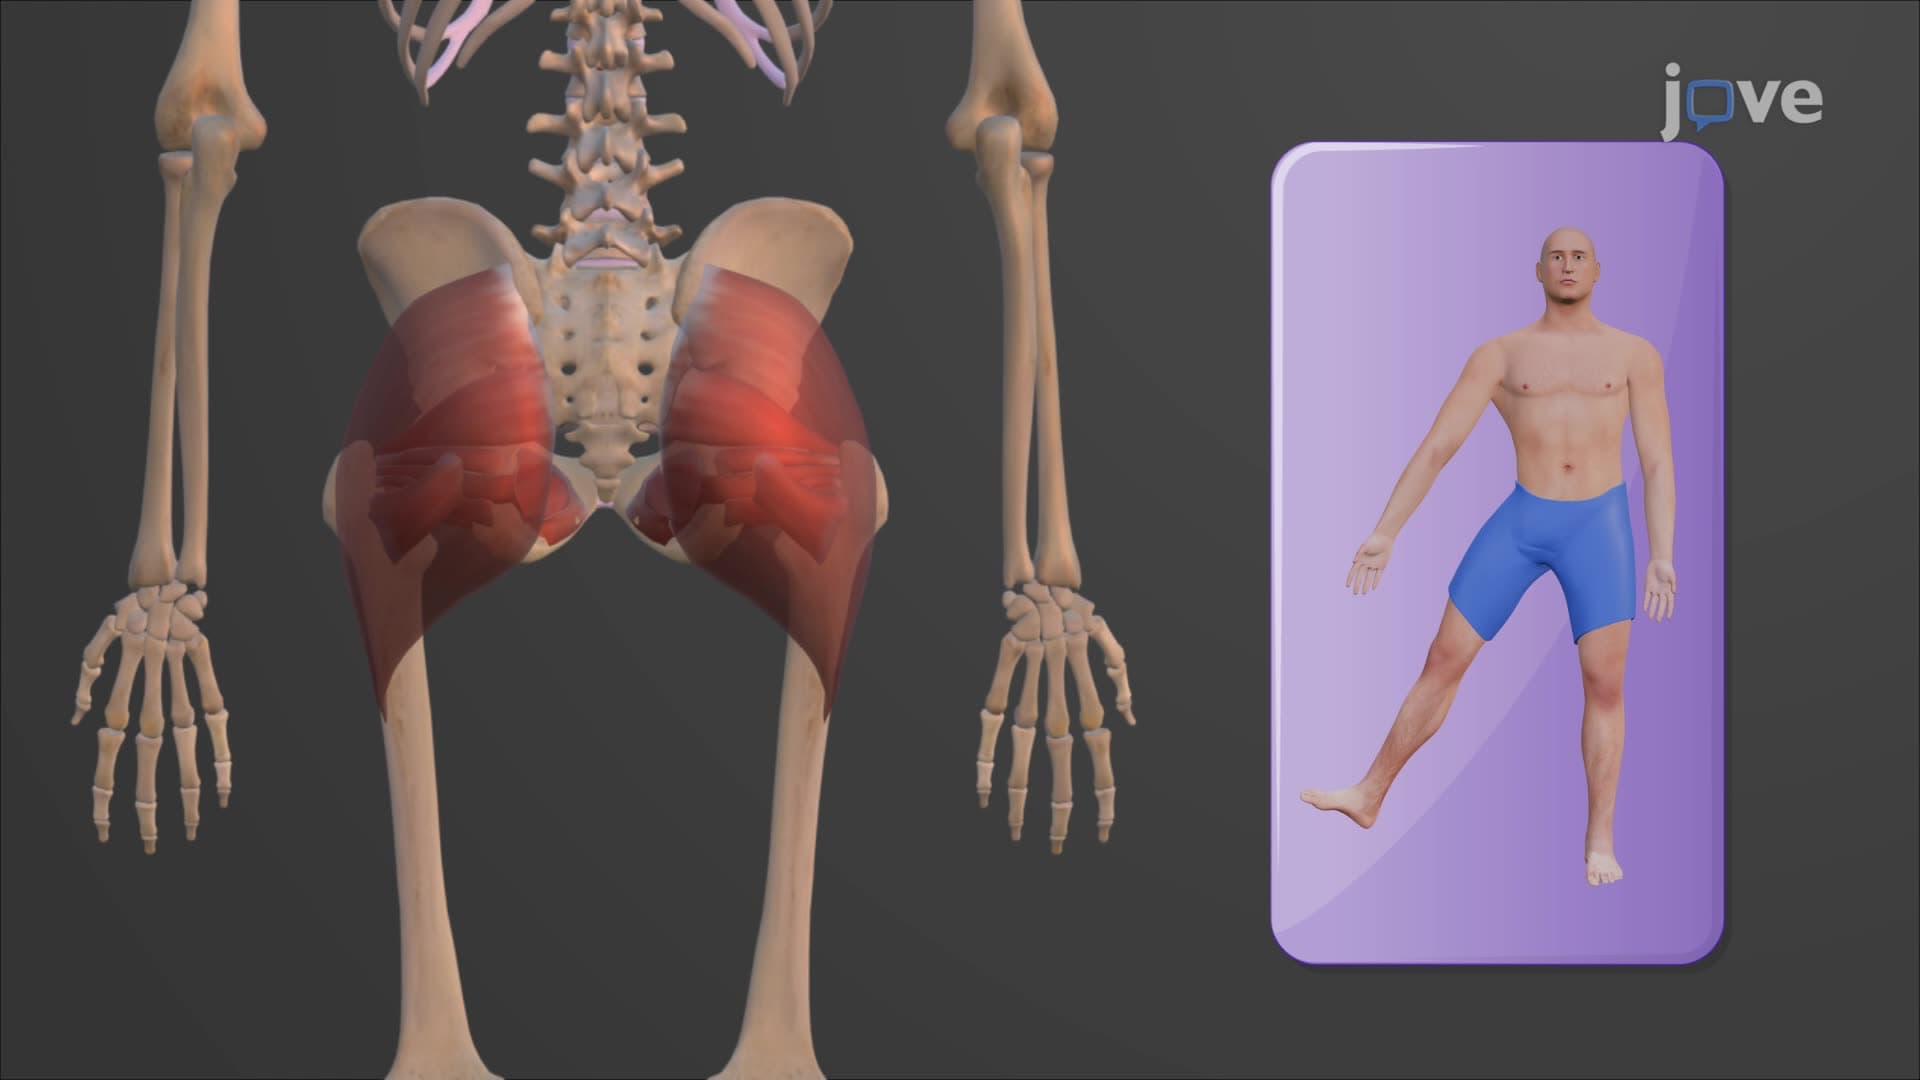 01:20
Muscles that Move the Thigh
Three other significant muscles are the gluteus maximus, gluteus medius, and gluteus minimus. The gluteus maximus originates from the posterior surface of the ilium, sacrum, and coccyx, and the thoracolumbar fascia...