Related Experiment Video
Updated: Aug 5, 2026
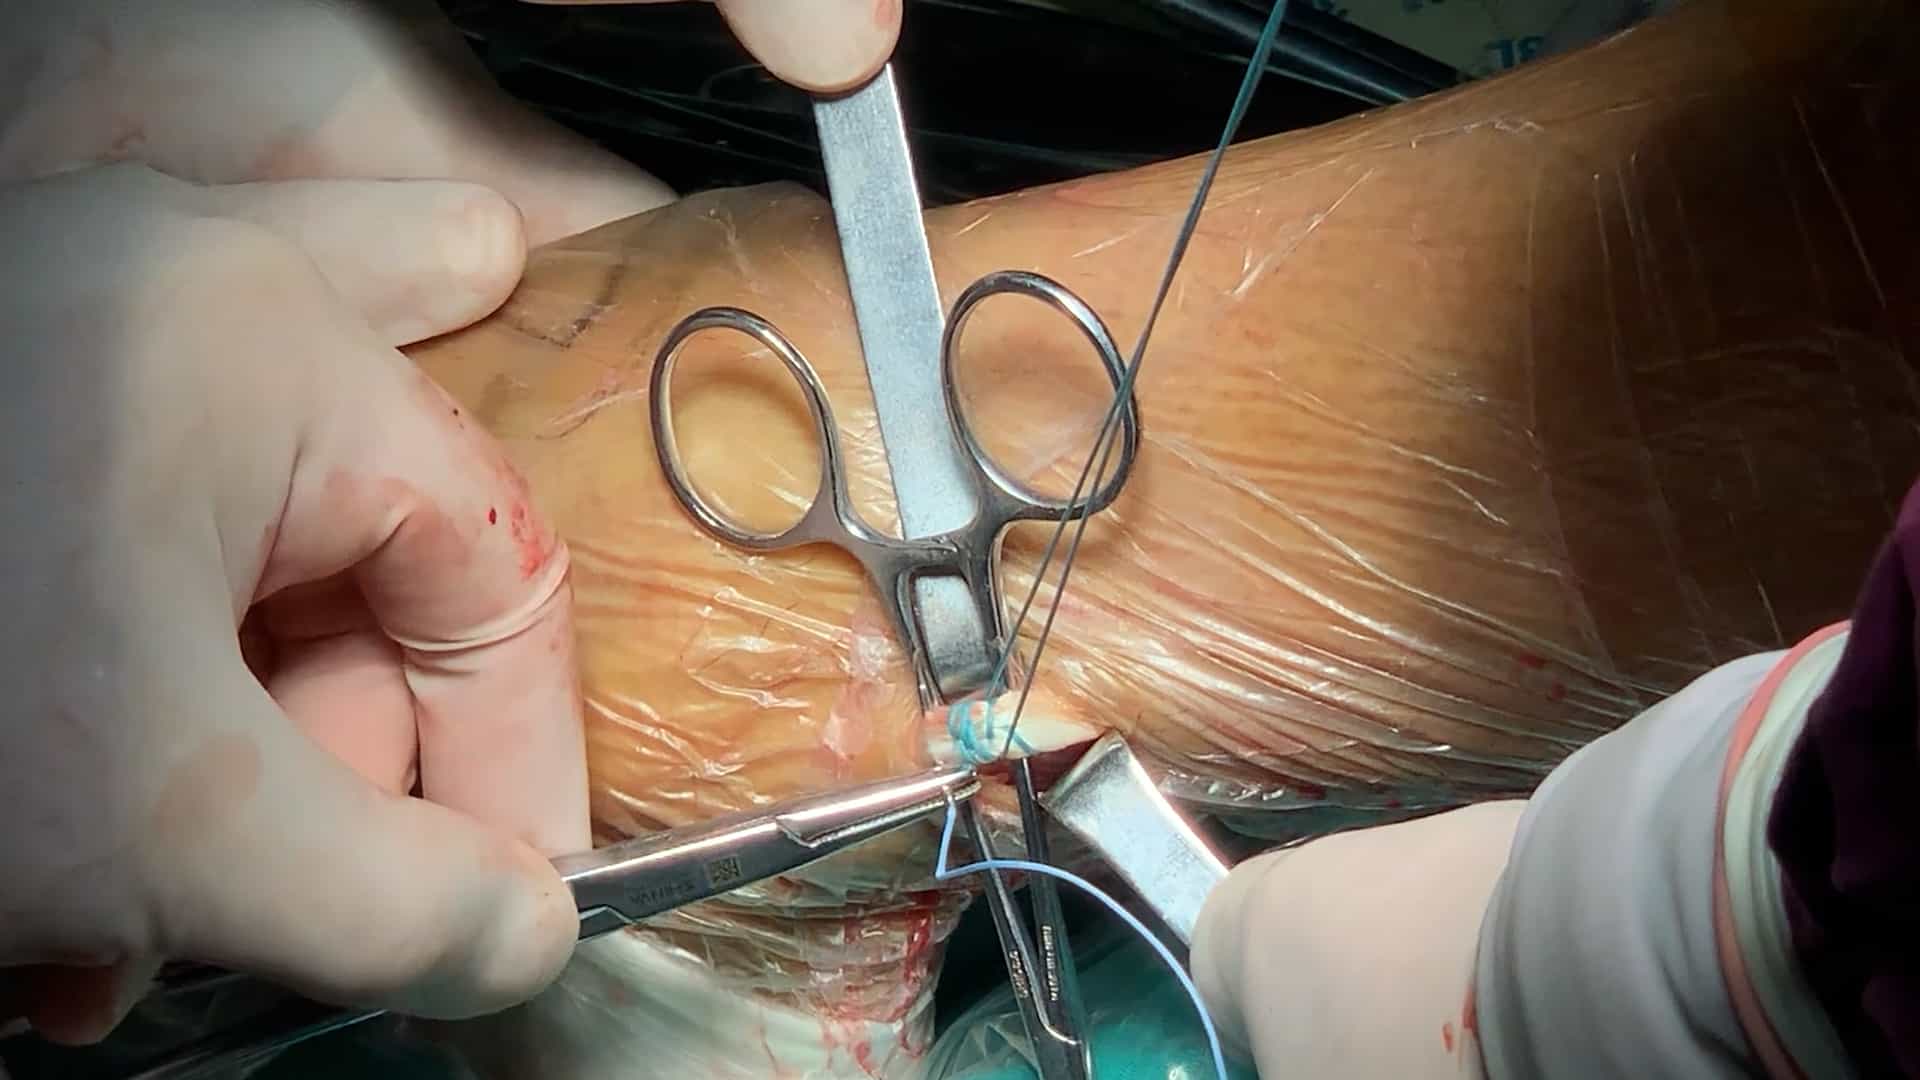

Harvesting of Peroneus Longus Tendon Autograft
Published on: September 2, 2025
Quadriceps Tendon Autografts Are Associated With Increased Short-term Reoperation Rates for Extension Deficit or Pain
Carolina Kekki1,2, Riccardo Cristiani1,2, Anders Stålman1,2
1Department of Molecular Medicine and Surgery, Stockholm Sports Trauma Research Center, Karolinska Institutet, Stockholm, Sweden.

Background:
Anterior cruciate ligament reconstruction (ACLR) rates are rising, and quadriceps tendon (QT) autografts have gained popularity in recent years. Although QT autografts show objective and subjective outcomes comparable to hamstring tendon (HT) and bone-patellar tendon-bone (BPTB) autografts, nonrevision reoperations across graft types and their impact on patient-reported outcome measure (PROM) scores remain poorly studied.
Purpose:
To compare nonrevision reoperation rates and PROM scores between primary ACLR using HT, BPTB, and QT autografts at 2 years' follow-up.
Study Design:
Cohort study; Level of evidence, 3.
Methods:
In this retrospective cohort study, 5653 primary ACLR procedures (2015-2022) were categorized by autograft type. Reoperations for extension deficit or pain, meniscal injuries, or cartilage injuries within 2 years were identified through medical records. Revision ACLR and graft failure were not included. Patient-reported outcomes were assessed preoperatively and at 2 years postoperatively using the Knee Injury and Osteoarthritis Outcome Score (KOOS). The minimal important change, patient acceptable symptom state, and treatment failure were evaluated using the KOOS4. Subgroup analysis examined associations between graft diameter, sex, and reoperations for extension deficit or pain.
Results:
The QT group had a higher overall reoperation rate (19.2%) than the HT (8.9%) and BPTB (6.9%) groups (P < .001), driven by extension deficit or pain (11.9% vs 5.5% and 4.7%, respectively; P < .001). QT grafts remained independently associated with reoperations for extension deficit or pain after adjusting for confounders (odds ratio [OR], 1.96 [95% confidence interval (CI), 1.44-2.67]; P < .001). The QT group demonstrated lower odds of achieving the minimal important change than the HT (OR, 0.56 [95% CI, 0.41-0.77]; P < .001) and BPTB (OR, 0.48 [95% CI, 0.32-0.72]; P < .001) groups. The QT and BPTB groups showed higher odds of experiencing treatment failure (OR, 1.98 [95% CI, 1.21-3.23]; P = .01 and OR, 2.00 [95% CI, 1.10-3.63]; P = .02) and lower odds of achieving the patient acceptable symptom state (OR, 0.65 [95% CI, 0.49-0.85]; P = .002 and OR, 0.57 [95% CI, 0.41-0.79]; P < .001) than the HT group. On sex-stratified analysis, female patients demonstrated higher reoperation rates for extension deficit or pain than male patients (7.3% vs 5.5%, respectively; P = .01), and female patients receiving larger grafts (9.5-12.0 mm) demonstrated 72% higher odds of having this outcome (OR, 1.72 [95% CI, 1.14-2.56]; P = .01).
Conclusion:
QT autografts were associated with significantly higher reoperation rates for extension deficit or pain and inferior PROM scores compared with HT autografts at 2 years after primary ACLR.