Related Experiment Video
Updated: Aug 5, 2026
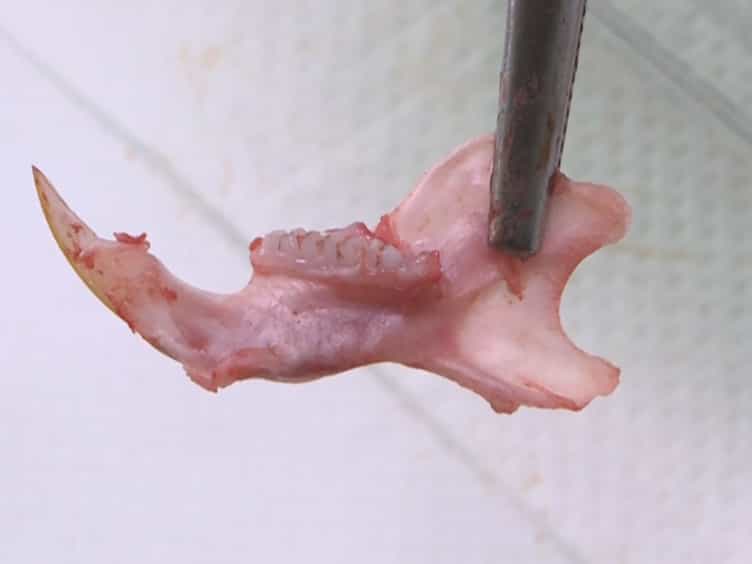

Micro-dissection of Enamel Organ from Mandibular Incisor of Rats Exposed to Environmental Toxicants
Published on: March 29, 2018
Perinatal and Neonatal Factors Associated With Developmental Defects of Enamel in Primary Dentition of Children Born
1Yale School of Medicine, New Haven, Connecticut, USA.

Insights
Developmental defects of enamel (DDE) are common in premature infants, with incidence linked to gestational age. Maternal diabetes and respiratory distress syndrome (RDS) are risk factors, while preeclampsia may be protective.
Area of Science:
- Neonatal health
- Pediatric dentistry
- Developmental biology
Background:
- Developmental defects of enamel (DDE) in premature infants are understudied.
- Understanding perinatal and neonatal risk factors for DDE is crucial for early intervention.
Purpose of the Study:
- To investigate perinatal and neonatal factors associated with DDE in the primary dentition of premature infants.
- To identify potential risk and protective factors for DDE in this vulnerable population.
Main Methods:
- Prospective observational study of infants born at or before 32 weeks gestational age (GA).
- Exclusion of infants with specific congenital anomalies or infections.
- DDE assessment at 3 years corrected age using the modified DDE index.
Main Results:
- A significant inverse association was found between GA and DDE (OR 0.86, p=0.04).
- Maternal diabetes (OR 3.4, p=0.04), respiratory distress syndrome (RDS, OR 2.44, p=0.03), and days on furosemide (OR 1.02, p=0.04) were associated with increased DDE risk.
- Preeclampsia showed a protective association with DDE (OR 0.32, p=0.006).
Conclusions:
- DDE is prevalent in premature infants, with higher incidence correlating with lower GA.
- Maternal diabetes, RDS, and furosemide exposure are potential risk factors for DDE.
- Preeclampsia may offer a protective effect against DDE in premature infants.
Background:
Perinatal and neonatal factors associated with developmental defects of enamel (DDE) among children born prematurely have not been well studied.
Aim:
To evaluate perinatal and neonatal factors associated with DDE in primary dentition among children born prematurely.
Design:
A prospective observational study was performed including ≤ 32 weeks gestational age (GA) infants within 12 h after birth. Infants with TORCH infections, chromosomal disorders, craniofacial anomalies, inherited anomalies of teeth, organic acidemia, or who died were excluded. At 3 years of corrected age, DDE was evaluated using the modified DDE index.
Results:
One hundred and eighty-three infants were studied of which 77 developed DDE. GA was inversely associated with DDE (OR 0.86, 95% CI: 0.75-0.99, p = 0.04). On multivariate logistic regression, maternal diabetes (OR 3.4, 95% CI: 1.05-11.2, p = 0.04), preeclampsia (OR 0.32, 95% CI: 0.15-0.73, p = 0.006), respiratory distress syndrome (RDS, OR 2.44, 95% CI: 1.05-5.7, p = 0.03), and days on furosemide (OR 1.02, 95% CI: 1.001-1.04, p = 0.04) were associated with DDE.
Conclusion:
DDE in primary dentition is common among children born prematurely with incidence directly related to the degree of prematurity. Maternal diabetes, RDS, and days on furosemide may be risk factors, whereas preeclampsia may be protective for DDE.

Related Concept Videos
 01:28
Development of the Oral Microbiota
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin and...
 01:07
Teratogenicity
 01:30
Neurulation
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or grinding food.
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...