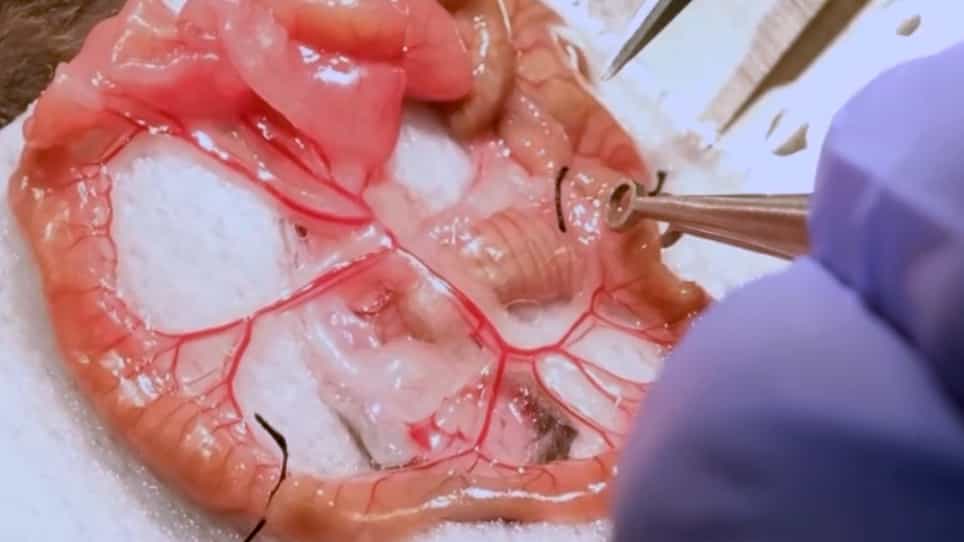
Related Experiment Video
Updated: Aug 5, 2026


Performing Colonoscopic-Guided Pinch Biopsies in Mice and Evaluating Subsequent Tissue Changes
Published on: February 5, 2021
Evaluation of intestinal leakage pressure following unsutured intestinal biopsies performed with an automatic
Esther Deglume1, Roberta Aloisi1,2, Guilhem Delsol1
1IVC Evidencia, CHV des Cordeliers, Meaux, France.

Objective:
To evaluate whether full-thickness intestinal biopsies performed with an automated needle-core device, without closure of the biopsy site, maintain adequate intestinal integrity in dogs and cats.
Materials And Methods:
This experimental study consisted of ex vivo testing on small intestinal segments from fresh canine and feline cadavers, and in vivo testing in dogs and cats undergoing enterectomy for unrelated indications. Full-thickness biopsies were performed using a 16-gauge automated needle-core device, with biopsy sites left unsutured. Intraluminal pressure was progressively increased using methylene blue-stained saline, and the initial leakage pressure (ILP) was recorded at first visible evidence of leakage. Cadaveric and in vivo ILP were compared to each other and to the reported maximal physiological intraluminal pressure of 25 mmHg.
Results:
Thirty-nine cadaveric intestinal segments from seven animals were evaluated. The mean cadaveric ILP was 20.7 mmHg (95% CI [5.9-35.5 mmHg]), with leakage observed below 25 mmHg in 33 of them. In vivo ILP was measured in 12 patients (8 dogs, 4 cats), yielding 23 measurements. The mean in vivo ILP was 85.66 mmHg (95% CI [55.53, 115.78]), significantly exceeding the reference value of 25 mmHg, and all measurements remained above 26 mmHg.
Conclusion:
Cadaveric leakage pressures were markedly lower than in vivo measurements, suggesting that cadaveric models may be poorly suited for evaluating intestinal pressure. In contrast, unsutured needle-core biopsy sites in live dogs and cats tolerated pressures above reported maximal physiological levels, immediately after biopsy. These findings suggest that the immediate risk of leakage at small (1.3-mm) unsutured biopsy sites is low; however, because healing and longer-term integrity were not evaluated, the necessity of routine closure cannot be established from these data. Further studies are needed to evaluate long-term safety and applicability in diseased intestines.