Related Experiment Video
Updated: Aug 5, 2026
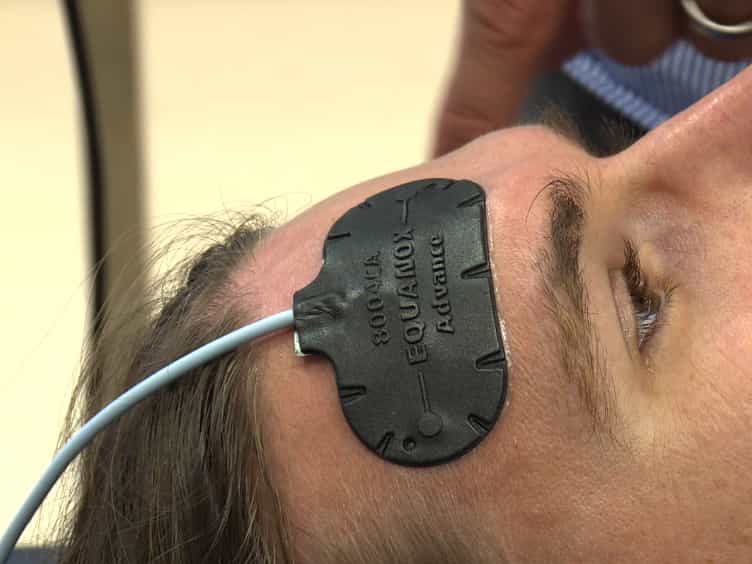

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
Apnea-hypopnea index estimation using overnight chest-wall accelerometry
Fons Schipper1,2, Pedro Fonseca1,2, Angela Grassi1
1Philips Sleep and Respiratory Care, Eindhoven, Netherlands.

Rationale And Study Objectives:
To develop a method for apnea-hypopnea index (AHI) estimation using a chest-worn accelerometer, as an approach to obstructive sleep apnea diagnosis and long-term monitoring of treatment, for example through positional therapy.
Methods:
We developed a method for AHI estimation by combining a cardiorespiratory sleep staging algorithm with an adapted neural network for detecting respiratory events. Originally based on electrocardiography and respiratory impedance plethysmography, the network was retrained using chest-wall accelerometry-based instantaneous heart rate and respiratory effort. Training and validation utilized accelerometer data from 413 participants across two centers, recorded during diagnostic overnight polysomnography (PSG), in absence of any therapy. The dataset was split equally: half was used to train the neural network, and the remaining half to evaluate its performance. This evaluation compared the accelerometry-derived overnight AHI against the reference from PSG, both overall and separately for supine and non-supine sleeping positions.
Results:
Sleep staging reached substantial agreement with polysomnography, achieving a Cohen's kappa coefficient of agreement of 0.67 for four-class sleep staging (Wake/REM/N1-N2/N3). AHI was estimated with highly reliable, showing an intraclass correlation coefficient of 0.90 (95% CI: 0.86-0.92) when compared to polysomnography-derived values. Performances were consistent in both supine and non-supine sleeping positions. Positive likelihood ratios were high (7.1, 16.0, and 165.7 for the mild, moderate, and severe OSA severity classes, using near-boundary double labeling). Negative likelihood ratios were low (0.095, 0.153, and 0.069 for the same cases).
Conclusion:
AHI can be reliably estimated using chest-wall accelerometry. This approach may be used in diagnostic tests for OSA but also to assess residual AHI during positional therapy.

Related Concept Videos
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:26
Respiratory Volumes and Capacities I
 01:23
Acute Respiratory Failure-IV