Related Experiment Video
Updated: Aug 7, 2026
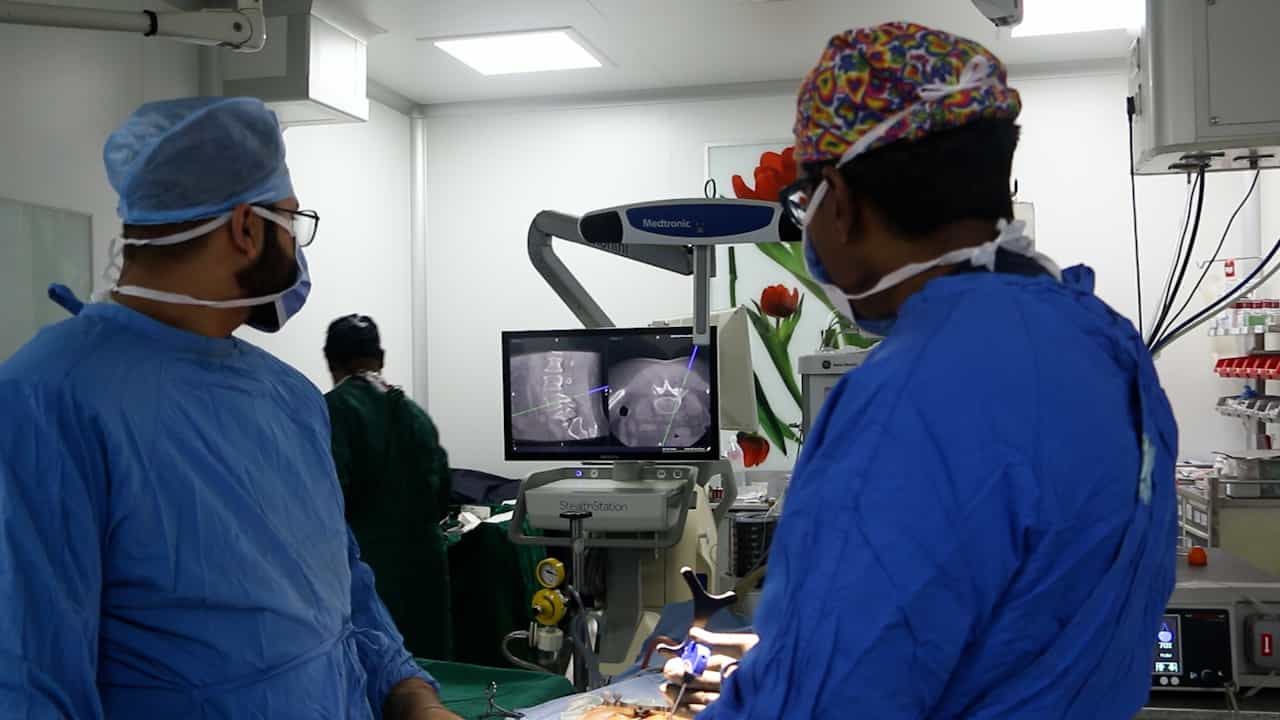

Optimizing Minimally Invasive Spine Surgery: A Fully 3D CT O-Arm Navigated Workflow in MIS TLIF
Published on: October 17, 2025
Patient-reported Outcomes in Primary versus Revision Cervical and Lumbar Spine Surgery: An Analysis of the Michigan
Daniel K Park1, Philip Zakko, Jad Khalil
1From the Midwest Orthopedics at RUSH, Chicago, IL (Dr. Park); the Department of Orthopedics, Corewell Health, Royal Oak, MI (Dr. Zakko); the Michigan Orthopedic Surgeons, Southfield, MI (Dr. Khalil); the Department of Orthopaedic Surgery, University of Michigan, Ann Arbor, MI (Dr. Aleem); the Department of Neurosurgery, Henry Ford Hospital, Detroit, MI (Dr. Tong and Dr. Chang); and the Department of Orthopedics, Henry Ford Hospital, Detroit, MI (Dr. Kahn and Dr. Taliaferro).

Objectives:
To see whether there are differences between primary and revision surgeries while stratifying results by cervical and lumbar regions.
Methods:
Michigan Spine Surgery Improvement Collaborative is a multi-institutional quality-improvement collaborative across Michigan. The analytic sample included patients who underwent spine surgery between February 24, 2014, and January 31, 2025. Descriptive statistics were used to compare demographic characteristics and patient-reported outcomes between primary and revision procedures.
Results:
A total of 49,577 patients undergoing primary lumbar surgery and 3745 undergoing revision were identified. For cervical procedures, 20,473 primary and 3281 revision cases were included. Patients undergoing revision surgery were slightly older across both spinal regions. In unadjusted analyses, revision lumbar patients consistently demonstrated worse outcomes than those undergoing primary surgery. Return to work at 1 year was lower among revision patients, and they also had markedly higher odds of opioid use and emergency department visits. In the cervical cohort, similar differences were observed. In addition, cervical revision patients demonstrated higher odds of readmission and return to the operating room. After adjusting for patient demographics, comorbidities, and surgical factors, revision surgery remained an independent predictor of worse outcomes in both spinal regions.
Conclusions:
Revision spine surgery is associated with worse outcomes compared with primary procedures even after adjusting for baseline risk factors. The results are consistent across cervical and lumbar revisions about pain scores, physical function, opioid use, and patient satisfaction. Opioid usage continued to be higher, while return to work was delayed for lumbar revision patients.
Study Design:
Retrospective database.