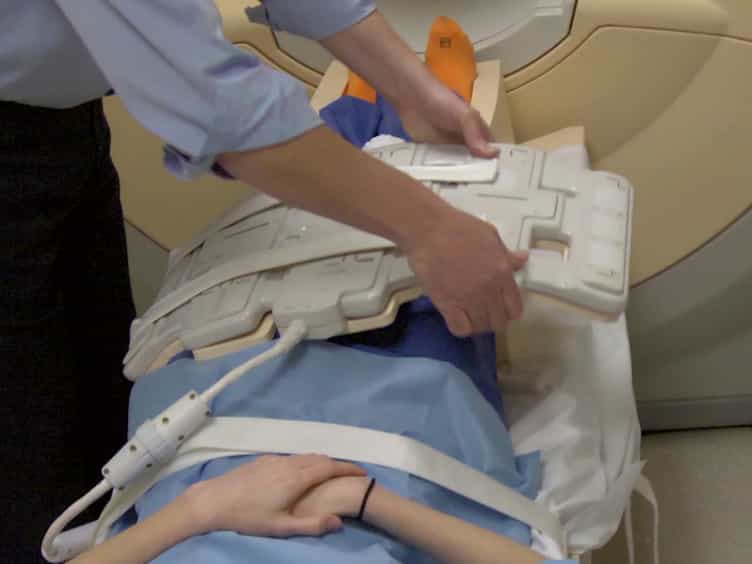
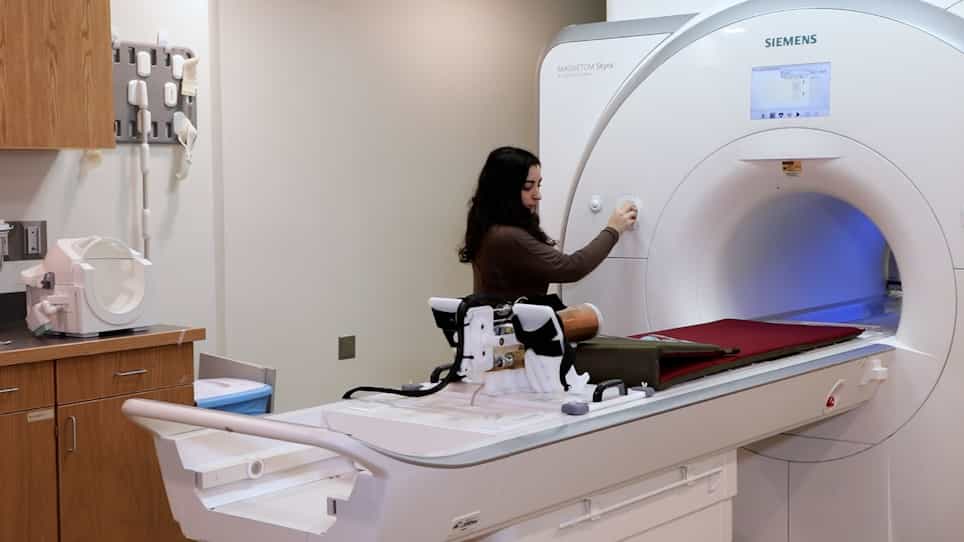
Related Experiment Video
Updated: Aug 7, 2026

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Quantifying Disease Progression in Patients With Charcot-Marie-Tooth Neuropathy Type 1A Using Quantitative Muscle MRI
Louise Iterbeke1, Lotte Huysmans2,3, Kobe Bamps4,5
1Laboratory for Muscle Diseases and Neuropathies, Department of Neurosciences, KU Leuven, Leuven Brain Institute (LBI) and Leuven Institute for Rare Diseases (L.IRD), Belgium.

Background And Objectives:
Charcot-Marie-Tooth neuropathy type 1A (CMT1A) is a slowly progressive demyelinating neuropathy with distal muscle weakness and atrophy. Sensitive, objective outcome measures are needed for future clinical trials. We aimed to identify responsive imaging and clinical biomarkers in CMT1A over 24 months.
Methods:
In this prospective, monocentric natural history study, ambulatory adults with genetically confirmed CMT1A and healthy controls were enrolled for 3 visits (baseline, 12, and 24 months). Quantitative muscle MRI quantified proton density fat fraction (PDFF, %) and disease activity with water T2 (T2H2O, ms), using automated 3D whole-muscle segmentation of 18 proximal and 10 distal leg muscles. Clinical outcomes comprised the Charcot-Marie-Tooth Neuropathy Score version 2 (CMTNSv2), Overall Neuropathy Limitations Score, 32-item Motor Function Measure (MFM32), 6-Minute Walk Distance (6MWD), 10-Meter Walk Test (10MWT), 30-Second Sit-to-Stand, 9-Hole Peg Test (9HPT), MRC sum score, and isometric strength testing. Patient-reported measures included the Individualized Neuromuscular Quality of Life (INQoL), ActivLim, Fatigue Severity Scale, and Brief Pain Inventory.
Results:
Thirty-three patients with CMT1A (43.8 years, 64% female) and 33 controls (42.2 years, 61% female) were included. At baseline, PDFF (%) was elevated in CMT1A across all leg muscles (p < 0.001). Distal leg PDFF (%) increased at 12 months (+1.1%, 95% CI 0.7-1.4, p < 0.001) and 24 months (+2.1%, 95% CI 1.4-2.8, p < 0.001). T2H2O in the anterolateral distal compartment increased at 12 months (+1.2 ms, 95% CI 0.3-2.1, p < 0.001) and 24 months (+1.5 ms, 95% CI 0.4-2.6, p < 0.001). Proximal leg PDFF (%) and T2H2O remained largely stable. The MFM32 total score declined at 12 months (-3.4%, 95% CI -4.1 to -2.6, p < 0.001) and 24 months (-5.8%, 95% CI -6.9 to -4.7, p < 0.001). INQoL scores worsened at 12 months (+15.1, 95% CI 10.0-20.2, p < 0.001) and 24 months (+23.6, 95% CI 18.8-28.7, p < 0.001). The 9HPT (+2.0s, 95% CI 0.5-3.4, p < 0.05) and CMTNSv2 (+3.3, 95% CI 2.2-4.5, p < 0.001) worsened at 24 months. Baseline distal leg PDFF (%) correlated with age, disease duration, 6MWD, 10MWT, MFM32, and MRC sum score.
Discussion:
Distal leg PDFF (%) from 3D whole-muscle segmentation detects CMT1A progression within 12 months. Combined with the MFM32 and INQoL, these measures enable sensitive 12-month endpoints for future clinical trials in adults with CMT1A.