Related Experiment Video
Updated: Aug 7, 2026

Assessing Urinary Tract Junction Obstruction Defects by Methylene Blue Dye Injection
Published on: October 12, 2017
Assessment of Suture Tension on an Advanced Ureteral Repair Simulator Using Black Light Assessment of Surgical
Alex T Gong1, Victoria A Roach1, Dan M Burke1
1Center for Research in Education and Simulation Technologies, Division of Healthcare Simulation Science, UW Medicine, University of Washington, Seattle, WA 98195-6410, United States.

Introduction:
The maintenance of skills to manage ureteral injuries present a significant challenge because of limited case exposure and training opportunities. The Department of Defense Individual Critical Task List Committee identified a requirement of a minimum of 5 traumatic ureteral repairs per year for skill maintenance. Ureteral repairs are thought to require a "tension-free" anastomosis to reduce the risk of tissue ischemia potentially resulting in anastomotic leak or delayed stricture. However, the term "tension-free" with respect to anastomoses, remains a qualitative assessment based on surgeon experience, and threshold appropriate tension has yet to be meaningfully quantified. A recently developed ureteral repair trainer, which incorporates black light assessment of surgical technique (BLAST) technology on the ureter, was used to quantify what an expert would otherwise qualitatively identify as a "tension-free" anastomosis.
Materials And Methods:
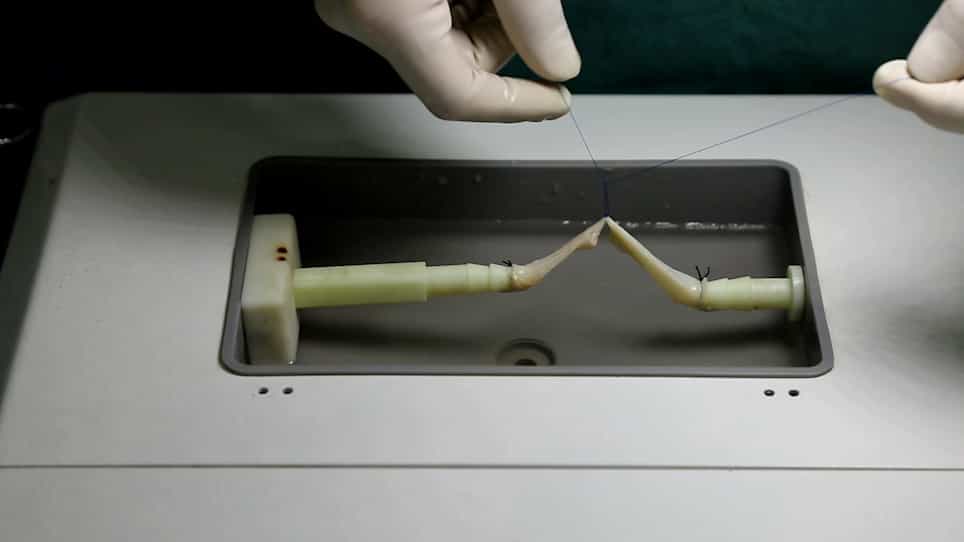
To create the ureteral repair puck, black light assessment of surgical technique (BLAST) was mixed into the synthetic ureter solution before casting it into a resin mold. The mold enabled the creation of reproducible 10 mm spaced lines along the ureter only visible under UV illumination. The completed ureteral repair puck was then integrated into the trainer. Expert reconstructive urologists attending the Society of Genitourinary Reconstructive Surgeons 2024 Conference were invited to perform ureteral-ureteral (UU) anastomosis and ureteroneocystostomy (ureteral reimplantation) repairs using the trainer. The study was determined to be human subjects research that qualifies for exempt status under category 2, based on a limited review by the IRB at the University of Washington (#STUDY00020202). After each procedure, wing dividers were used to transfer the in-situ distance between the BLAST lines under UV light to a set of calipers for manual measurement. We utilized a lab-developed uniaxial tensile tester to measure the corresponding tension based on the BLAST line displacement from the expert's tension-free technique on a fresh synthetic ureter.
Results:
Sixteen expert urologists performed a "tension-free" anastomosis on the ureteral repair trainer. Eight completed UU anastomosis, while the other 8 completed a ureteral reimplantation. Two urologists that completed the reimplantation were excluded from the primary analysis, as they indicated that their anastomosis was under too much tension. The mean distance between the lines of the BLAST markers for the UU and ureteral reimplantation were 10.35 ± 0.46 mm and 10.80 ± 0.67 mm, respectively. The corresponding forces for the UU and ureteral reimplantation at these grid distances were 0.013 N and 0.120 N, respectively.
Conclusions:
The purpose of this study was to quantify the tensile force of a "tension free" ureteral anastomosis using a recently developed high-fidelity ureteral repair trainer and integrated ureter puck, anchored by expert performance. This is the first study to quantify expert anastomosis performance in UU and ureteral reimplantation repair. Understanding the force of an expert surgeon's "tension-free" anastomosis can provide valuable training metrics to assess the cross-training performance of military general and trauma surgeons in ureteral repairs. Future work will involve a longitudinal study comparing non-expert surgeon forces to experts in ureteral anastomosis to support the Army ICTL requirements.