Related Experiment Video
Updated: Aug 8, 2026
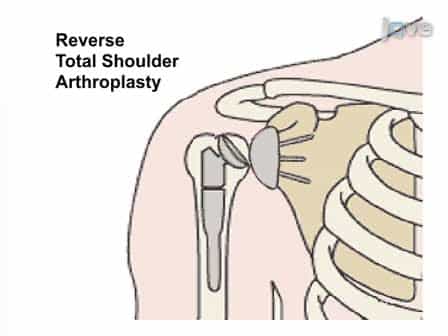
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Clinical impact of scapular stress fracture after reverse total shoulder arthroplasty: a single-center propensity
By Chul-Hyun Cho1, Hyuk-Joon Sohn1, Du-Han Kim1
1Department of Orthopedic Surgery, Keimyung University Dongsan Hospital, Keimyung University School of Medicine, Daegu, Republic of Korea.

Background:
Scapular stress fracture (SSF) is a recognized complication after reverse total shoulder arthroplasty (rTSA), yet its clinical impact remains controversial. This study aimed to determine the incidence of SSF after rTSA; to compare outcomes with a 1:3 propensity score‑matched control group; and to evaluate the influence of fracture location, treatment modality, and radiographic union on clinical outcomes.
Methods:
A total of 551 consecutive primary rTSAs performed between January 2010 and December 2024 at a single tertiary referral center were retrospectively reviewed. Thirty patients developed post-operative SSF; 28 with a minimum follow-up of 12 months after SSF diagnosis were included for outcome analysis. Eighty-four control patients without SSF were selected using 1:3 propensity score matching based on age, sex, bone mineral density, implant type, and history of prior shoulder surgery. Clinical outcomes included visual analog scale pain score, University of California, Los Angeles score, American Shoulder and Elbow Surgeons score, subjective shoulder value, and active range of motion (ROM). Sub-group analyses were conducted according to fracture location, treatment modality, and radiographic union. The mean follow-up duration after rTSA was 52.5 ± 36.2 months and 47.1 ± 27.1 months in the SSF and control groups, respectively.
Results:
The incidence of SSF was 5.4% (30 of 551 cases). Final visual analog scale pain score, University of California, Los Angeles score, American Shoulder and Elbow Surgeons score, and subjective shoulder value did not differ significantly between groups. However, the SSF group demonstrated significantly reduced forward flexion (126.1° vs. 136.2°, P = .011) and abduction (103.2° vs. 117.3°, P = .003). According to the Levy classification, there were 4 type I, 16 type II, and 8 type III fractures. Fracture location significantly affected final forward flexion (P = .046) and abduction (P = .037), with type III fractures demonstrating the poorest ROM. Treatment modality (operative vs. non-operative) and radiographic union did not significantly influence the final clinical outcomes.
Conclusion:
SSF occurred in 5.4% of primary rTSAs. Although patient-reported outcomes were comparable to matched controls, SSF was associated with significantly decreased shoulder elevation. Fracture location influenced ROM recovery, whereas treatment modality and radiographic union did not significantly affect the final clinical outcomes.