Related Experiment Video
Updated: Aug 8, 2026
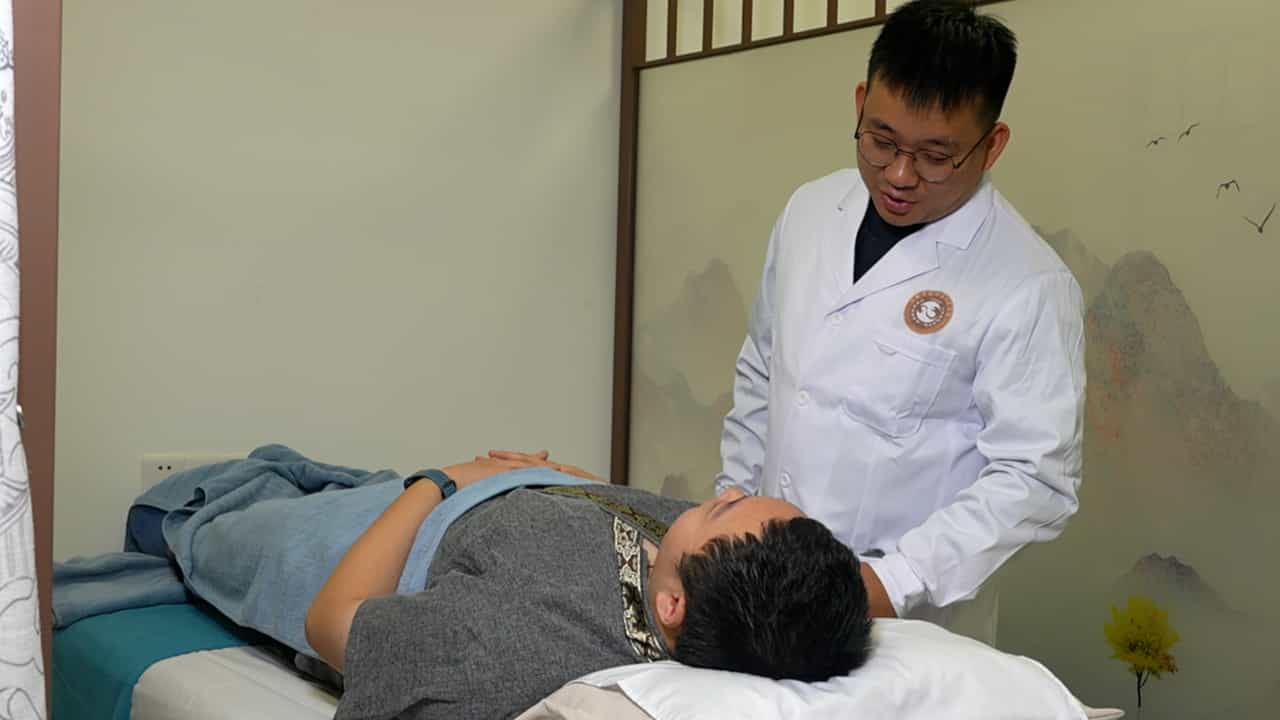

Alternative Therapy for Acute Exacerbation of Chronic Obstructive Pulmonary Disease: Moving Cupping Along Meridians
Published on: September 27, 2024
Symptom trajectory types during recovery from acute exacerbation of COPD and their association with systemic
1Department of Internal Medicine, Xianju Hospital of Traditional Chinese Medicine, Taizhou City, Zhejiang Province, China.

Objective:
To identify symptom trajectory types during recovery from AECOPD using GBTM, explore the role of admission systemic inflammatory burden (assessed by CRP and PCT) in shaping recovery heterogeneity, and analyze the association between trajectory types and prognosis.
Methods:
A total of 216 AECOPD patients hospitalized between January 2023 and December 2024 were enrolled. CAT and mMRC were used to assess symptom changes at 7 time points from admission to 12 weeks post-discharge. Admission systemic inflammatory biomarkers (CRP and PCT) were collected as biomarkers of inflammatory burden. Sepsis was defined according to Sepsis-3 criteria as life-threatening organ dysfunction caused by a dysregulated host response to infection, identified by an acute SOFA score increase of ≥2 points. Available SOFA components included the respiratory sub-score (derived from PaO2/FiO2) and the coagulation sub-score; hepatic, renal, cardiovascular, and neurological sub-scores were not systematically collected. Accordingly, formal complete SOFA-based Sepsis-3 classification was not feasible; CRP and PCT are used herein as surrogate biomarkers of systemic inflammatory burden alongside partial SOFA data. GBTM was applied using the traj procedure in SAS 9.4 to identify symptom recovery trajectory types, and baseline characteristics and prognostic differences were compared among trajectory groups. Cox proportional hazards regression and Fine-Gray competing risk models were used to analyze the association between trajectory types and first re-exacerbation risk. Negative binomial regression was used to analyze the association between trajectory types and re-exacerbation and rehospitalization frequency. Multivariable logistic regression was used to identify independent predictors of non-rapid recovery trajectories.
Results:
Four symptom recovery trajectory types were identified: rapid recovery group (82 cases, 38.0%), slow recovery group (62 cases, 28.7%), persistent symptoms group (48 cases, 22.2%), and symptom rebound group (24 cases, 11.1%). Patients in non-rapid recovery groups exhibited significantly higher admission inflammatory biomarker levels (CRP and PCT) compared to the rapid recovery group (all P < 0.05). The median time to first re-exacerbation was 248, 156, 78, and 102 days, respectively (P < 0.001). Multivariable Cox regression showed that, using the rapid recovery group as reference, the slow recovery group (aHR = 1.62, 95%CI: 1.08-2.42), persistent symptoms group (aHR = 2.58, 95%CI: 1.68-3.96), and symptom rebound group (aHR = 2.24, 95%CI: 1.32-3.80) all had elevated first re-exacerbation risk (all P < 0.05). Negative binomial regression showed that non-rapid recovery groups had increased re-exacerbation and rehospitalization counts within 12 months (all P < 0.05). Higher admission CAT score (OR = 1.18), lower FEV1%pred (OR = 0.96), ≥2 exacerbations in the previous year (OR = 2.42), higher admission CRP (OR = 1.01, an admission inflammatory biomarker), and current smoking (OR = 2.15) were independent predictors of non-rapid recovery trajectory (all P < 0.05).
Conclusion:
Symptom trajectories during AECOPD recovery are heterogeneous, and elevated admission systemic inflammatory burden is associated with non-rapid recovery. Non-rapid recovery trajectories are associated with increased re-exacerbation risk and worse quality of life. Trajectory-based prognostic stratification combined with early inflammatory burden assessment may facilitate identification of high-risk patients and development of individualized follow-up management strategies.
Related Concept Videos
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...