Related Experiment Video
Updated: Aug 8, 2026
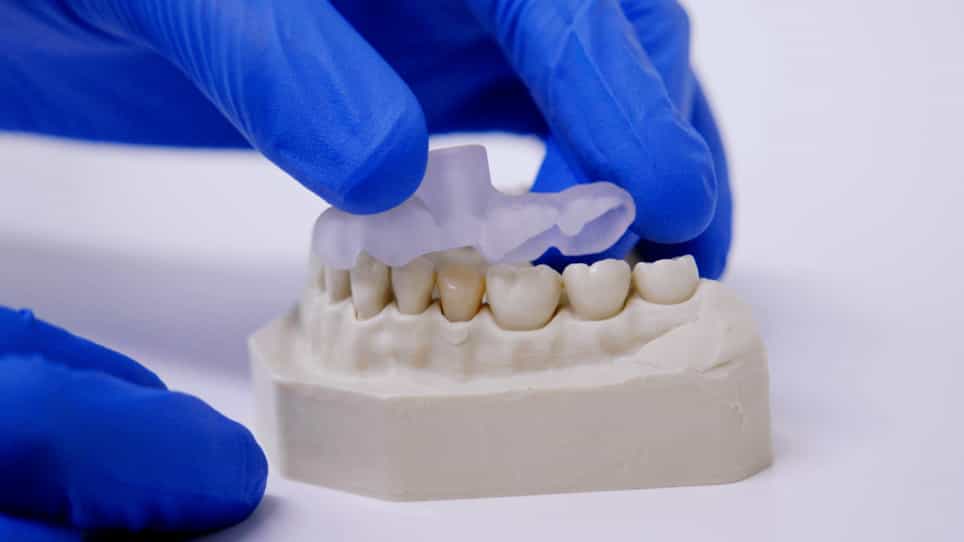

Guided Endodontics: Three-Dimensional Planning and Template-Aided Preparation of Endodontic Access Cavities
Published on: May 24, 2022
Accuracy of working length determination using endodontic motors with integrated electronic apex locators: an in
Huynh-Anh Bui1, Minh-Anh Bui2, Thi-Thuy-Trang Huynh1
1Faculty of Dentistry, University of Medicine and Pharmacy at Ho Chi Minh City, Ho Chi Minh City, Vietnam.

Abstract:
The aim of the present study was to evaluate the accuracy of endodontic motors with an integrated electronic apex locator (EAL) for determining endodontic working length under in vitro conditions. A total of twenty-six extracted human mandibular single-canal premolars were included and scanned via cone-beam computed tomography (CBCT), three-dimensionally reconstructed, and then allocated equally into two device groups (n = 13 each). The teeth were accessed and a glide path was prepared with a manual K-file before the canals were prepared with a continuous single-file system (One Curve, Micro-Mega, Besançon, France) driven by one of two integrated endodontic motor/EAL systems (Connect Drive, VDW; and E-Connect S, Eighteeth) until the auto-apical-reverse ("apex") signal was displayed. The teeth were scanned by CBCT a second time after preparation, and 3D reconstruction was performed to determine the post-preparation endpoint. Subtraction of the pre- and post-preparation images was used to evaluate the accuracy of the working length relative to the directly measured actual length. The data were analysed using Bland-Altman agreement analysis (mean bias and 95% limits of agreement) in MedCalc, with between-device comparison performed using a test appropriate for the independent two-group design; significance was set at 0.05. There was no significant difference in working length between the two integrated systems. Under the present in vitro conditions, neither integrated motor/EAL system produced measurements identical to the reference length, although the deviations were small: the mean bias of the auto-apical-reverse endpoints relative to the actual length ranged from approximately 0.13 to 0.26 mm, remaining within the ±0.5 mm clinical tolerance, and the largest single deviation recorded was 0.79 mm short of the major apical foramen. The working length should therefore be confirmed using complementary methods rather than relying solely on the auto-reverse endpoint.
