Related Experiment Video
Updated: Aug 8, 2026
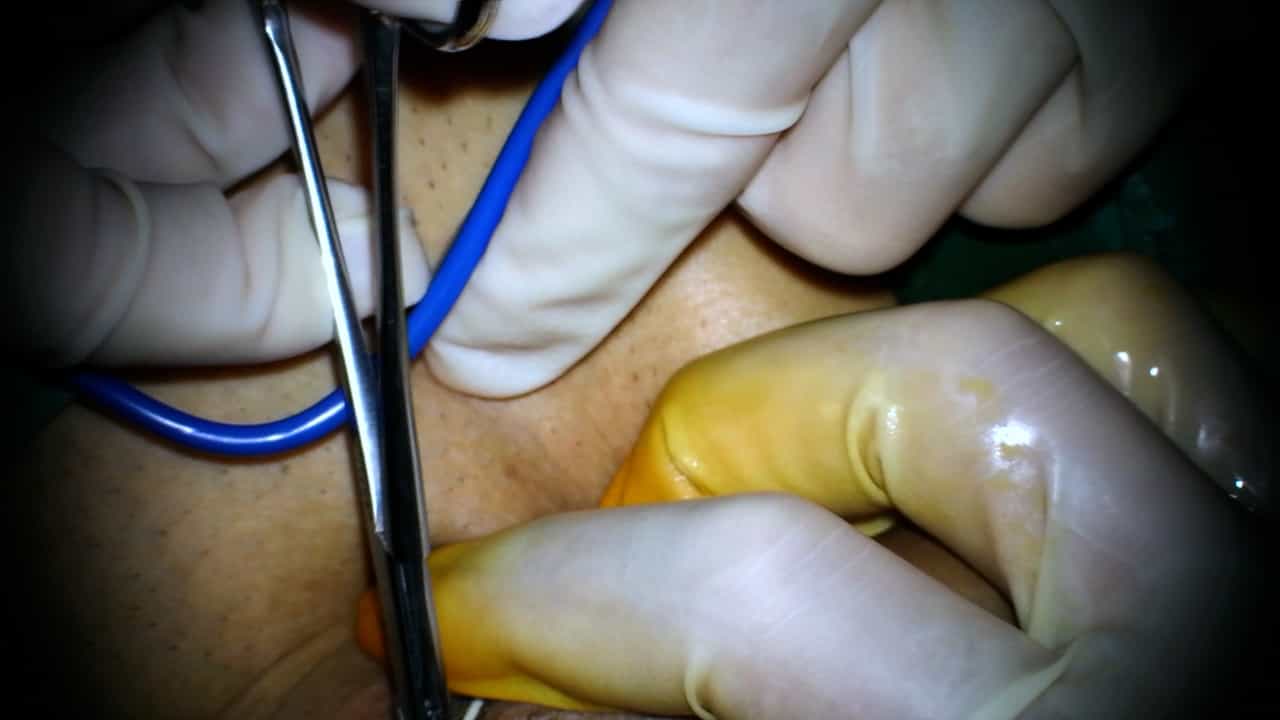

Microscopic Electric Rotary Grinding of Plaques Combined with Graft Repair in the Management of Peyronie's Disease
Published on: March 15, 2024
Active Peyronie's disease as an early antifibrotic treatment window: a translational review
Marek Broul1,2,3, Michaela Liegertová4, Aneta Hujová3
1Department of Sexology, Krajská zdravotní, a.s. - Masaryk Hospital in Ústí nad Labem, o.z., Ústí nad Labem 400 11, Czech Republic.

Introduction:
Peyronie's disease (PD) is an acquired fibrotic disorder of the tunica albuginea that can cause pain, curvature, deformity, erectile dysfunction, and substantial psychosexual burden. Management is usually guided by disease phase, yet active disease remains inconsistently defined, and no oral regimen has shown high-certainty disease-modifying efficacy. We synthesize clinical, mechanistic, guideline, outcome-measure, traction, and public-data evidence relevant to active or progressive PD as a target for early antifibrotic trials.
Methods:
We conducted a targeted narrative translational review of full-text sources on active-phase definitions, PDE5 inhibitor/selective estrogen receptor modulator (SERM) pharmacology, tadalafil-based clinical studies, placebo-controlled tamoxifen evidence, current recommendations, non-surgical evidence reviews, patient-reported outcome measures, traction therapy, and PD transcriptomic or single-cell studies. We selected sources through targeted database searching, citation chasing, and full-text evidence audit; no protocol-registered systematic review was performed. Clinical studies were heterogeneous and largely non-randomized; therefore, we did not attempt a pooled efficacy estimate.
Results:
Active and stable PD remain clinically useful categories, although their operational definitions vary across studies. Experimental PD models identify fibroblast-to-myofibroblast transformation as a pharmacologically accessible process, with PDE5 inhibitors and SERMs showing timing-dependent antifibrotic effects. Retrospective PDE5 inhibitor studies and clinical audits of PDE5 inhibitor plus tamoxifen therapy report mixed observations on progression and pain, but interpretation is constrained by non-randomized design, small or imbalanced controls, confounding, and heterogeneous endpoints. Placebo-controlled monotherapy evidence remains negative or neutral for tamoxifen, especially when disease duration is broad or not stratified by active inflammatory features. Guidelines and evidence reviews support individualized conservative care without endorsing PDE5 inhibitor/SERM therapy as standard practice.
Conclusion:
Active/progressive PD is a defensible setting for early antifibrotic trials. PDE5 inhibitor/SERM therapy is among the best-developed mechanistic candidates, but remains investigational. Clinical adoption requires prospective, randomized, stage-defined studies with standardized curvature assessment, plaque imaging, erectile-function measurement, pain assessment, co-intervention documentation, adverse-event capture, and PD-specific patient-reported outcomes.
Related Concept Videos
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:27
Peripheral Artery Disease III: Interprofessional Care