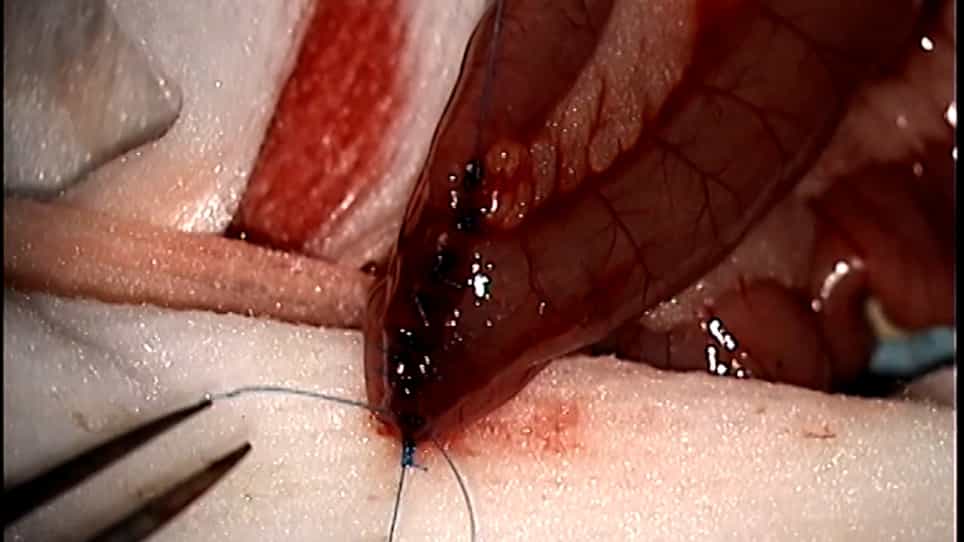
Related Experiment Video
Updated: Aug 9, 2026


Techniques of Sleeve Gastrectomy and Modified Roux-en-Y Gastric Bypass in Mice
Published on: March 20, 2017
Outcomes of sleeve gastrectomy and Roux-en-Y gastric bypass in patients with liver disease and body mass index ≥ 40:
Raul Sebastian1, Alba Zevallos2, Oscar Tuesta3
1Department of Surgery, The Johns Hopkins University, Baltimore, MD; Department of Surgery, Northwest Hospital, Randallstown, MD.

Background:
Nonalcoholic fatty liver disease (NAFLD), prevalent in bariatric surgery patients, is a leading indication for liver transplantation. However, class III obesity is a relative contraindication for transplantation.
Objective:
To evaluate the safety of bariatric surgery in patients with mild to moderate liver disease of any cause.
Setting:
2023 Metabolic and Bariatric Surgery Accreditation and Quality Improvement Program (MBSAQIP) database.
Methods:
Patients who underwent sleeve gastrectomy (SG) and Roux-en-Y gastric bypass (RYGB) were included. We performed a 1:1 propensity score matching analysis with 27 preoperative characteristics. We compared 30-day postoperative outcomes for patients with body mass index (BMI) < 40 with versus without liver disease after SG (Analysis 1) or RYGB (Analysis 2) and for patients with BMI ≥ 40 with versus without liver disease after SG (Analysis 3) or RYGB (Analysis 4).
Results:
From 182,673 patients (71% SG; 29% RYGB), outcomes in analysis 1 showed that patients with liver disease are associated with higher rates of surgical site infection (SSI), and blood transfusions (P < .05). Analysis 2 showed that patients with liver disease are associated with higher rates of emergency visits, readmissions, reoperations, and SSI (P < .05). In analysis 3, patients with liver disease had higher rates of unplanned intensive care unit admission, emergency visits, SSI, blood transfusions, and readmissions (P < .05). In analysis 4, patients with liver disease had higher rates of emergency visits and SSI (P < .05). However, there were no differences across the four analyses in mortality and cardiopulmonary complications.
Conclusion:
Bariatric surgery in patients with liver disease is safe and feasible with similar mortality and cardiopulmonary complications compared to patients without liver disease. However, patients with liver disease have a higher rate of complications, including emergency visits, SSI, readmissions, and blood transfusions after bariatric surgery. Furthermore, patients with liver disease and BMI ≥40 have higher rates of unplanned intensive care unit admission, emergency visits, readmissions, and reoperations.