Related Experiment Video
Updated: Aug 10, 2026
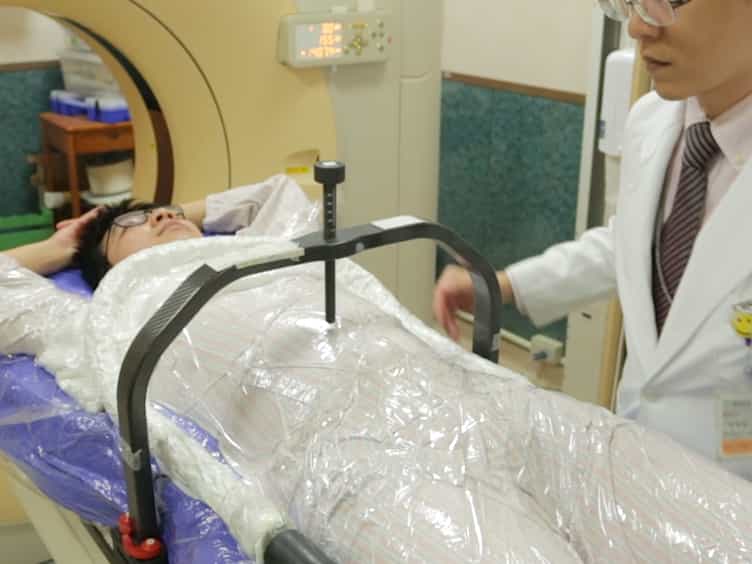
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Local and symptomatic control evaluation in palliative radiotherapy for rectal adenocarcinoma in frail, elderly, or
Eva Bisson1, R Nebbache1, L Quéro2
1Service d'Oncologie Radiothérapie, Hôpital Tenon, AP-HP, Sorbonne Université, Paris, France.

Background:
Locally advanced rectal cancer can cause severe pelvic symptoms (pain, hemorrhage, obstruction) in elderly, frail, or metastatic patients often unfit for surgery or optimal systemic therapy. The Swedish hypofractionated schedule (25 Gy in 5 fractions over 5 days) is widely used and effective in the neoadjuvant setting, but its role in palliation remains uncertain. Optimal dose and treatment duration remain to be defined. This study evaluates local and symptomatic control and treatment-related toxicity of different palliative irradiation schedules.
Materials And Methods:
This retrospective study included patients treated with palliative radiotherapy for symptomatic, locally advanced, or metastatic rectal adenocarcinoma between 2010 and 2020 in five AP-HP Radiation Oncology departments. The primary endpoint was 6-month local control. Secondary endpoints were symptomatic response, overall survival, and toxicity. Survival was estimated using the Kaplan-Meier method and compared using log-rank test, categorical variables were compared using Fisher's exact test, and correlation using Spearman's coefficient.
Results:
Sixty-three patients were included (median age of 80 years) with predominantly locally advanced disease (86% T3-T4), and frequent metastases (54%). With a median follow-up of 13.3 months, the local control was 46% at 6 months (95% CI: 33.6-59) and 22.2% at 1 year (95% CI: 13-34.8). Local control did not differ significantly between irradiation schedules but tended to be higher for BED >37.5 Gy (66.7% vs. 33.3%; p = 0.2). A statistically significant improvement in symptomatic control was observed for BED >37.5 Gy (93.3% vs. 55.6%; p = 0.002), and for the 30 Gy in 10 fractions schedule (92.3% vs. 70%; p = 0.048). Symptomatic and local control were correlated (p < 0.001).
Conclusions:
Higher BED was associated with improved symptomatic control and a non-significant numerical increase in local control compared with the Swedish schedule. Dose escalation, including hypofractionated IMRT using simultaneous integrated boost warrant further evaluation.