Related Experiment Video
Updated: Aug 10, 2026

Lateral Molar Approach-Driven Transoral Endoscopic Procedure for Benign Infratemporal Fossa Tumor Resection
Published on: August 15, 2025
Occult Advanced Gastric Cancer Revealed by Intraosseous Mandibular Metastasis: A Case Report
Yudai Shimojukkoku1,2, Jun Sumino1, Miki Katsurano1
1Department of Oral Surgery, Saitama Cancer Center, Ina, Japan.

Introduction:
Metastases to oral and maxillofacial regions are uncommon and may mimic odontogenic infection or primary intraosseous malignancy. Mandibular involvement in patients with gastric cancer is particularly rare, and delayed recognition may postpone definitive diagnosis.
Case Presentation:
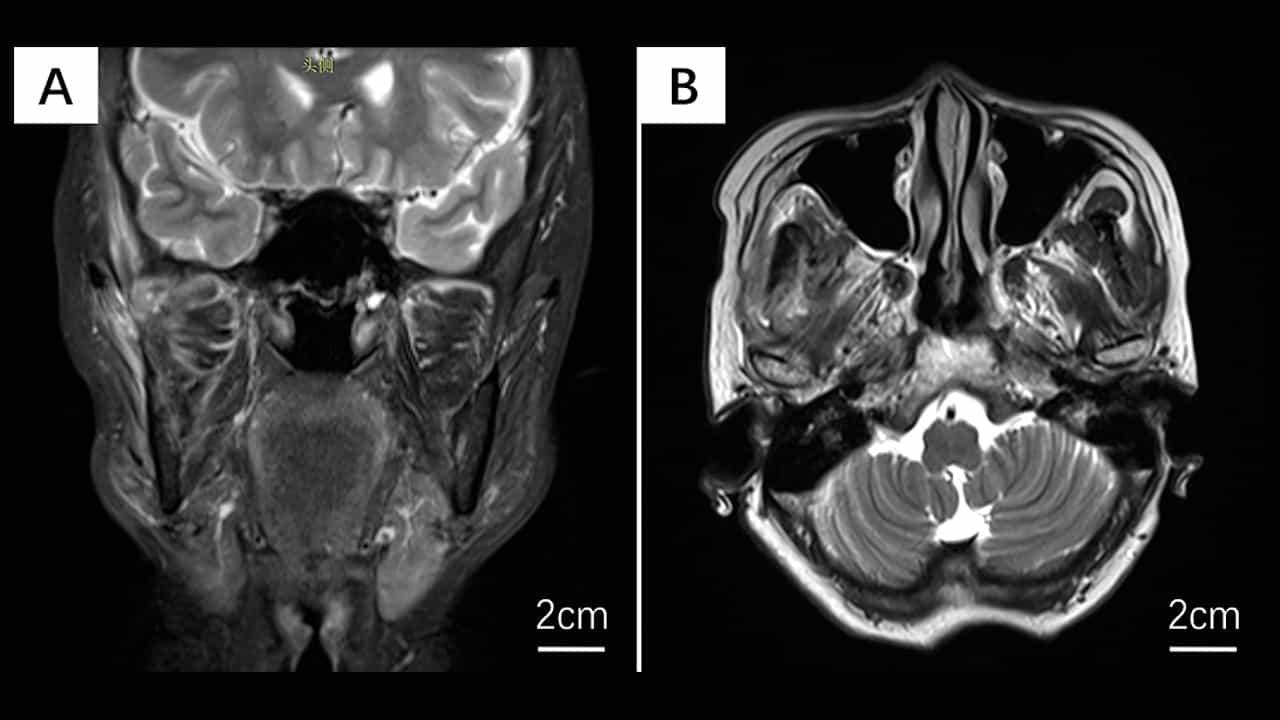
A 61-year-old man presented with numb-chin syndrome and a nonhealing mandibular extraction socket. Panoramic radiography and CT revealed an ill-defined osteolytic lesion in the left mandible with suspected extraosseous extension. Although primary intraosseous carcinoma was initially suspected, histopathological reevaluation of the mandibular biopsy specimen suggested metastatic adenocarcinoma. 18F-FDG PET/CT demonstrated uptake in the mandible and a suspected primary lesion extending from the lower thoracic esophagus to the stomach, with multiple nodal and distant metastases. Upper gastrointestinal endoscopy revealed an ulcerated, bleeding mass at the gastroesophageal junction, and biopsy demonstrated adenocarcinoma. Based on the combined clinicopathologic, radiologic, and endoscopic findings, the lesion was diagnosed as mandibular metastasis from an advanced upper gastrointestinal adenocarcinoma, clinically managed as gastric cancer. The patient received four cycles of FOLFOX chemotherapy and achieved a partial radiologic response, but treatment was discontinued because of gastrointestinal perforation. He was transitioned to best supportive care and died 7 months after the initial diagnosis.
Conclusion:
Metastatic disease should be considered for patients with ill-defined mandibular osteolysis accompanied by numb-chin syndrome and a nonhealing extraction socket, even in cases without a history of malignancy. To avoid diagnostic delay, early tissue diagnosis and prompt systemic evaluation are critical.
