Related Experiment Video
Updated: Aug 10, 2026


High-Resolution Endocardial and Epicardial Optical Mapping in a Sheep Model of Stretch-Induced Atrial Fibrillation
Published on: July 29, 2011
Atrial Fibrillation Initiation Arises From Reentry at Patient-Specific Regions With Steep Repolarization Gradients
Elad Anter1, Michael Barkagan1, Dor Yadin1
1Cardiac Electrophysiology Section, Division of Cardiovascular Medicine, Shamir Medical Center, Be'er Yaakov, Israel; Gray Faculty of Medical and Health Sciences, Tel Aviv University, Tel Aviv, Israel.

Background:
The mechanism by which ectopic beats initiate atrial fibrillation (AF) remains undefined.
Objectives:
This study sought to define the mechanism and underlying substrate of AF initiation.
Methods:
In 57 patients with AF and 24 controls, biatrial mapping with programmed extrastimulation during sinus rhythm was performed to characterize refractoriness, conduction, and AF inducibility. Multiple convergent electrophysiological parameters were assessed at initiation and noninitiation sites to define the mechanism of AF onset. In an exploratory cohort, 24 redo patients with durable pulmonary vein isolation (PVI; 50% with persistent AF) underwent ablation confined to mechanistically identified sites.
Results:
AF was reproducibly induced and localized to discrete, patient-specific sites (1.8 ± 1.0 per patient), representing only 2.8% of tested locations. These sites were strongly associated with steep repolarization gradients (SRGs; AERP difference ≥50 milliseconds over ≤10 millimeters), present in 91.7% of patients with AF vs 8.3% of controls (P < 0.001), accounting for 92.2% of all AF initiation episodes, and representing the strongest electrophysiological correlate of AF initiation, whereas low bipolar voltage was non-discriminatory. PV-associated SRGs predominated in paroxysmal AF, with increasing non-PV substrate in persistent AF and redo patients with durable PVI; in redo patients with durable PVI, SRG sites involved the left and right atria in 70% and 30% of sites, respectively. Multiple convergent electrophysiological observations supported reentry as the predominant mechanism, including a narrow vulnerability window, direction-dependent initiation, functional conduction block preceding AF onset, and organized pan-diastolic activation at AF onset. In redo patients with durable PVI, ablation confined to identified SRG sites achieved 87.5% freedom from atrial arrhythmia without antiarrhythmic drugs over a median follow-up of 489 days.
Conclusions:
AF initiation arises from a localized, patient-specific substrate capable of supporting reentry that can be identified using programmed stimulation during sinus rhythm. These findings provide a mechanistic basis for transitioning from empiric to individualized, substrate-guided ablation strategies.

Related Concept Videos
 01:25
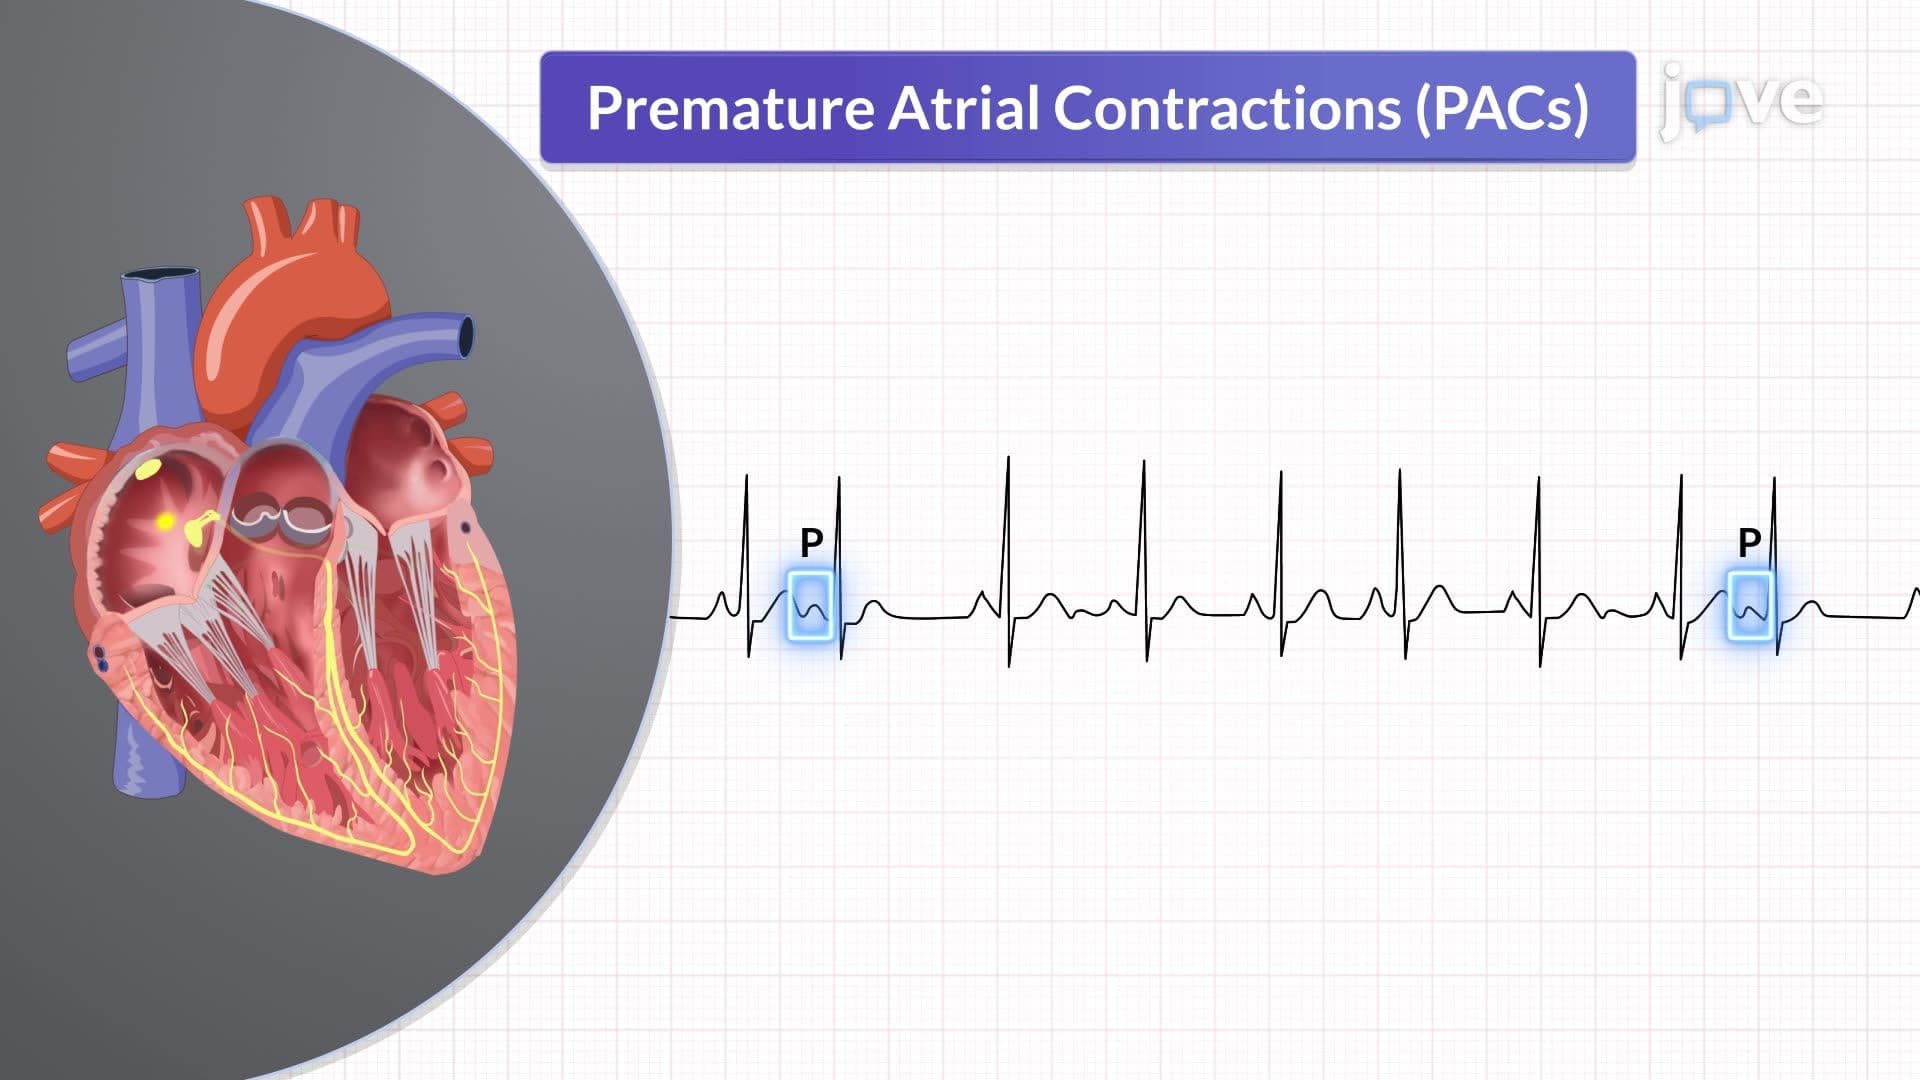
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:30
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials