Related Experiment Video
Updated: Aug 11, 2026
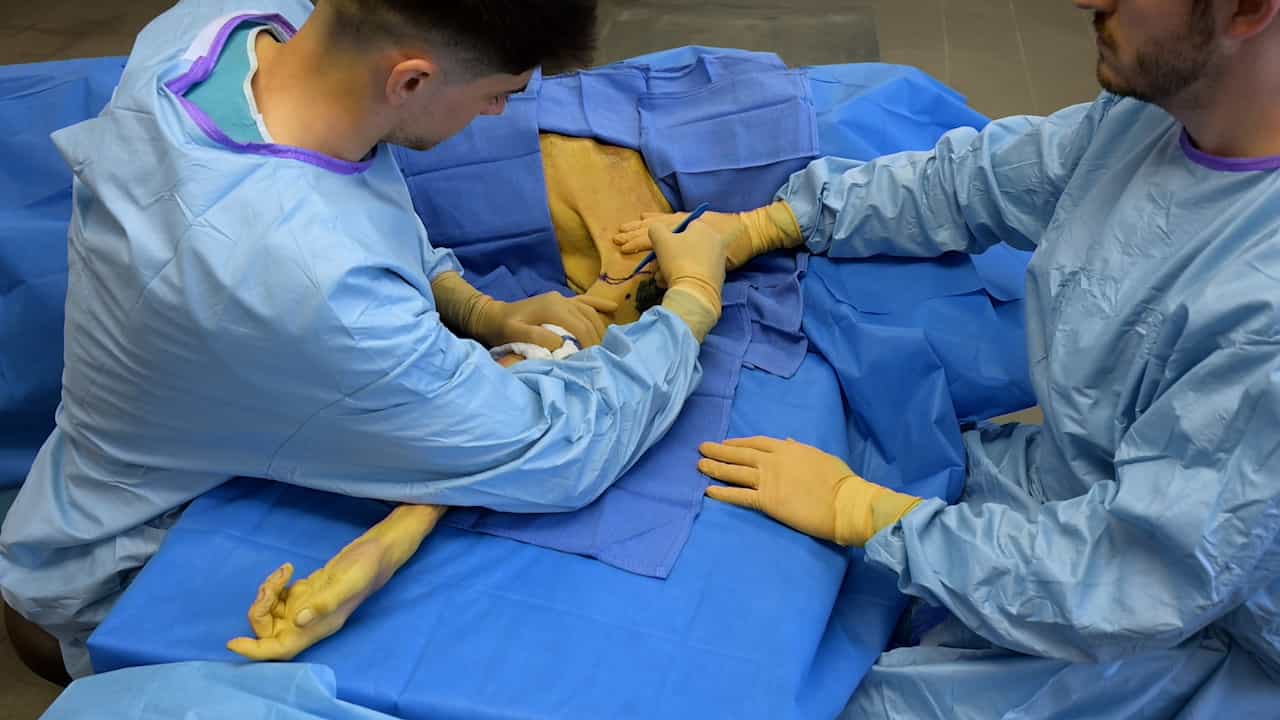

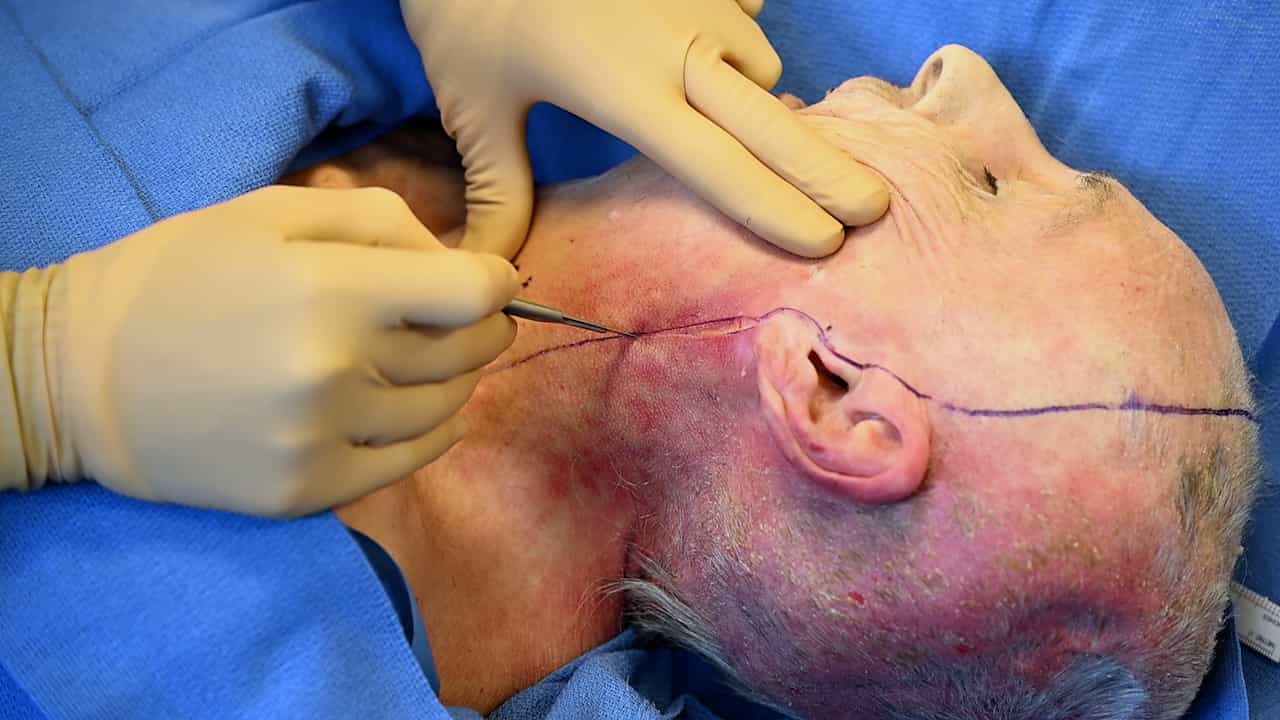
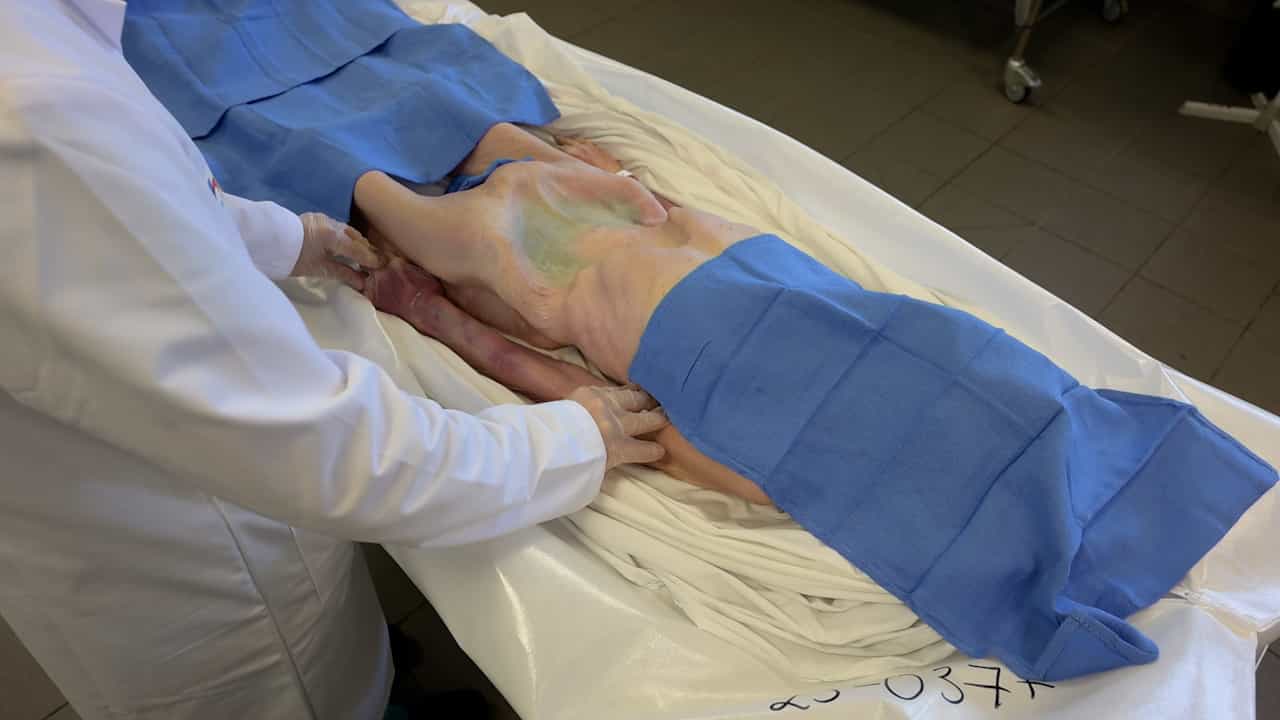
Vascularized Composite Upper Limb Allograft Harvesting for Proximal Arm Allotransplantation
Published on: June 13, 2025
Posttransplant lymphoproliferative disorder in vascularized composite allotransplantation: a systematic review with
Ramu Janarthanan1,2, Sree Valli1, Sam Thomas1
1Department of Plastic and Reconstructive Surgery, Amrita Institute of Medical Sciences and Research Center, Amrita Vishwa Vidyapeetham, Kochi, India.

Background:
Posttransplant lymphoproliferative disorder (PTLD) is a serious complication, yet its presentation and consequences after vascularized composite allotransplantation (VCA) remain poorly characterized. Disease control must be balanced against graft preservation, rejection risk, and allograft loss.
Methods:
A systematic review was performed in accordance with PRISMA (Preferred Reporting Items for Systematic reviews and Meta-Analyses) 2020 across PubMed, Scopus, and Embase to identify PTLD after skin-bearing human VCA. Extracted variables included recipient and graft characteristics, immunosuppression, Epstein-Barr virus data, histopathology, treatment, graft outcome, and patient outcome. Two institutional bilateral upper extremity VCA recipients with PTLD were reviewed and integrated with the literature.
Results:
The review identified eight reports describing nine unique published cases of PTLD after VCA. Including two institutional cases yielded 11 patients. Grafts included face (n=5), upper extremity (n=4), lower extremity (n=1), and abdominal wall (n=1) allotransplants. PTLD developed between 4 months and 11 years after transplantation. Initial management included immunosuppression reduction and rituximab-based therapy; chemotherapy was used for disseminated or progressive disease. Graft explantation occurred in four cases, predominantly in face recipients, whereas graft preservation was achieved in selected patients, including both institutional upper extremity recipients. Four patients died of PTLD or related complications.
Conclusions:
PTLD after VCA is rare but clinically significant. Outcomes are heterogeneous, and graft explantation is not uniformly required. In selected patients, early diagnosis, individualized immunosuppression reduction, graft surveillance, and oncologic management may permit disease control with graft preservation. These findings may support multidisciplinary decision-making, although interpretation is limited by the small number of cases.