Related Experiment Video
Updated: Aug 11, 2026

A Simple and Rapid Method for Simultaneous Isolation of Primary Islets and Primary Pancreatic Acinar Cells from Mice
Published on: January 9, 2026
Autoimmune Pancreatitis, Diabetic Ketoacidosis, and Severe Hypertriglyceridemia: Unraveling a Pathophysiological
Deive Vinga Akoubou1, Inass Chaari1, Cheick Oumar Keita1
1Endocrinology, Diabetes and Metabolism, Avicenna Military Hospital, Marrakech, MAR.

Abstract:
Autoimmune pancreatitis (AIP) is a rare form of chronic pancreatitis and an uncommon cause of recurrent acute pancreatitis. Although diabetes mellitus is a frequent manifestation of AIP, presentation as diabetic ketoacidosis (DKA) is exceptional. The coexistence of DKA and severe hypertriglyceridemia (HTG) in the setting of AIP represents a rare clinical association with important diagnostic and therapeutic implications. A 43-year-old man with type 2 diabetes mellitus and two previous episodes of HTG-associated acute pancreatitis presented with severe epigastric pain, persistent vomiting, and Kussmaul respiration. Laboratory investigations revealed moderate DKA (pH, 7.12; bicarbonate, 12 mmol/L), severe HTG (16.0 g/L), and markedly elevated serum lipase (600 IU/L). Contrast-enhanced abdominal CT demonstrated diffuse pancreatic enlargement with a characteristic sausage-shaped appearance and Balthazar grade E acute pancreatitis. The recurrence of pancreatitis, together with the characteristic imaging findings, prompted suspicion of type 1 AIP. Serum IgG4 levels were subsequently found to be elevated (240 mg/dL), further supporting the diagnosis in accordance with the International Consensus Diagnostic Criteria. The patient was treated with aggressive intravenous fluid resuscitation, continuous intravenous insulin infusion, and early corticosteroid therapy, resulting in rapid clinical improvement and normalization of metabolic abnormalities within 72 hours. This case illustrates a rare association between type 1 AIP, DKA, and severe HTG. We propose a biologically plausible pathophysiological interaction in which pancreatic inflammation may have contributed to transient insulin deficiency, precipitating DKA and subsequently promoting severe HTG, thereby perpetuating pancreatic injury. Although this sequence cannot be established from a single case, recognizing this uncommon presentation may facilitate earlier diagnosis and appropriate multidisciplinary management. AIP should be considered in patients presenting with recurrent pancreatitis associated with DKA, severe HTG, and characteristic pancreatic imaging findings. Early recognition and timely multidisciplinary management may improve clinical outcomes. Further studies are needed to better define the relationship between these conditions.

Related Concept Videos
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
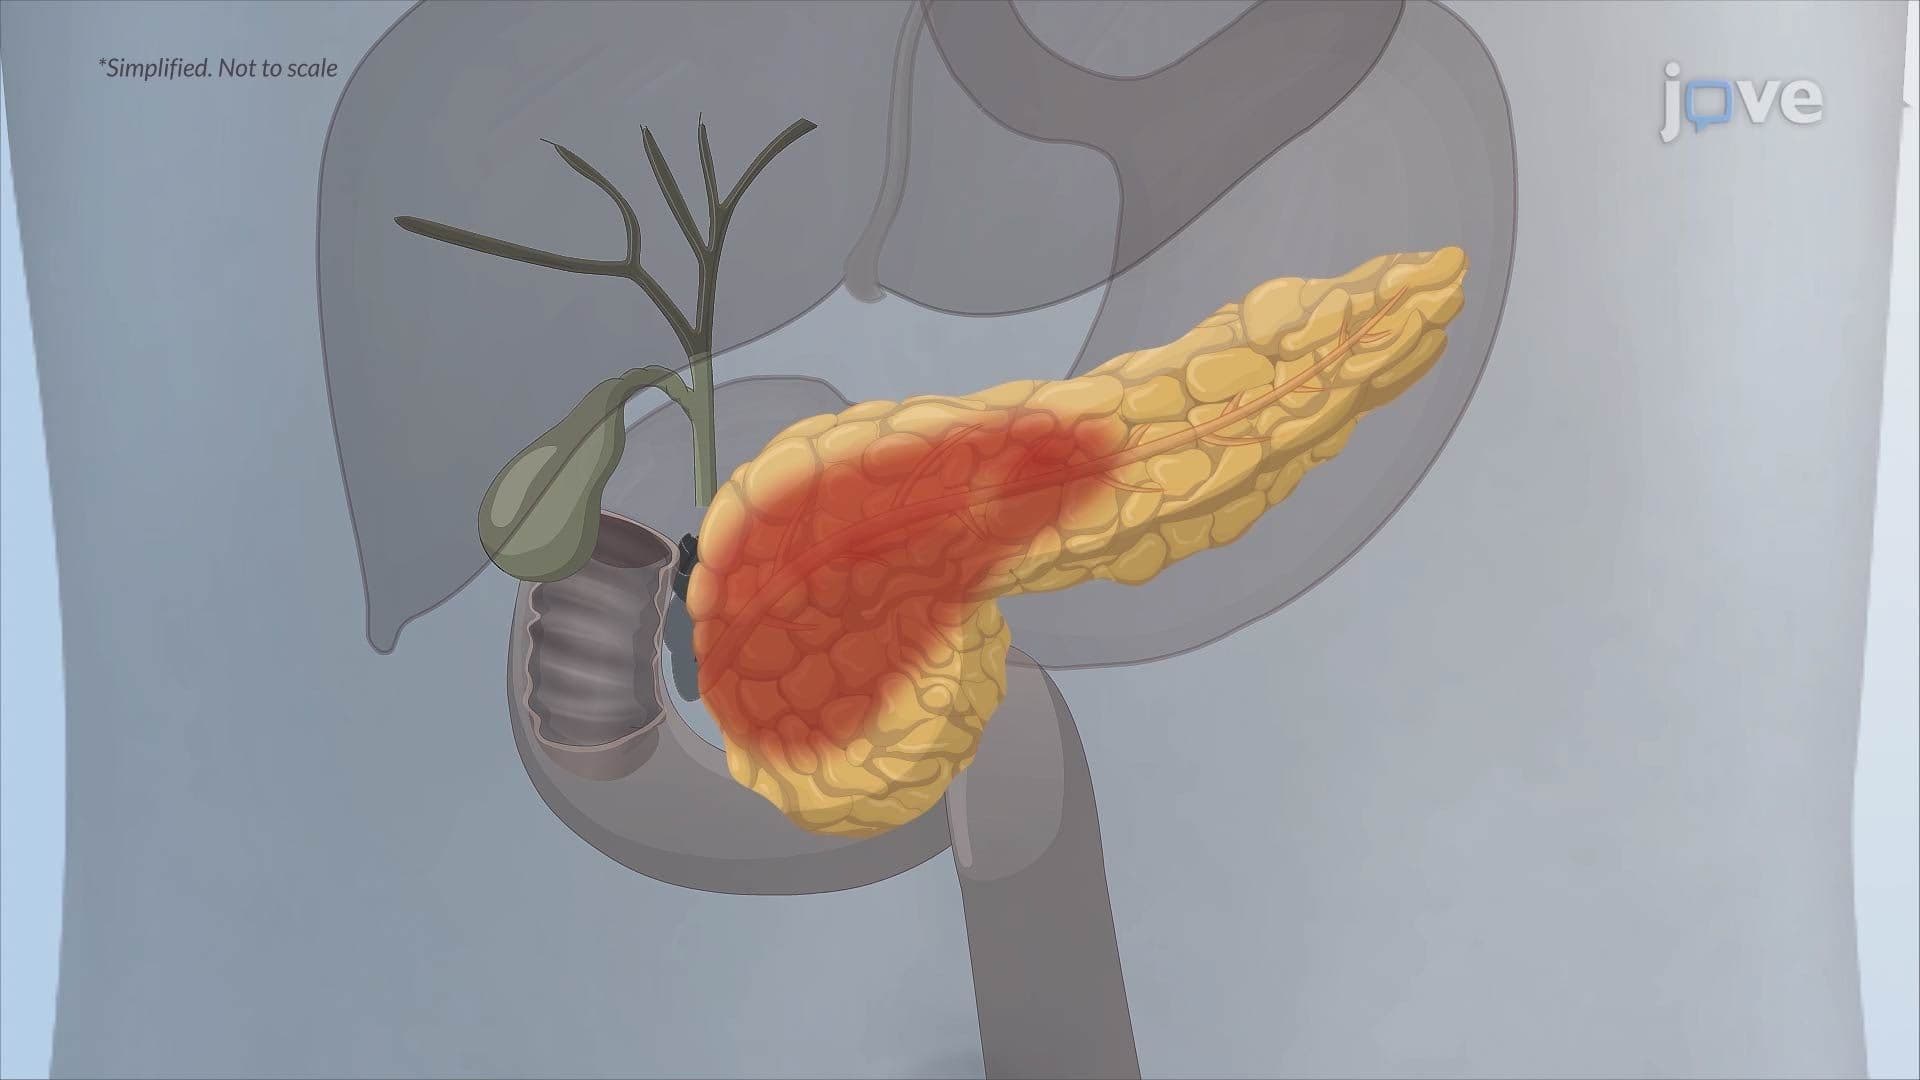
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:21
Acute Pancreatitis II: Pathophysiology
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:26
Type I Diabetes II: Pathophysiology
 01:22
Diabetic Ketoacidosis ll: Pathophysiology