Related Experiment Video
Updated: Aug 12, 2026
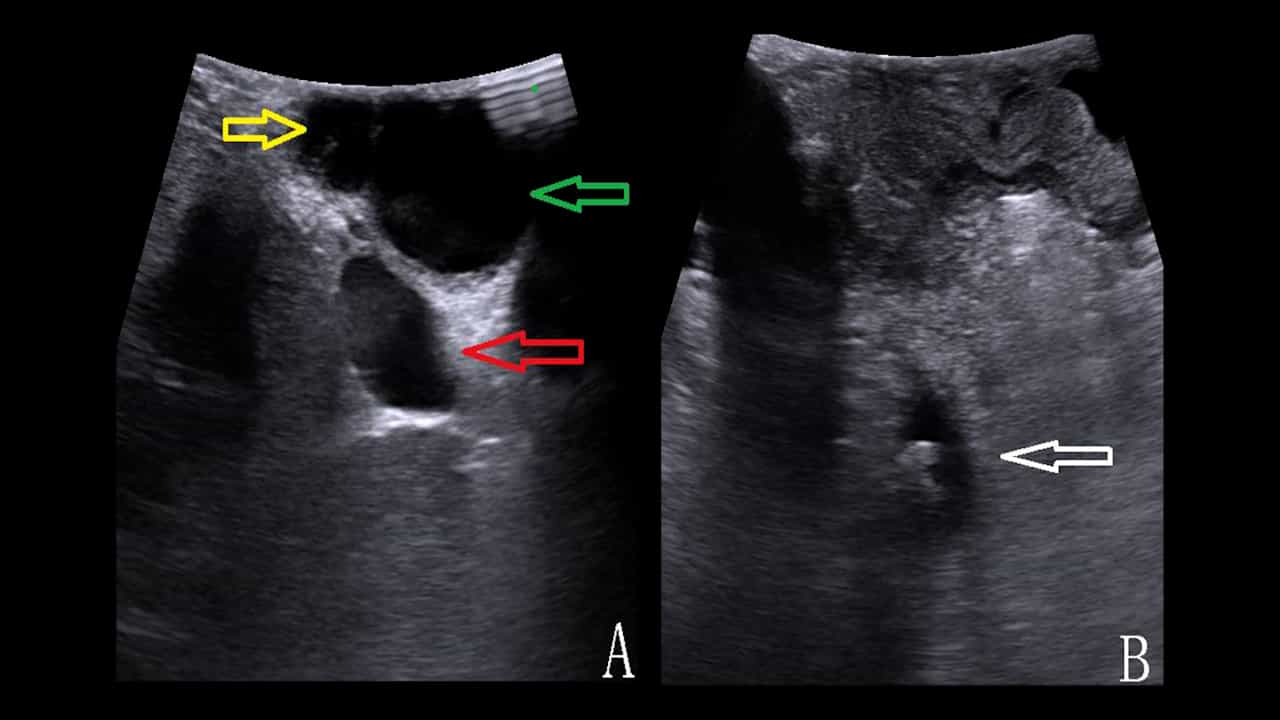

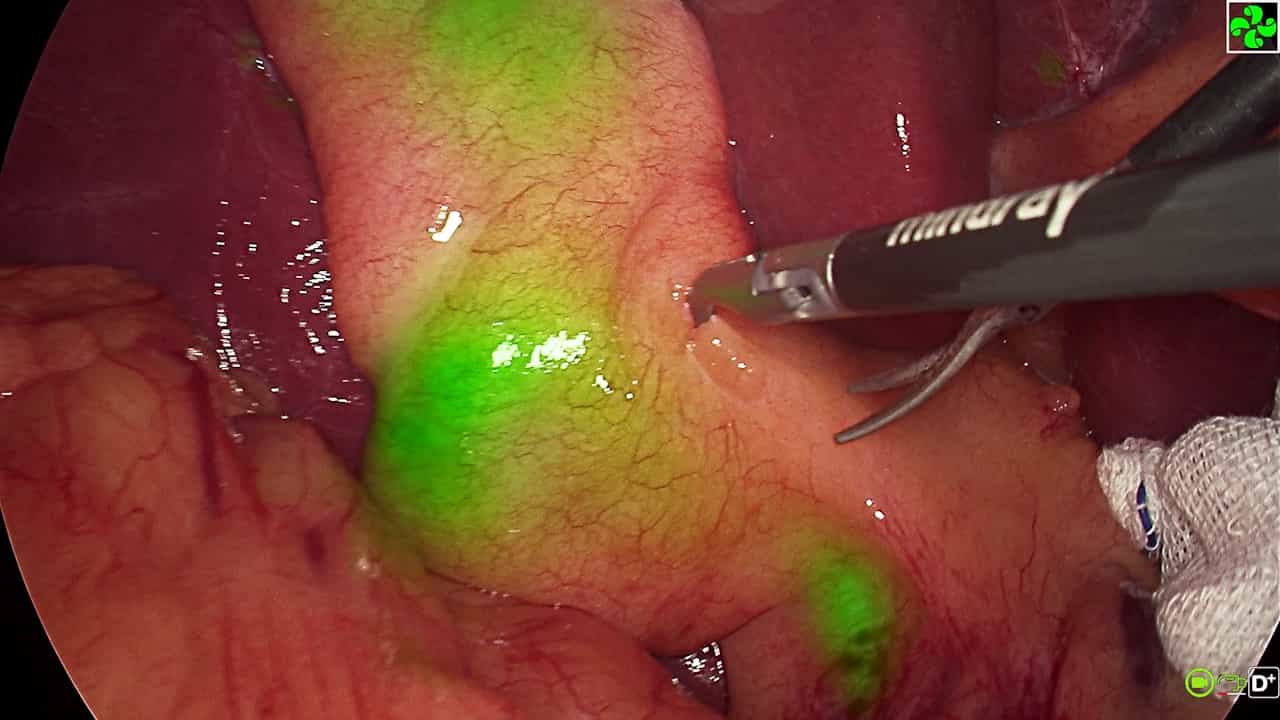
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Laparoscopic Versus Open Cholecystectomy in Older Adults: A Systematic Review and Meta-Analysis of Postoperative
Ahmed Mahmoud I Hassan1, Bassam Omar M Abobakr1, Abdulkareem Saad Alshamrani2
1College of Medicine, Ibn Sina National College for Medical Studies, Jeddah, SAU.

Abstract:
Laparoscopic cholecystectomy (LC) has supplanted open cholecystectomy (OC) as the gold standard for gallbladder disease, but its adoption in older adults has remained inconsistent due to concerns about physiological reserve and operative risk. This review directly compares postoperative outcomes of LC versus OC exclusively within older adults (≥65 years). A systematic review and meta-analysis was conducted per the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 guidelines. Five databases (PubMed/MEDLINE, Embase, Cochrane Central Register of Controlled Trials (CENTRAL), Scopus, and Web of Science Core Collection) were searched in January-February 2026 for comparative studies of LC versus OC in older adults published January 2000-February 2026. Risk of bias was assessed using the Newcastle-Ottawa Scale (NOS). Quantitative pooling of postoperative mortality was planned using a random-effects (DerSimonian-Laird) model where at least three studies reported adjusted, comparably defined estimates. Ten studies met the inclusion criteria, comprising 54,983 older adults (range: 94-47,500 per study). Two additional studies initially considered eligible were excluded after full-text review confirmed they lacked an extractable older adult-specific comparative subgroup. Of the 10 included studies, only two reported mortality estimates adjusted for confounding by indication; this fell short of the pre-specified three-study threshold for confirmatory quantitative pooling. Both adjusted estimates independently favored LC: the first study reported an adjusted OR for open surgery (relative to LC) of 5.4 (95% CI: 2.09-13.91), equivalent to an OR of 0.19 (95% CI: 0.07-0.48) for LC relative to OC, while the second study reported an adjusted OR of 0.16 (95% CI: 0.10-0.25) for LC relative to OC. As a post-hoc exploratory analysis, explicitly falling short of the pre-specified threshold and reported as a sensitivity check rather than a confirmatory result, random-effects pooling of these two adjusted estimates yielded an OR of 0.164 (95% CI: 0.109-0.249; p<0.0001) with no detectable heterogeneity (I²=0%). Unadjusted mortality counts reported in other studies (0.05% LC vs 1.55% OC, pre-matching) were not pooled with these adjusted estimates or with each other, given the high risk of confounding by indication inherent to crude comparisons in this literature. LC was also associated with shorter hospital stay, fewer postoperative complications, and lower readmission across the narratively synthesized outcomes. LC is associated with favorable postoperative outcomes compared with OC in older adults, including in octogenarian and nonagenarian subgroups, though the evidence base remains predominantly observational, quantitative pooling of mortality was not possible with the available data, and findings are subject to confounding by indication.