Related Experiment Video
Updated: Aug 12, 2026
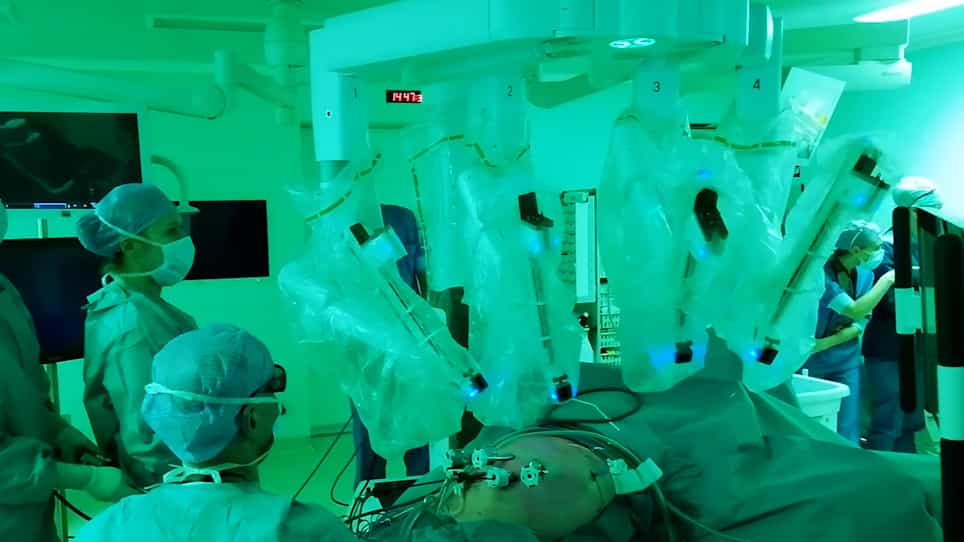

Robotic Pancreatoduodenectomy for Pancreatic Head Cancer: a Case Report of a Standardized Technique
Published on: June 24, 2022
Circumferential lymphadenectomy around the SMA in pancreatic head cancer: A single-center experience
Pengfei Wu1, Kai Zhang1, Xumin Huang1
1Pancreas Center, the First Affiliated Hospital of Nanjing Medical University, Jiangsu Province Hospital, Pancreas Institute of Nanjing Medical University, Nanjing 210029, China.

Background:
Complete circumferential lymphadenectomy (CCL) around the superior mesenteric artery (SMA) is not routinely performed during pancreaticoduodenectomy (PD) for patients with pancreatic head cancer, and its clinical value remains unclear.
Objective:
To investigate the positive rate of left side lymph nodes along the SMA (14cd-LNs), identify the associated risk factors and clinical outcomes, and evaluate the feasibility and potential clinical benefit of CCL in patients with pancreatic head cancer.
Methods:
Patients who underwent PD for pancreatic head cancer at the Pancreatic Center of the First Affiliated Hospital of Nanjing Medical University (Jiangsu Province Hospital) between January 2020 and March 2023 were prospectively collected and retrospectively reviewed. Baseline characteristics, pathological findings, perioperative outcomes, and long-term oncological outcomes were evaluated. Univariate and multivariable logistic regression analyses were performed to identify risk factors. Statistical analyses were conducted using Stata 18.0.
Results:
A total of 260 patients were identified, 132 (50.77%) performed CCL. Compared with the non-CCL group, CCL prolonged the median operation time (287.5 min vs. 248.0 min, P < 0.001), and postoperative hospital stay (17.0d vs. 13.0d, P < 0.001), but did not increase the postoperative mortality and morbidity. In the CCL group, the positive rate of 14cd-LNs was 28.79% (38/132), and 14cd-LNs metastasis indicated poorer prognosis (14cd-LNs negative vs. 14cd-LNs positive, median disease-free survival: 23.2 months vs. 11.5 months, P = 0.003; median overall survival: NR vs. 20.6 months, P = 0.003). Uncinate invasion-positive (OR=2.88, 95%CI: 1.07 to 7.76, P = 0.036), and tumor size≥4 cm (OR=4.27, 95%CI: 1.63-11.21, P = 0.003) were independent risk factors of 14cd-LNs metastasis. CCL significantly reduced postoperative 9-month local recurrence compared to non-CCL (25.00% vs 10.91%, P = 0.008), and emerged as an independent influencing factor of 9-month local recurrence (OR=0.31, 95%CI: 0.12-0.78, P = 0.013), but failed to provide survival benefits, neither disease-free survival (18.4 vs. 13.7 m, P = 0.280) nor overall survival (25.5 vs. 28.1 m, P = 0.930) across the whole cohort. For patients with low-risk 14cd-LNs metastasis (uncinate invasion-negative and tumor size <4.0 cm), CCL improved their disease-free survival (27.2 vs.12.8 m, P = 0.019) and overall survival (NR vs. 31.7 m, P = 0.062).
Conclusions:
14cd-LNs metastasis occurs at a considerable frequency in patients with pancreatic head cancer and is associated with poor prognosis. CCL provides improved locoregional control and may confer survival benefit in patients with low-risk 14cd-LNs metastasis.