Related Experiment Video
Updated: Aug 12, 2026
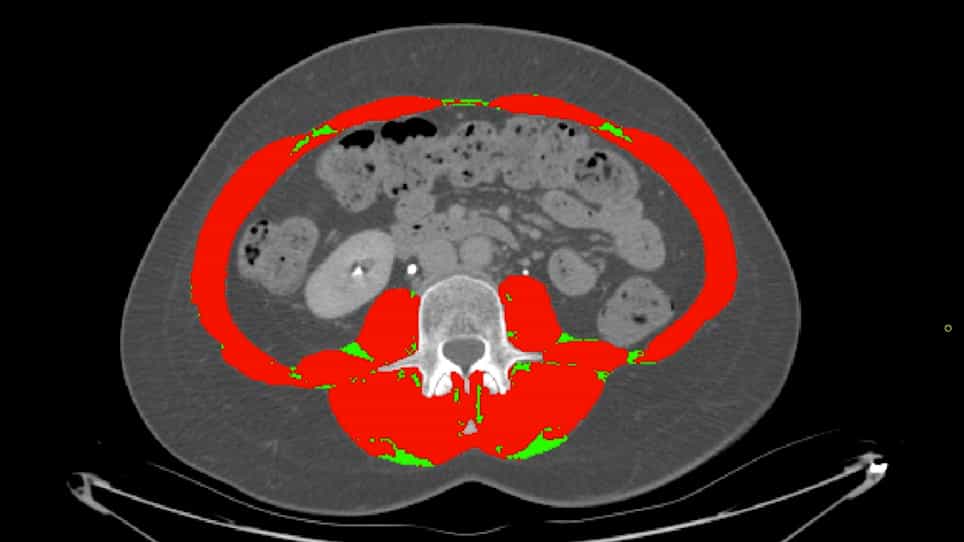

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Frailty and sarcopenia proxies are associated with postoperative outcomes after abdominal wall reconstruction: a
Ruben D Salas-Parra1, Bryan Vintimilla2, Katerina Jou3
1Division of General Surgery, Northwell Health, New York, NY, USA. Rdsp.med@gmail.com.

Background:
Abdominal wall reconstruction (AWR) carries significant postoperative morbidity, including surgical site infection, wound dehiscence, and readmission. Frailty and sarcopenia have emerged as critical predictors of surgical outcomes; however, their role in AWR is not well defined. We aimed to evaluate the independent and combined predictive value of frailty and sarcopenia proxies on morbidity and mortality after AWR.
Methods:
A retrospective analysis using the American College of Surgeons National Surgical Quality Improvement Program (ACS-NSQIP) database was conducted from 2015 to 2020. Frailty was assessed using the Modified Frailty Index (mFI-5), and sarcopenia proxies were defined by ≥ 1 validated proxy markers (BMI < 20, > 10% weight loss/malnutrition, hypoalbuminemia, hematocrit < 30%). Propensity score matching (PSM) was performed to create balanced cohorts, and conditional logistic regression on matched pairs was used to evaluate associations between frailty, sarcopenia proxies, and postoperative outcomes. Primary outcomes were 30-day morbidity and mortality.
Results:
15,466 adult patients undergoing elective AWR were included. Frailty and sarcopenia proxies were present in 19.4% and 11.3% of patients, respectively. After propensity score matching, frailty was associated with increased odds of overall morbidity (OR 1.16, 95% CI 1.01-1.32; p = 0.035), major complications (OR 1.27, 95% CI 1.07-1.52; p = 0.008), and discharge to a non-home facility (OR 1.40, 95% CI 1.09-1.80; p = 0.008). Sarcopenia proxies demonstrated similar associations. The combined frailty and sarcopenia-proxy phenotype (dual-impairment) conferred the highest odds of morbidity, major complications, and discharge to a non-home facility. Thirty-day mortality and operative time did not differ significantly between groups after matching.
Conclusion:
Frailty and sarcopenia proxies are prevalent among patients undergoing elective AWR and are independently associated with increased postoperative morbidity, with their coexistence (dual-impairment) conferring the greatest risk. Incorporating these factors into risk calculators may improve patient selection, nutritional optimization, and prehabilitation strategies in complex hernia repair.