

Complete traumatic transection of the fourth portion of the duodenum after blunt abdominal trauma: a case report
Ghazi Lâamiri1,2, Hazem Alouani1, Manel Yakoubi1,2,3
1Department of general surgery, Mohamed Taher Maamouri University hospital, Nabeul, Tunisia.

Introduction And Importance:
Traumatic injuries to the fourth portion of the duodenum (D4) are exceptionally rare owing to its retroperitoneal location and protection by the ligament of Treitz. Their subtle clinical presentation and limited visibility on imaging frequently result in delayed diagnosis and increased morbidity. Complete transection of D4, associated with proximal jejunal injury after blunt abdominal trauma, is particularly uncommon and represents a diagnostic and therapeutic challenge.
Case Presentation:
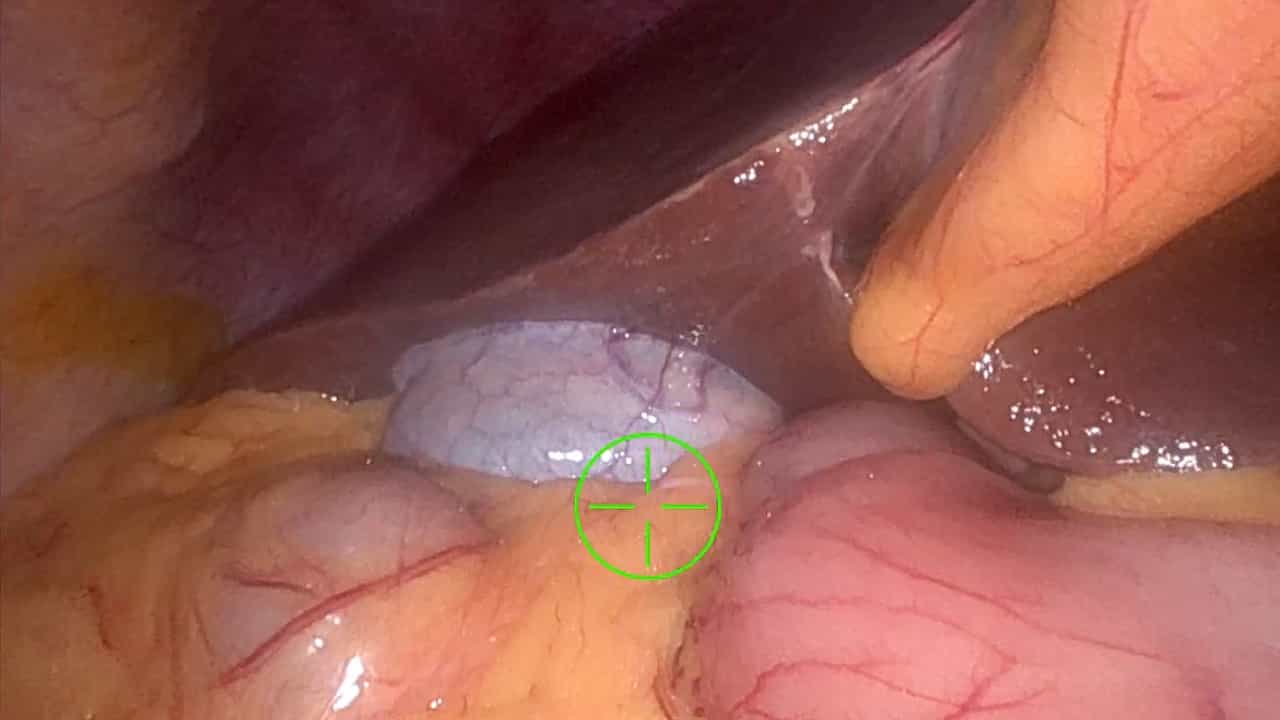
We report the case of a 40-year-old woman who sustained blunt abdominal trauma following a road traffic accident. She was hemodynamically stable, with mild epigastric tenderness and no external injury marks. A contrast-enhanced CT scan revealed moderate hemoperitoneum, a liver contusion, subtle supramesocolic pneumoperitoneum, mesenteric root infiltration, and an associated left renal artery dissection with renal devascularization. However, duodenal discontinuity was not clearly identified. Given the presence of indirect signs suggestive of hollow viscus injury, including mesenteric root infiltration and supramesocolic pneumoperitoneum, early surgical exploration was considered mandatory. Given the presence of indirect radiologic signs suggestive of intestinal injury, including mesenteric root infiltration and pneumoperitoneum, exploratory laparotomy was undertaken. Surgical exploration revealed a complete circumferential transection of the fourth portion of the duodenum, extending to the first jejunal loop. After debridement of devitalized tissue margins, a manual latero-terminal duodenojejunal anastomosis was performed with wide drainage. The postoperative course was favorable.
Clinical Discussion:
D4 injuries account for less than 1% of duodenal trauma. Their retroperitoneal location often masks clinical signs, and CT sensitivity remains limited. According to the American Association for the Surgery of Trauma (AAST) classification, this lesion corresponds to a Grade III duodenal injury characterized by complete transection without pancreatic involvement. When pancreatic and ampullary structures are intact, primary duodenojejunal anastomosis represents a safe and effective reconstructive option.
Conclusion:
High clinical suspicion is required when imaging demonstrates mesenteric root infiltration or subtle pneumoperitoneum following blunt abdominal trauma. Early surgical exploration and prompt reconstruction are essential to achieve favorable outcomes.
Related Concept Videos
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology