Related Experiment Video
Updated: Aug 14, 2026
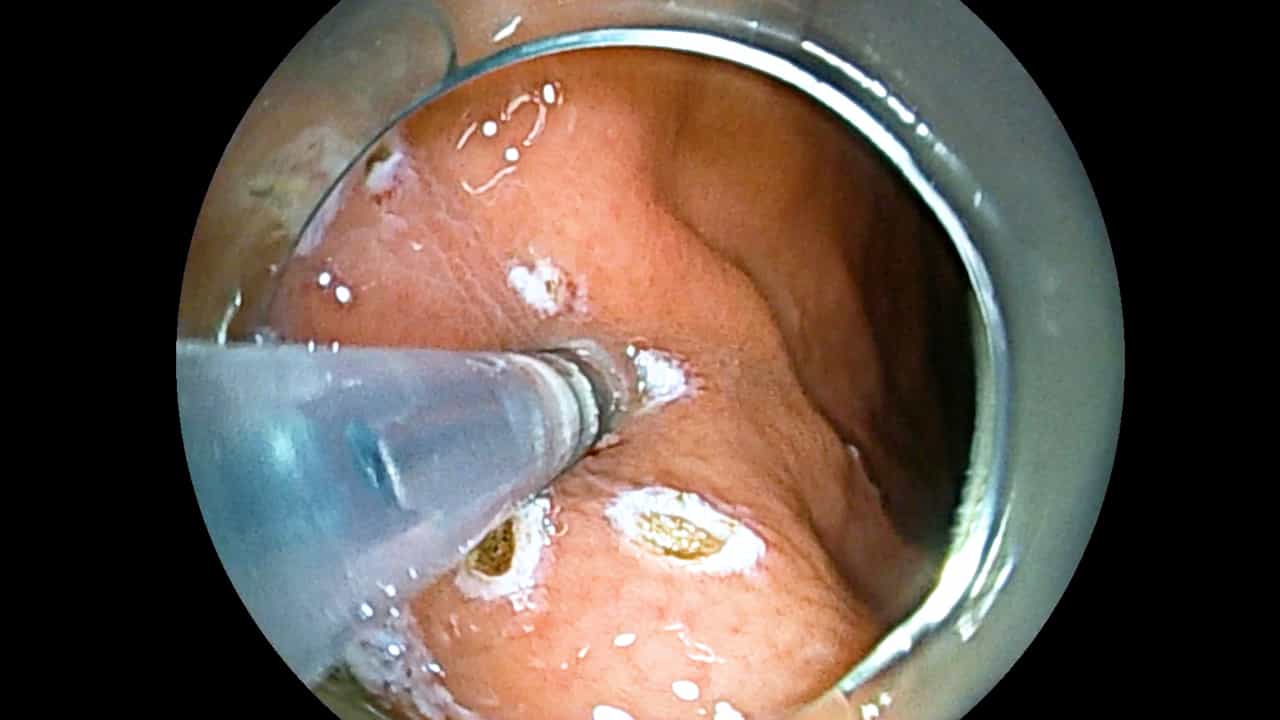

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Endoscopic Hand Suturing After Gastric Endoscopic Submucosal Dissection in Patients with Low to Intermediate Risk of
Zofia Orzeszko1, Przemysław Kasprzyk2, Urszula Zawada2
1Department of Surgery, Faculty of Health Sciences, Jagiellonian University, Trynitarska 11 Street, 31-061, Krakow, Poland. zofia.orzeszko@uj.edu.pl.

Purpose:
Endoscopic hand suturing (EHS) enables closure of large mucosal defects after gastric endoscopic submucosal dissection (ESD), but evidence on its prophylactic use in patients at low to intermediate risk of delayed bleeding (DB) is limited. This pilot study evaluated the feasibility of EHS following gastric ESD in a Wester setting.
Methods:
This retrospective pilot study included 46 consecutive patients with low to intermediate DB risk (BEST-J score 0-2) who underwent uneventful gastric ESD between September 2023 and December 2024. Post-ESD defects were closed using EHS (group A, n = 20) or left open (group B, n = 26). Primary outcomes were technical success of closure and DB rate. Secondary outcomes included overall procedure time (OPT), perforation rate, and length of hospital stay (HS).
Results:
En bloc resection and complete closure were successful in 100% of attempted cases. DB in group A was 0.0% (0/20) versus 7.7% (2/26) in group B (mean difference [MD] 7.7%; 95%CI: - 3.3 to 18.7). OPT was longer in the EHS group (59 ± 19 vs. 35 ± 17 min; MD 23 min; 95%CI: 12-34). No delayed perforations occurred. HS was shorter in group A (2.1 ± 1.0 vs. 2.9 ± 1.1 days; MD 0.8 days; 95%CI: 0.2-1.4).
Conclusion:
In a Western setting, EHS after gastric ESD is feasible and enables reliable defect closure. However, implementation of EHS is associated with increased procedure time and cost, and its clinical benefit in low- to intermediate-risk patients remains uncertain.
Clinicaltrials:
gov Identifier: NCT06779266 retrospectively registered.