Related Experiment Video
Updated: Aug 14, 2026

Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Effectiveness and Safety of the Minimally Invasive Lumbar Decompression (MILD) Procedure for Adults with Lumbar
Rebecca Cox1, Lucky Patel2, Kenan Sarlioglu3
1Georgetown/MedStar National Rehabilitation Hospital, Washington, DC, USA.

Objective:
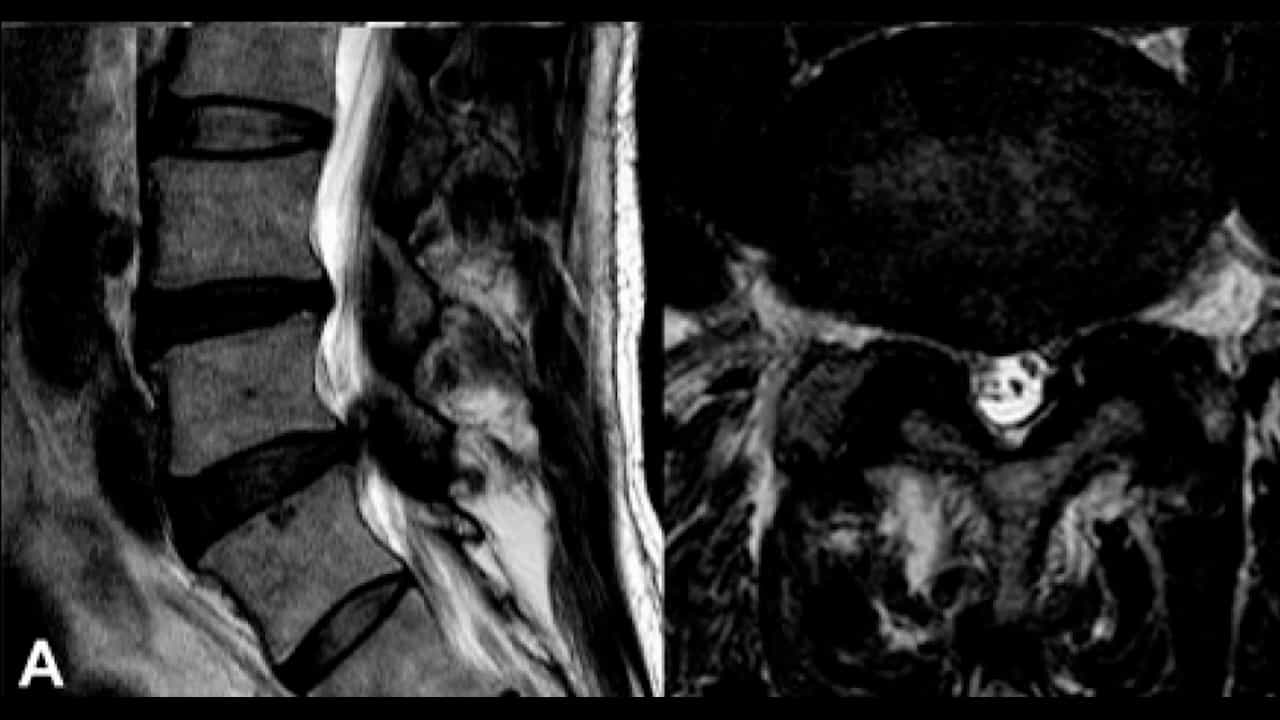
Lumbar spinal stenosis (LSS) is a common and disabling condition in older adults, and current treatment options leave a therapeutic gap between conservative management and open surgical decompression. Minimally invasive lumbar decompression (MILD) is a percutaneous, image-guided procedure that targets the hypertrophic ligamentum flavum as a primary driver of central canal narrowing. This systematic review evaluates the effectiveness and safety of MILD for the treatment of LSS.
Methods:
A systematic search of MEDLINE, Embase, Cochrane CENTRAL, and Web of Science was conducted for studies published between January 2016 and the first quarter of 2026. Studies were included if they enrolled adults with LSS who underwent the MILD procedure and reported validated clinical outcomes, such as the Visual Analog Scale, Numeric Rating Scale, Oswestry Disability Index, or Zurich Claudication Questionnaire. Sixteen publications representing 11 unique studies, including two randomized controlled trials and nine observational studies, met the inclusion criteria. Study quality was assessed using the Newcastle Ottawa Scale.
Results:
Across the included studies, MILD was associated with consistent improvements in pain and disability compared with baseline and comparator treatments. In the MiDAS ENCORE trial, MILD produced significantly greater reductions in pain and disability than epidural steroid injections at 6 months. The MOTION trial demonstrated sustained improvements in pain, disability, and walking tolerance through three years compared with conventional medical management. Observational studies supported these findings and reported low rates of subsequent surgical intervention, generally at or under 12% within five years. Safety outcomes were favorable overall, with low rates of device-related complications. However, one propensity-matched comparison found a higher rate of postoperative neurologic symptoms following MILD relative to open decompression.
Conclusion:
MILD is an effective and generally safe treatment option for appropriately selected patients with LSS and neurogenic claudication driven by ligamentum flavum hypertrophy. Patient selection based on classic claudication symptoms, imaging confirmed hypertrophy, and failure of conservative therapy appears critical to optimizing outcomes. Further research is needed to clarify long-term comparative effectiveness relative to surgical alternatives and to standardize outcome reporting across studies.