Related Experiment Video
Updated: Aug 14, 2026
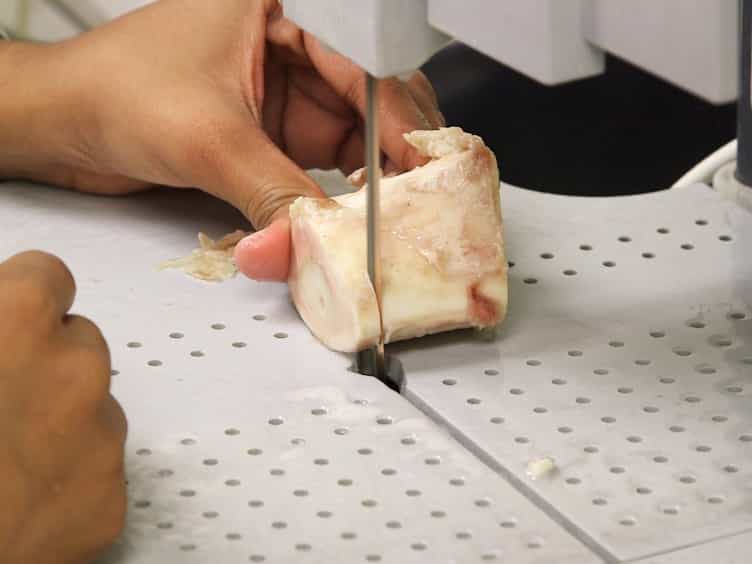

Fragility Assessment of Bovine Cortical Bone Using Scratch Tests
Published on: November 30, 2017
Bone organic matrix quality indices associate with fragility fracture occurrence independently of bone mineral
Eleftherios P Paschalis1, Sonja Gamsjaeger2, Norbert Hassler2
1Ludwig Boltzmann Institute for Osteology, Hanusch Kh, Heinrich Collin Str. 30, Vienna, 1140, Austria. lpaschalis@gmx.net.

Abstract:
Bone mineral density measures are not the sole determinant whether a patient suffers fragility fractures. We tested the hypothesis that changes in bone organic matrix quality indices strongly associate with Fx occurrence. Fx-suffering patients have altered quantitative and qualitative organic matrix attributes, offering new insights into the pathogenesis of Fx. Fragility fractures present a considerable socioeconomic burden. We tested the hypothesis that organic matrix attributes associate with fragility fracture occurrence independent of BMD. We used Raman microspectroscopy to analyze iliac crest biopsies from age- and BMD-matched postmenopausal women that either sustained (n = 60) fragility fractures or not (n = 60) in the cortical and cancellous compartments at specific tissue ages. The measured indices were mineral/matrix, mineral crystallinity, nanoporosity, glycosaminoglycan, and pyridinoline contents. Tissue-age unadjusted data were compared by 2-way ANOVA with anatomical compartment and fracture incidence as the two factors, while tissue-age-adjusted data by 2-way ANOVA with tissue age and patient group as the two factors. Tissue-age-unadjusted data indicated differences between anatomical compartments but no differences between the two patient groups. Tissue-age-adjusted data showed that the fracture-sustaining patients had higher mineral/matrix values in both compartments (in cortical, this was due to lower organic matrix content). At forming cortical surfaces, they had higher nanoporosity and lower pyridinoline content. They also had higher glycosaminoglycan content in the interstitial bone of the cancellous compartment. The results indicate that fracture-suffering patients have altered quantitative and qualitative organic matrix attributes. The elevated mineral/matrix in fracture-suffering patients may imply stiffer, thus of decreased toughness, bone, while the decreased pyridinoline content at cortical actively forming surfaces would decrease collagen fiber stiffness. The data of the present study offer new insight into the pathogenesis of fragility fractures.
Introduction:
Fragility fractures present a considerable socioeconomic burden. We tested the hypothesis that organic matrix attributes associate with fragility fracture occurrence independent of BMD.
Methods:
We used Raman microspectroscopy to analyze iliac crest biopsies from age- and BMD-matched postmenopausal women that either sustained (n=60) fragility fractures or not (n=60) in the cortical and cancellous compartments at specific tissue ages. The measured indices were mineral/matrix, mineral crystallinity, nanoporosity, and glycosaminoglycan, and pyridinoline contents. Tissue-age unadjusted data were compared by 2way ANOVA with anatomical compartment and fracture incidence as the two factors, while tissue-age adjusted data by 2way ANOVA with tissue age and patient group as the two factors.
Results:
Tissue-age-unadjusted data indicated differences between anatomical compartments but no differences between the two patient groups. Tissue-age-adjusted data showed that the fracture-sustaining patients had higher mineral / matrix values in both compartments (in cortical, this was due to lower organic matrix content). At forming cortical surfaces, they had higher nanoporosity and lower pyridinoline content. They also had higher glycosaminoglycan content in the interstitial bone of the cancellous compartment.
Conclusions:
The results indicate that fracture-suffering patients have altered quantitative and qualitative organic matrix attributes. The elevated mineral / matrix in fracture-suffering patients may imply stiffer, thus of decreased toughness, bone, while the decreased pyridinoline content at cortical actively forming surfaces would decrease collagen fiber stiffness.


Related Concept Videos
 01:18
The Bone Matrix
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into...
 01:40
Bone Remodeling