Related Experiment Video
Updated: Aug 14, 2026

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Single-Position Minimally Invasive Retropleural Asymmetric Vertebral Column Resection and Percutaneous Pedicle Screw
Piotr Kowalski1, Gergely Bodon2, Michael A Galgano3
1Department of Neurosurgery, Regional Specialized Hospital, ul. Dekerta 1, 66-400 Gorzow, Poland.

Abstract:
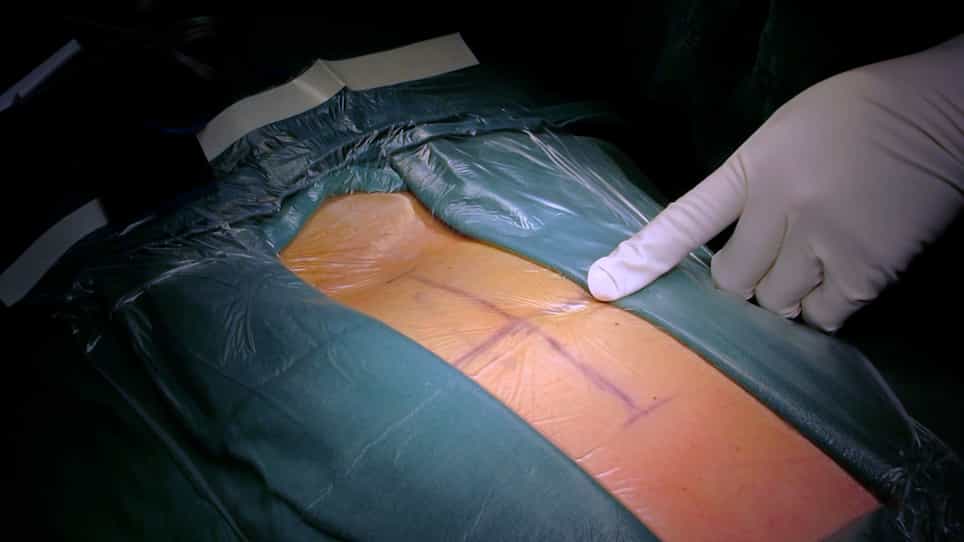
Background: Congenital thoracic kyphoscoliosis caused by vertebral malformations is a challenging condition that may progress during skeletal growth, leading to spinal imbalance, pain, cosmetic deformity, and neurological compromise. Conventional correction often requires extensive anterior, posterior, or combined approaches associated with substantial surgical morbidity. We describe a single-position surgical technique combining a lateral retropleural asymmetric vertebral resection with percutaneous posterior instrumentation performed entirely in the lateral decubitus position. Methods: A 15-year-old boy with progressive congenital thoracic kyphoscoliosis secondary to a T10 butterfly vertebra underwent surgical correction after failure of conservative treatment. The procedure was performed entirely in the left lateral decubitus position under multimodal intraoperative neurophysiological monitoring. Bilateral percutaneous pedicle screws were inserted from T7 to L1 under fluoroscopic guidance without repositioning the patient. A muscle-sparing lateral retropleural approach was then used to perform T10 asymmetric vertebral column resection, anterior column reconstruction with an expandable cage, and definitive deformity correction using posterior rod compression. The technical rationale, operative workflow, and reconstruction strategy are described. Results: The procedure was completed without intraoperative neurological deterioration or the need for patient repositioning. Postoperative imaging demonstrated satisfactory restoration of coronal and sagittal alignment, appropriate implant positioning, and spinal canal decompression. The patient experienced marked improvement in pain, shoulder balance, rib hump deformity, and overall posture while maintaining normal neurological function. The main thoracic curve improved from 32° to 6°, thoracic kyphosis from 78° to 63°, VAS from 5 to 0, ODI from 42 to 5, and SRS-22R from 3.85 to 4.85. Solid fusion was confirmed at 3 years. A postoperative pneumothorax, attributed to pleural violation during exposure, represented the only complication and resolved completely following pleural drainage. At 36-month follow-up, radiographs and computed tomography confirmed maintenance of deformity correction, stable instrumentation, and solid anterior and posterior fusion without implant failure or loss of correction. Conclusions: Single-position lateral retropleural asymmetric vertebral resection combined with percutaneous pedicle screw fixation is a technically feasible option for selected patients with congenital thoracic kyphoscoliosis. Avoiding intraoperative repositioning while combining anterior reconstruction and posterior stabilization through a reduced-access retropleural approach may simplify the surgical workflow and minimize soft-tissue disruption without compromising deformity correction. Further clinical experience is required to establish its reproducibility and comparative advantages.