Related Experiment Video
Updated: Aug 14, 2026
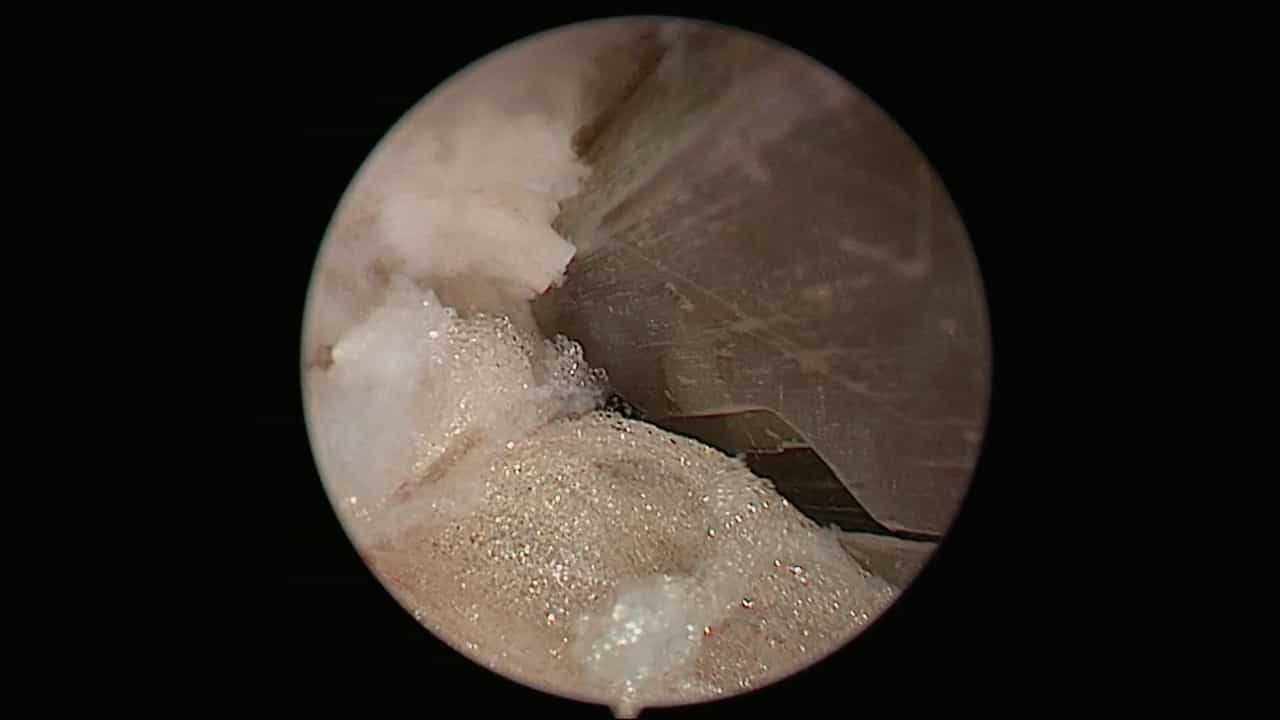

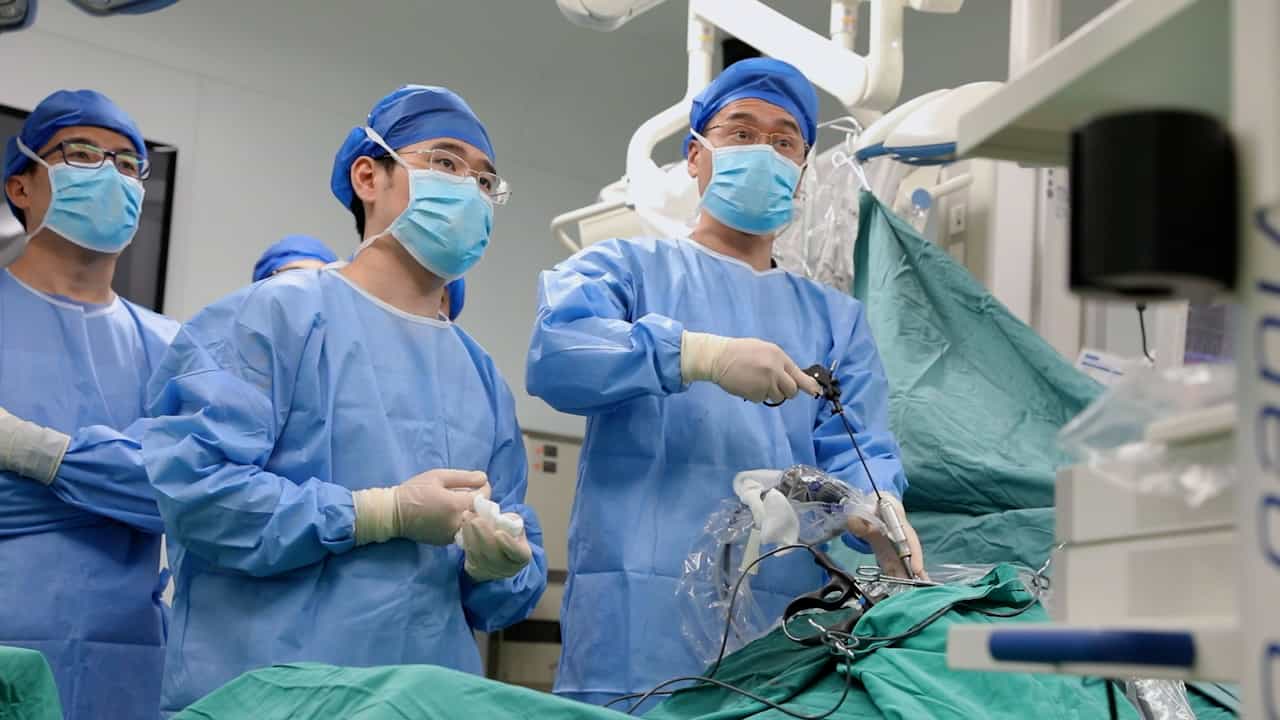
The Third Channel-Assisted Unilateral Biportal Endoscopic Technique for Lumbar Spinal Stenosis Combined with Contralateral Disc Herniation
Published on: November 17, 2023
Comparative efficacy of unilateral biportal endoscopy versus endoscopic foraminoplasty decompression for single-level
Xu Qiao1, Cao Rui1, Aikebaierjiang Aisaiti1
1Spinal Surgery, The First Affiliated Hospital of Xinjiang Medical University, Urumqi, Xinjiang Uygur Autonomous Region, China.

Objective:
To compare perioperative, functional, and radiological outcomes of unilateral biportal endoscopic (UBE) decompression versus endoscopic foraminoplasty decompression (EFD) in patients with single-level lumbar spinal stenosis (LSS) using a retrospective observational design.
Methods:
A total of 208 patients with single-level LSS were screened; 161 were enrolled (UBE: n = 78; EFD: n = 83). Perioperative data, VAS (leg pain) score, ODI, JOA scores, and radiological parameters (disc height, foraminal area, spinal canal volume) were assessed over 12 months. Multivariable regression and repeated-measures ANCOVA were used for adjusted comparisons.
Results:
Baseline characteristics were comparable between groups (all P > 0.05). UBE had shorter operation time (93.85 vs. 110.42 min, P < 0.001) and hospital stay (7.09 vs. 8.71 days, P < 0.001), but greater blood loss (143.21 vs. 97.53 mL, P < 0.001). Both groups improved significantly in all functional scores (P < 0.05). UBE showed faster early recovery at 3-6 months, but differences were non-significant at 12 months. Radiological decompression was more extensive with UBE (P < 0.05 for foraminal area and canal volume). Excellent-to-good rates were 66.67% vs. 59.04% (P = 0.319). On adjusted analysis, surgical technique was not an independent predictor of favorable outcome (OR = 1.42, 95% CI: 0.71-2.84, P = 0.322).
Conclusion:
This retrospective comparative observational study suggests that both UBE and EFD are safe and effective minimally invasive options for single-level LSS, with acceptable complication profiles. UBE is associated with shorter operation time and hospital stay but greater blood loss, whereas EFD offers reduced bleeding. Although UBE provides more extensive radiological decompression, functional outcomes at 12 months are comparable between the two techniques. The choice of procedure should be individualized based on stenosis morphology, patient comorbidities, and surgeon expertise. Given the non-randomized design, these findings should be interpreted as hypothesis-generating and require confirmation in prospective randomized trials.