Related Experiment Video
Updated: Aug 14, 2026
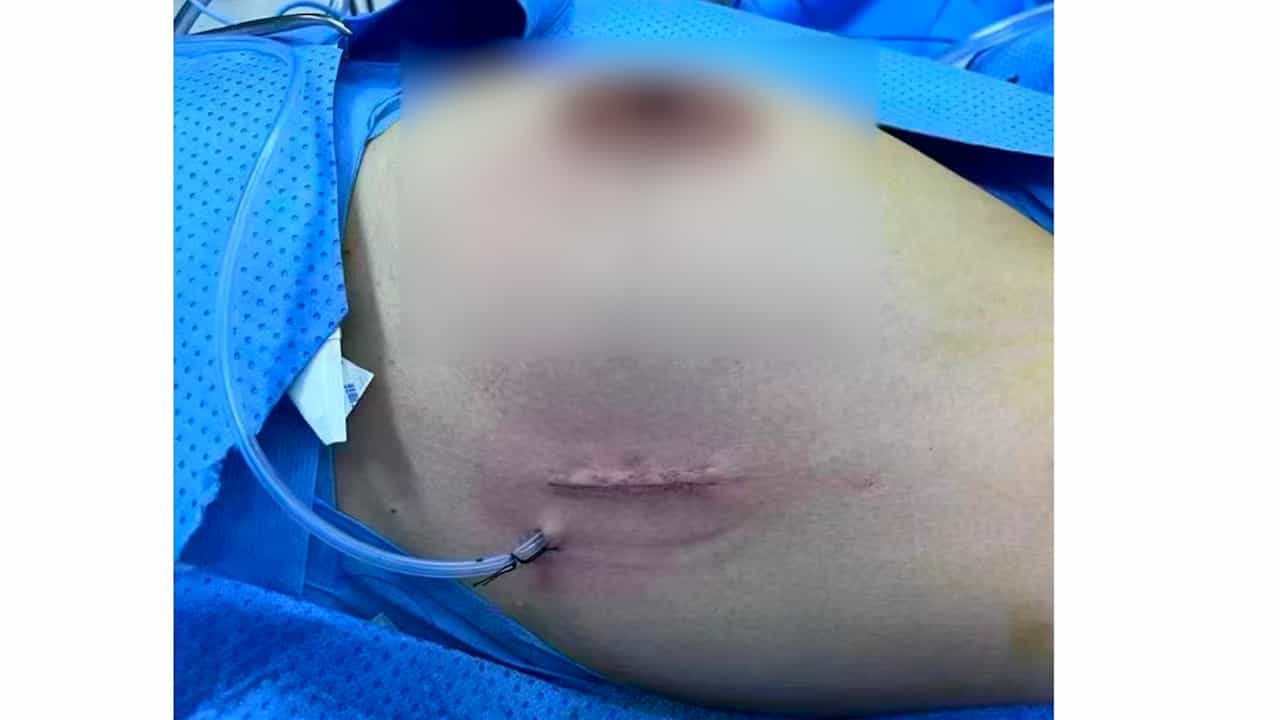
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Axillary surgical de-escalation after neoadjuvant therapy in breast cancer: current evidence, clinical controversies,
Jinxiu Ma1, Gang Zhao1, Jian Sun1
1Department of Breast Surgery, General Surgery Center, The First Hospital of Jilin University, Changchun, Jilin, China.

Abstract:
Neoadjuvant therapy (NAT) has expanded opportunities to de-escalate axillary surgery in breast cancer, but the appropriate extent of surgery remains uncertain across pretreatment nodal stages and post-treatment responses. This focused narrative review synthesizes evidence from pivotal prospective trials and contemporary observational cohorts on the timing and technical optimization of sentinel lymph node biopsy (SLNB), stage-specific axillary management after NAT, the integration of regional nodal irradiation (RNI), the management of residual low-volume nodal disease, and the potential omission of axillary surgery. In patients with initial cN0 disease, post-NAT SLNB provides pathologic staging, and a negative result may allow axillary lymph node dissection (ALND) to be avoided. In patients with biopsy-proven cN1 disease who convert to ycN0, dual-tracer mapping, retrieval of at least three sentinel lymph nodes, and targeted removal of the previously positive marked node improve diagnostic accuracy and reduce the false-negative rate. However, these diagnostic performance data do not by themselves establish the long-term oncologic safety of omitting ALND. For patients presenting with cN2 disease, ALND remains the standard because prospective evidence supporting SLNB or targeted axillary dissection is limited, although selected patients with HER2-positive or triple-negative breast cancer who achieve an excellent pathologic response may be candidates for prospective de-escalation studies. The NSABP B-51/RTOG 1304 trial supports consideration of RNI omission in selected patients with initial cN1 disease who convert to ypN0, but it does not demonstrate that radiotherapy can replace ALND. In patients with residual isolated tumor cells or micrometastases, contemporary cohorts show substantial variation in the use of completion ALND and clinically relevant rates of additional nodal involvement, but randomized evidence remains lacking. Complete omission of axillary staging should remain investigational and restricted to carefully selected patients in prospective trials. Future studies should integrate initial nodal burden, residual disease volume, tumor subtype, systemic therapy, and radiotherapy while evaluating recurrence, survival, and treatment-related morbidity. The goal is not de-escalation alone, but identification of the least morbid strategy that preserves reliable staging and durable oncologic control.
More Related Videos
 03:07
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
 13:35
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024