Related Experiment Video
Updated: Aug 15, 2026
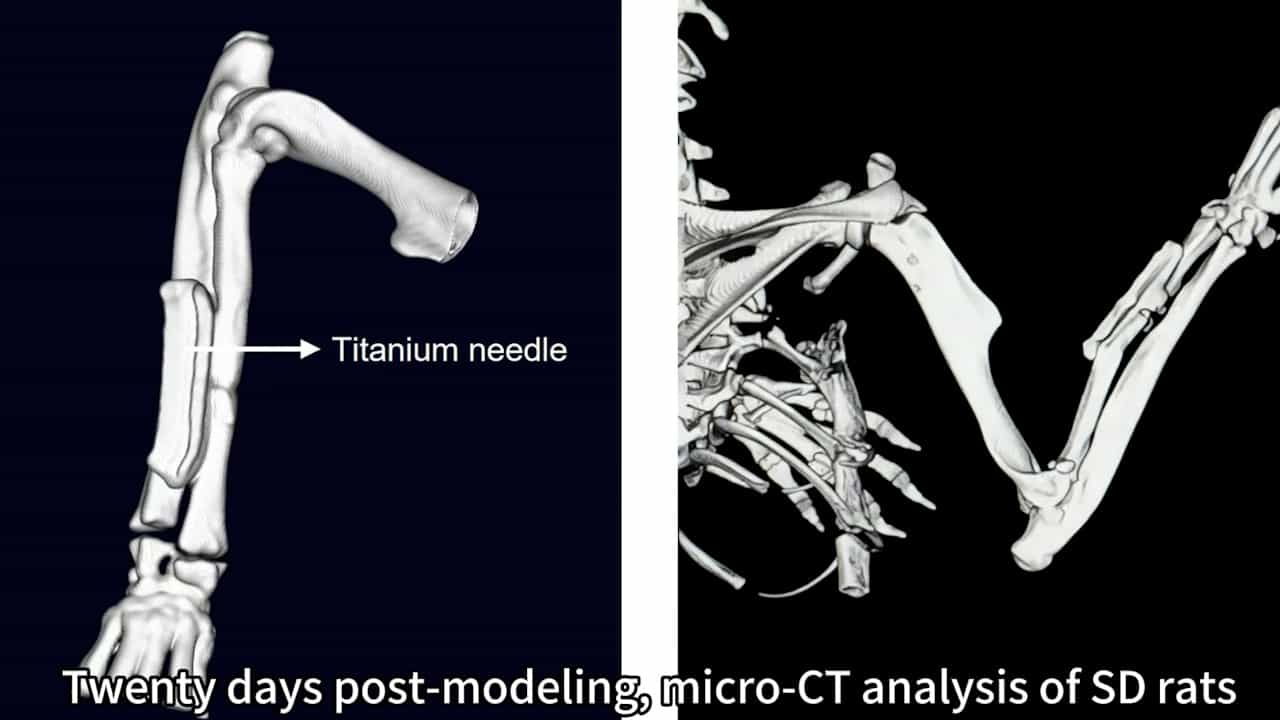

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Distal Radius Fracture Treated with a Modified Kocher-style Dorsolateral Approach, Distal Radius T-plate, and
Navendu Dilip Gadhia1, Abhijit More2, Abhishek Nair2
1Department of Orthopaedics, Dr. D. Y. Patil Medical College, Hospital and Research Centre, Pune, Maharashtra, India.

Abstract:
Distal radius fractures are common injuries and displaced or unstable patterns frequently require operative stabilization. Volar locking plating remains the predominant method for many unstable distal radius fractures; however, selected radial column or radial styloid-dominant patterns may be amenable to fragment-specific fixation. We report a displaced distal radius fracture treated using a modified Kocher-style dorsolateral wrist exposure with cannulated compression screw fixation augmented by a distal radius T-plate. A 45-year-old, right-hand-dominant, male manual laborer presented after a fall on an outstretched hand with acute right wrist pain, swelling, deformity, and painful restriction of wrist motion. Radiographs and computed tomography evaluation showed a displaced extra-articular distal radius fracture with a dominant radial styloid/lateral fragment, minimal comminution, intact ulna, and congruent distal radioulnar joint. Open reduction and internal fixation was performed through a 5-cm dorsolateral modified Kocher-style approach. The fracture was anatomically reduced, buttressed with a distal radius T-plate, and compressed using a 3.0-mm cannulated compression screw placed from the radial styloid across the fracture line under fluoroscopic guidance. The postoperative course was uneventful. At 6 weeks, radiographs showed early callus and maintained alignment, with approximately 60° of active wrist flexion and 60° of extension without pain. At 3 months, radiographs showed union with trabecular bridging, clinically symmetrical wrist range of motion, grip strength comparable to the contralateral side, and return to manual work. At 1-year follow-up, the patient remained asymptomatic without tendon irritation, neurovascular deficit, implant prominence, loss of reduction, or need for implant removal. This case suggests that, in carefully selected distal radius fractures with a large radial styloid/radial column fragment and limited comminution, a modified Kocher-style dorsolateral approach with cannulated compression screw fixation and T-plate augmentation may provide stable reduction while avoiding a standard volar exposure. This technique is not proposed as a replacement for volar locking plating; rather, it may be considered as a selected alternative when fracture morphology permits direct fragment-specific compression and buttress support. The single-case design and absence of prospectively recorded patient-reported outcome scores limit generalizability.
More Related Videos
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
